
Digital Twins and AI-Driven Drug Discovery
This week in the Guardrail, we break down how predictive AI models and clinical digital twins are accelerating time to market, streamlining regulatory filings, and reshaping early-phase trial architecture.
This week in the Guardrail, we break down how predictive AI models and clinical digital twins are accelerating time to market, streamlining regulatory filings, and reshaping early-phase trial architecture.
By Michael Bronfman
October 5, 2026
The biopharmaceutical sector is undergoing a massive shift in how new medicines are discovered and brought to market. For decades, the industry relied heavily on experimentation: manual bench work, endless wet lab testing, and risky failure rates once molecules finally reached human trials. Today, that approach is rapidly changing. Modern drug design increasingly relies on predictive algorithms, molecular modeling, and virtual patient simulations to guide key decisions before physical testing begins.
Biotech and pharmaceutical companies are shifting away from traditional trial-and-error methods toward a design-first scientific workflow. Instead of spending months on manual lab iterations, research teams can now optimize molecules computationally in just a few days. Artificial intelligence models are no longer treated as experimental side projects; they are routinely cited inside Investigational New Drug (IND) applications and Biologics License Applications (BLA) submitted to major regulators like the US Food and Drug Administration. At the same time, using digital twins in early-phase trial design has moved from a novel idea to a practical tool for managing trial data, site logistics, and patient cohorts.
Regulatory Reality: AI Models in IND and BLA Submissions
For a long time, the biggest barrier to using computer models in drug development was regulatory acceptance. Health authorities required proof from lab cultures and animal studies, treating computational predictions as secondary background information. That line has blurred significantly over the last few years. Regulators now regularly review AI-generated structural models, machine learning predictions, and algorithmic data packages as part of official filings.
Moving Beyond Basic Screening
Early computational tools were mostly used for simple screening, helping scientists filter massive collections of compounds down to smaller lists. Today, machine learning systems can design target-specific molecules from scratch, predict how tightly they will bind to proteins, spot potential off-target side effects, and forecast how a compound will move through the human body.
When biotechs submit IND filings containing AI-designed compounds, regulatory reviewers evaluate the algorithm's design, training data, and validation tests right alongside standard preclinical lab results. This change cuts down the time required to turn an initial hit into a lead compound. Instead of making and testing dozens of physical variations one by one, teams can test multiple chemical properties at once inside a computer model.
Regulatory Frameworks Supporting Computational Science
Health authorities around the world have updated their working policies to keep pace with these technologies. Regulatory initiatives like Model-Informed Drug Development (MIDD) and Quantitative Systems Pharmacology (QSP) give sponsors clear paths to include algorithmic data in formal applications.
These frameworks lay out rules for testing predictive software, making sure algorithms are transparent, tracking data sources, and checking machine learning outputs for accuracy. By setting clear standards, regulators give biotech companies a reliable way to use synthetic data and predictive models to justify starting doses in humans, map out metabolic pathways, and avoid unnecessary animal testing.
Digital Twins in Early Phase Clinical Trials
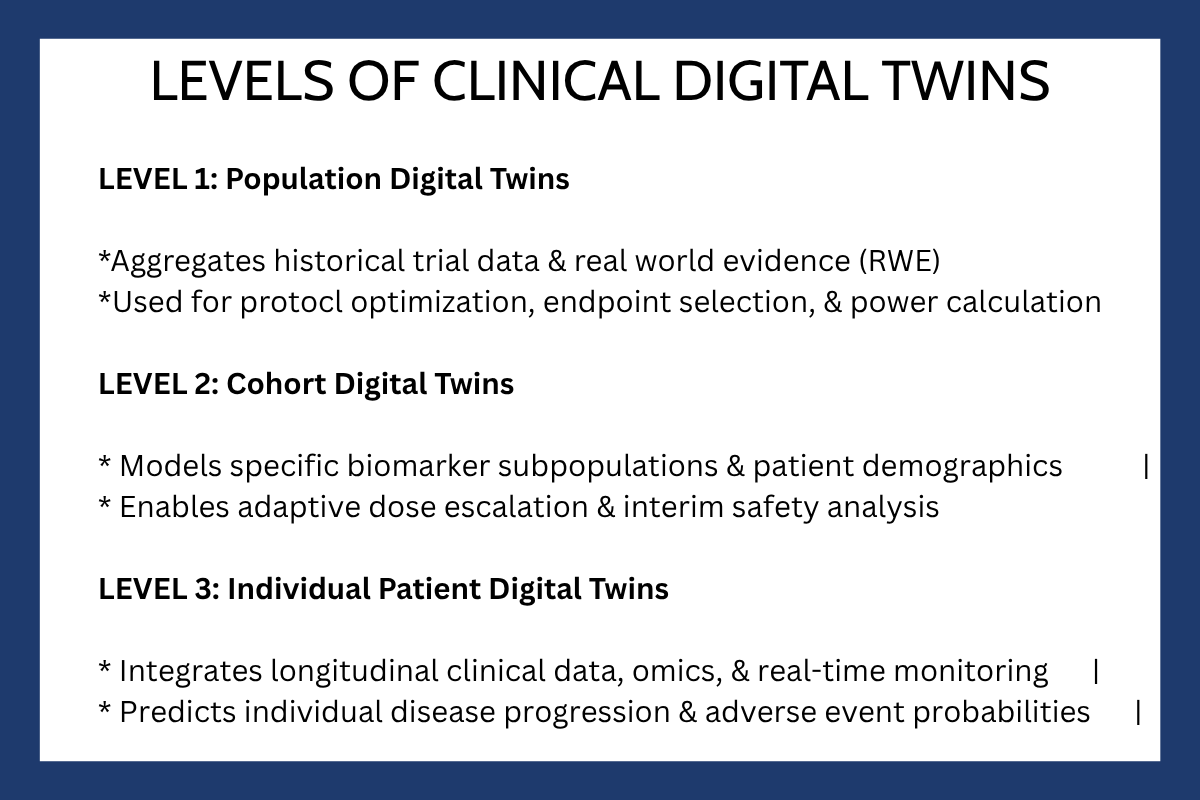
While AI algorithms handle molecule design, digital twin technology is helping reshape early-phase clinical trials. A clinical digital twin is a dynamic, detailed computer model of a biological system. It can represent a single organ, a disease pathway, or an individual patient participating in a trial.
In Phase 1 and Phase 2 trials, digital twin platforms pull in past trial records, real-world health evidence, genomic data, and patient tracking metrics. Using that information, the system simulates how different types of patients are likely to respond to a new treatment.
Building Synthetic Control Arms
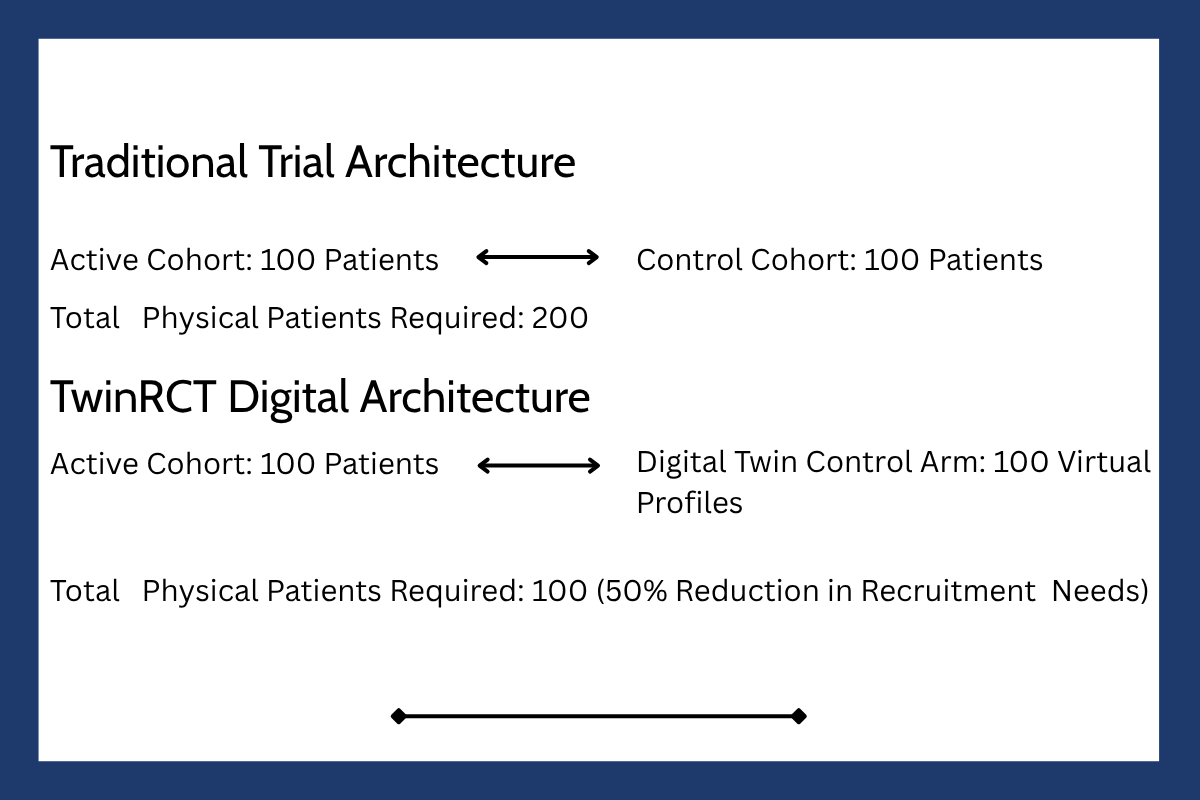
One of the most practical uses of digital twins is building synthetic or external control arms. Recruiting control patients for early-phase studies can be slow, expensive, and ethically tricky, especially when dealing with rare diseases or aggressive cancers where giving a placebo is hard to justify.
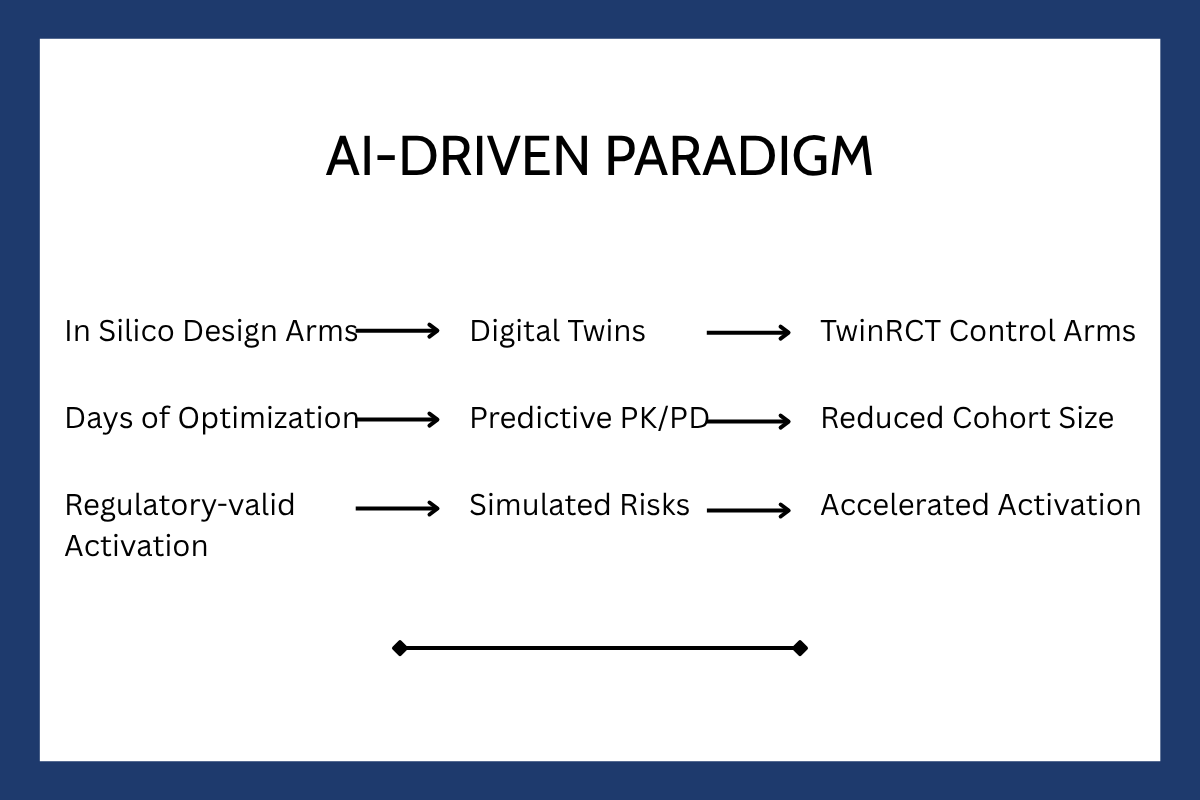
Digital twin software helps solve this problem by generating virtual control subjects matched to the real patients receiving the new treatment. Projecting how a patient's disease would normally progress under current standard care boosts the statistical strength of small studies without requiring companies to recruit large physical control groups. This approach, often called a TwinRCT, lets biotechs run smaller, faster trials that still meet strict regulatory standards for statistical proof
Improving Trial Protocols Before Enrolling Patients
Poorly designed trial protocols are a primary reason many drug candidates fail early in clinical testing. Problems like wrong dosing schedules, overly strict entry rules, or poorly chosen goals frequently derail promising drugs.
Digital twin simulations give research teams a risk-free way to test trial plans in advance. Teams can run thousands of virtual trial runs under different dosing schedules and rules long before the first real patient signs up. These virtual runs help highlight potential safety issues, find better dose levels, and spot places where patients might drop out. As a result, phase transitions go smoother, and teams have to make fewer costly changes once the trial is live.
Measuring the Impact: Manual Work vs Computational Design
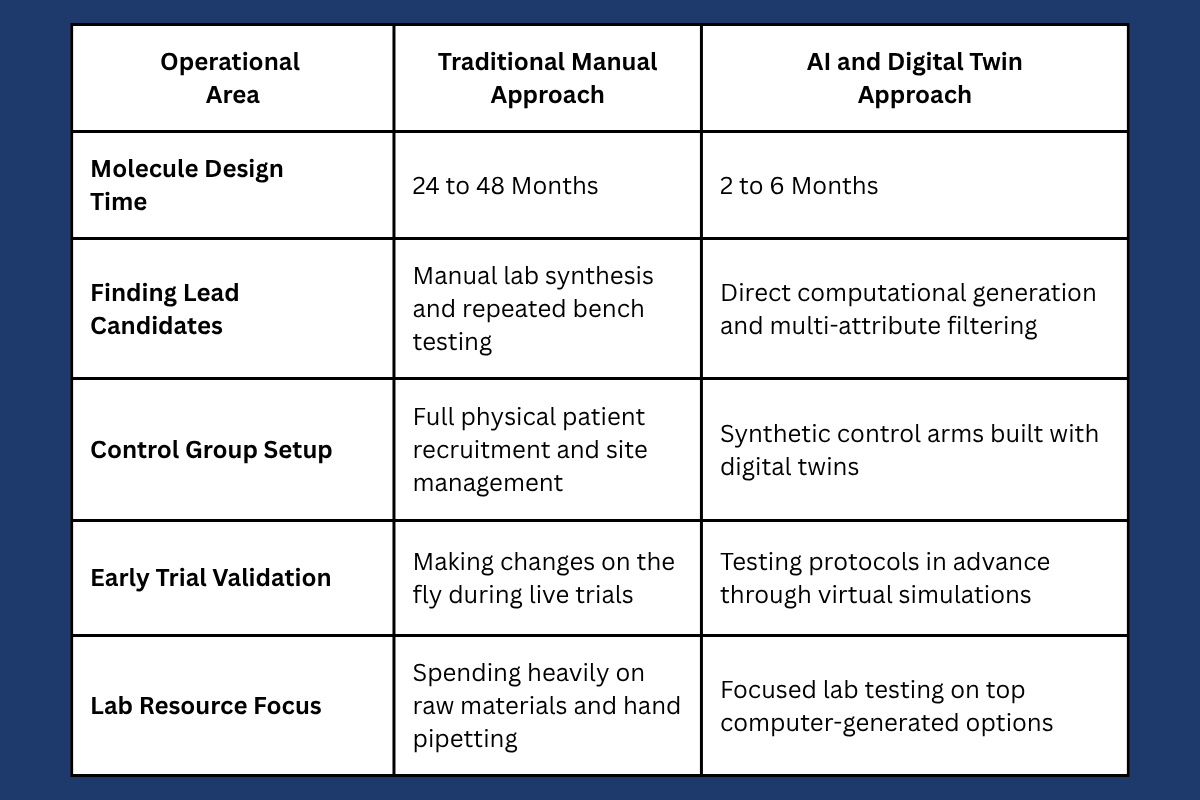
Swapping manual lab work for computational design changes both the timeline and economics of early research.
Reducing the Wet Lab Bottleneck
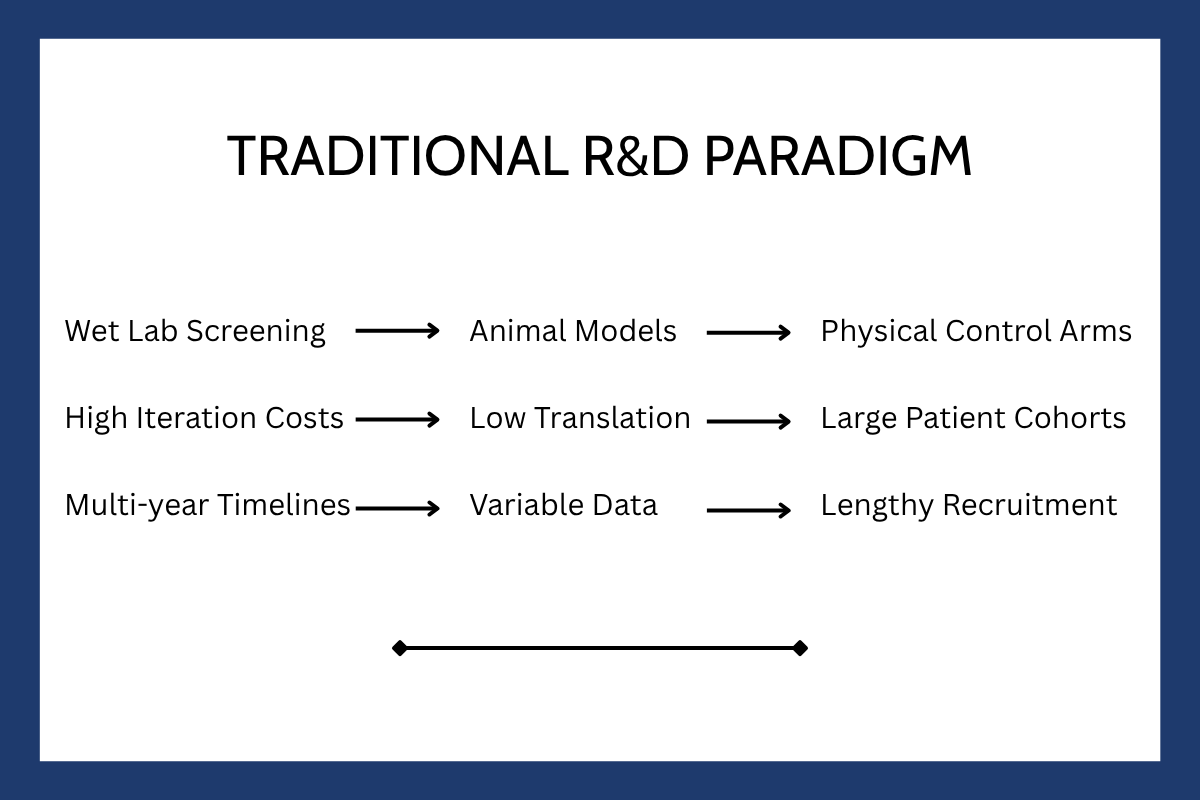
In traditional drug discovery, chemists make a batch of compounds, test them in cell dishes, study the results, and tweak the chemical structures to fix issues with performance or safety. This loop usually takes years and still ends with high failure rates once molecules reach living organisms.
Computational design turns that model upside down. Deep learning models can evaluate millions of virtual structures at once, checking them for target fit, ease of chemical synthesis, safety risks, and body absorption. Instead of using the physical lab to explore endless possibilities, scientists use it to double-check top computer predictions. Lab teams can focus on making a small, high-quality set of optimized candidates rather than hundreds of random shots in the dark.
Keeping Supply Chains and Lab Logistics Up to Speed
When software cuts compound design times from months down to days, physical labs run into immediate supply bottlenecks if they cannot order testing supplies fast enough.
Modern research relies heavily on digital procurement networks to streamline how teams order chemicals, cell lines, and standard lab supplies. Automating supply ordering ensures physical testing keeps pace with fast digital output, preventing material shortages from slowing down discovery timelines.
Overcoming Practical Challenges to Adoption
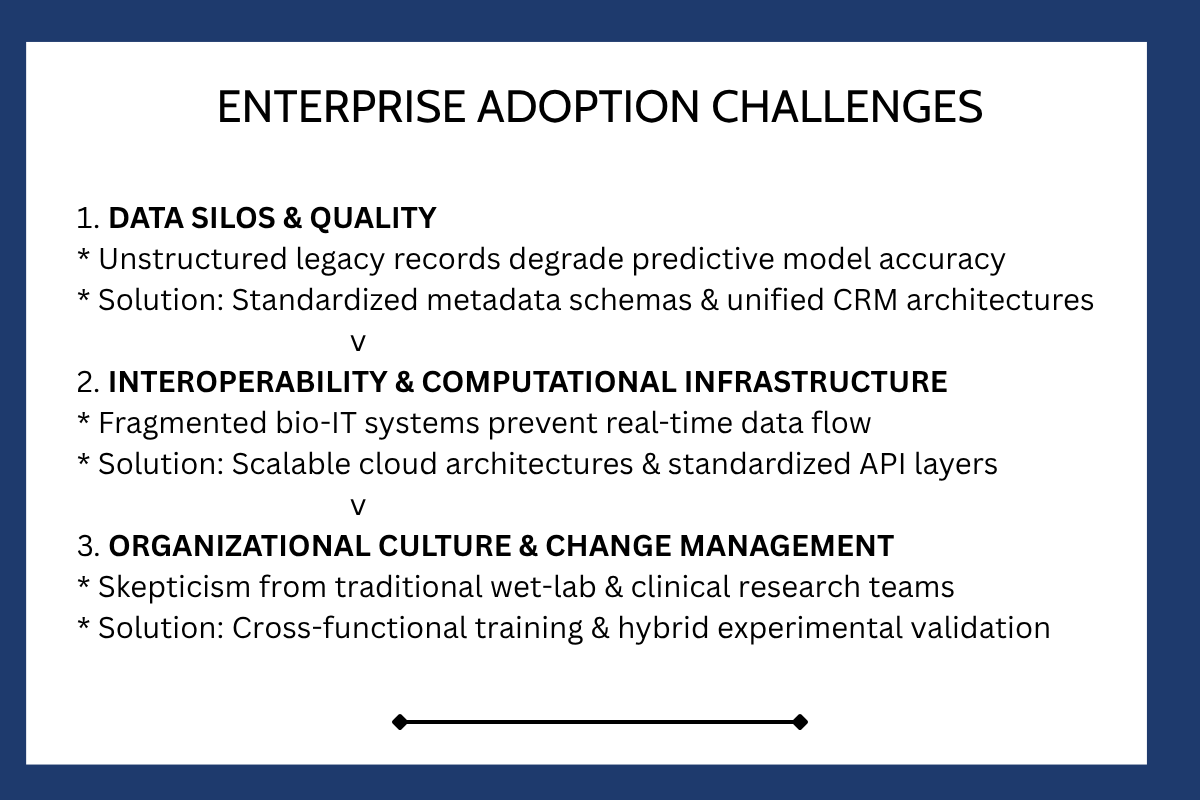
Even with clear benefits, adding AI models and digital twins to an existing pharma operation comes with real-world hurdles.
Data Quality and System Integration
An AI model or digital twin is only as reliable as the data used to train it. Messy historical records, poorly logged assay results, and missing trial details introduce errors into predictions. If a digital twin is built on incomplete or unbalanced trial data, its predictions will reflect those same flaws.
Companies need clear standards for managing their information. Setting up clean data formats, organizing electronic health records, and continuously gathering high-quality real-world evidence are necessary steps for building models teams can trust.
Connecting Lab Tools to Global Infrastructure
Linking computer models directly to daily trial operations requires solid software and infrastructure. IT departments must connect computational tools, lab data management software, and global logistical systems so information moves without friction.
Global management groups help biopharma organizations set up reliable operational frameworks, manage complex international logistics, and handle clinical trial supply chains across different countries. Ensuring software platforms talk to real-world logistics guarantees that digital discoveries transition smoothly into physical trial execution.
Bridging Team Gaps
Shifting to a predictive model requires cultural adjustments within research teams. There can sometimes be friction between computer scientists and traditional lab biologists or clinical staff. Lab veterans may feel skeptical of computer predictions, preferring physical test results they can see with their own eyes.
Overcoming this requires building mixed teams where computational scientists and lab staff work side by side throughout the project. When researchers see computer tools as helpful aids rather than replacements for human expertise, adoption happens naturally.
What This Means for Pharma Leadership
For executive teams, project leads, and clinical directors, adopting AI tools and digital twins is becoming a core practical requirement rather than a distant goal. Running multi-year discovery programs that end in high clinical failure rates is simply too risky and expensive for modern biotechs.
Smarter Spending and Risk Management
Developing new drugs takes enormous capital, with most of that money lost on clinical candidates that fail late in the process. Using digital twin simulations to stress test trial plans helps companies spot weak drug candidates much earlier.
Stopping dead-end projects early saves capital that can be redirected toward stronger candidates. In addition, using synthetic control arms cuts down on the number of physical patients needed for early trials, lowering recruiting costs and shortening trial setup times.
Key Steps for Building a Modern R&D Setup
To stay competitive, leadership teams should focus on three main operational goals:
Clean Up Data Pipelines: Build central data repositories that gather clean, organized trial and lab data from all internal teams and external partners.
Engage Regulators Early: Work with regulatory agencies early in the planning process using programs like MIDD to confirm computational methods and virtual control groups before launching trials.
Automate Operational Logistics: Connect computer design tools directly with digital ordering networks and automated lab hardware to keep physical testing moving at full speed.
Moving Toward Predictive Medicine
Combining artificial intelligence with digital twin models marks a permanent change in how drugs are researched and clinically tested. By including computational models inside IND and BLA regulatory packages and using digital twins to design smarter early-phase trials, life science companies are building a direct, efficient path to market.
Moving from manual experimentation to a design-first methodology lets companies swap months of slow trial and error for quick computational testing. Businesses that update their software systems, clean up their data pipelines, and connect their operational logistics will bring safer, more effective treatments to market with far fewer delays.
Sources:
Harvard, AI in Health Care: From Strategies to Implementation, Harvard Medical School, October 14, 2026
MIT, MIT Management Executive Education
Intglobal, Your Technology Sherpa
Clinical Digital Twins in Trial Design
Contact Metis Consulting Services to discover how we can help elevate your regulatory readiness and streamline your path to market.

Personalized Gene Editing: The Successful Treatment of "Baby KJ”

This week in the Guardrail, a remarkable medical triumph is quietly reshaping what we thought was possible. Step inside the emerging frontier where individualized medicine is rewriting the rules of healthcare—one patient at a time.
By Michael Bronfman
September 28, 2026
Every individual carries a unique genetic code made of over three billion DNA base pairs. When even a single letter in that immense sequence is mismatched, the consequences can be devastating. For generations, medicine had no way to fix these fundamental errors. Doctors could only treat the symptoms while rare genetic conditions progressed without a cure. Today, that reality is changing rapidly. The arrival of bespoke gene editing lets scientists write custom genetic fixes designed for an individual's exact mutation.
This new frontier moves beyond standard treatments meant for broad populations. Instead, it focuses on personalized solutions for ultra-rare diseases once considered untreatable. Recent clinical breakthroughs show how custom gene tools, collaborative research, and targeted delivery methods are changing modern medicine.
The Rise of Custom Genetic Medicine
Traditional pharmaceutical models rely on mass production. Researchers test a single drug across large groups of people, manufacture it in vast quantities, and give it to millions who share the same general diagnosis. While this model works well for common health conditions, it leaves millions of people behind. There are over seven thousand known rare diseases, yet fewer than ten percent have an approved drug. Most of these conditions affect tiny groups of individuals, sometimes only a handful of patients worldwide. Commercial drug companies rarely invest the hundreds of millions of dollars needed to develop treatments for such small groups.
Bespoke gene therapy flips this standard model on its head. Rather than forcing a single drug to fit millions of patients, scientists analyze one person's genome to identify the exact spot where a mutation occurs. They then build a custom therapeutic package engineered to repair or correct that exact genetic code.
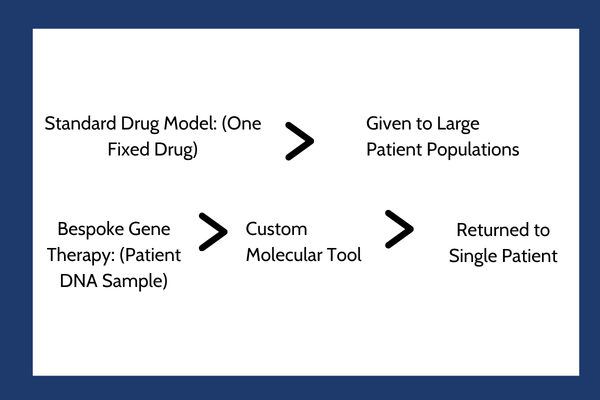
This approach relies heavily on precise genomic sequencing. Modern sequencing machines can read a human genome in hours, allowing medical teams to locate single base-pair changes almost instantly. Once researchers know the target sequence, they select an appropriate gene-editing tool to correct the error directly inside the cell.
The Historic Breakthrough for Baby KJ
The true potential of custom gene editing was recently demonstrated through the case of an infant known as Baby KJ. 1 Born with a severe metabolic disorder known as carbamoyl phosphate synthetase 1 deficiency, KJ was unable to process proteins safely. Without a functional version of this critical enzyme, toxic levels of ammonia built up in his blood shortly after birth. Standard care for this condition involves strict dietary limits, medications to bind excess nitrogen, and eventually a liver transplant.

Because KJ carried a unique single-letter mutation, standard drug therapies could not fix the underlying cause. A dedicated team of scientists and doctors from public academic centers and private biotechnology partners quickly gathered to build a custom solution. They selected a technology called base editing, which acts like a precise pencil and eraser to change one genetic letter into another without cutting both strands of the DNA molecule.
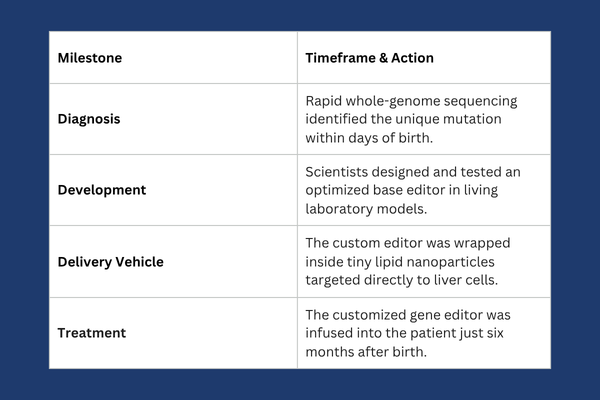
The results of this single patient trial showed clear signs of success. After his infusions, KJ tolerated higher levels of dietary protein and showed reduced dependence on nitrogen-removing medications, with no serious side effects. This rapid turnaround proved that a custom gene-editing therapy can move from design to human delivery safely in months rather than years. (A)
Broadening the Horizon: Progress in Huntington Disease
While single-patient treatments show what is possible at the individual level, bespoke gene tools are also creating pathways to treat complex inherited conditions that affect larger groups. Huntington disease is a fatal inherited condition caused by a repeating expansion in the huntingtin gene. This repeating sequence produces a toxic mutant protein that slowly destroys nerve cells inside the brain, causing loss of movement, cognitive decline, and psychiatric changes.
For decades, medical science struggled to slow the progress of this devastating condition. Recent clinical trials using targeted gene therapy vectors have broken that long standstill. An experimental therapy known as AMT-130 uses a modified harmless virus to deliver custom genetic instructions directly into deep brain structures. These instructions tell the brain cells to block the production of the toxic mutant protein.
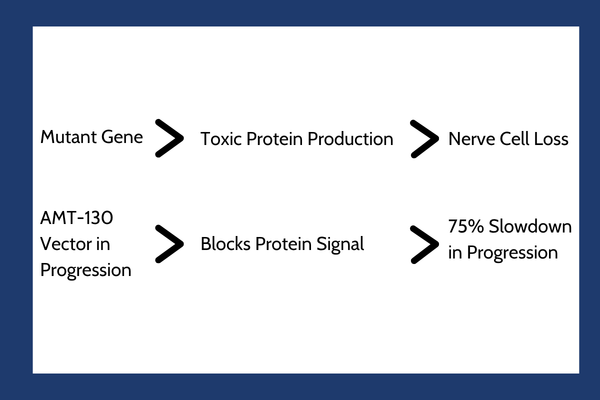
Clinical trial results revealed that high-dose groups receiving this targeted gene therapy experienced up to a 75 percent slowdown in disease progression over three years compared to expected natural decline. This functional preservation provides strong evidence that genetic interventions can protect delicate neural tissues from inherited defects. (B)
Defining N of 1 Therapies
Cases like Baby KJ represent a new classification in medicine: N of 1 therapies. In scientific research, the letter N stands for the total number of subjects in a trial. An N of 1 trial means the entire clinical trial is designed, executed, and evaluated for a single individual.
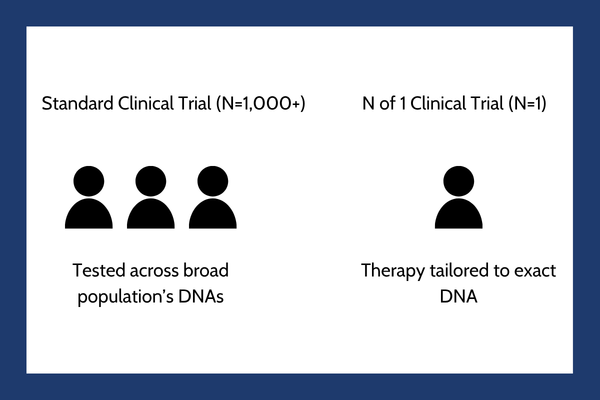
This model is fundamentally different from traditional drug development in several key ways:
Target Specificity: Standard drugs bind to broad biological pathways present in everyone. N-of-1 treatments target the exact sequence variation found in one person.
Modular Platforms: Researchers use standardized delivery tools like lipid nanoparticles or harmless viral shells, changing only the internal genetic code payload for each new case.
Speed of Creation: Because the delivery system stays constant, researchers can synthesize new therapeutic payloads in weeks once they identify the target DNA.
Direct Patient Testing: Preclinical testing focuses entirely on the patient's own cell samples in laboratory dishes to confirm safety before treatment begins.
By viewing the delivery system as a reusable vehicle and the genetic editor as software, medicine can create custom treatments for rare mutations without starting from scratch every single time.
Collaborative Networks and Regulatory Frameworks
Developing a unique drug for one individual requires breaking down traditional walls between academic researchers, regulatory agencies, and commercial drug companies. Public/Private partnerships have become the foundation of this progress.
Organizations like the Bespoke Gene Therapy Consortium2 bring together national health institutes, universities, and pharmaceutical corporations. Their goal is to create standardized operational playbooks for custom therapies, making the process faster and less costly.
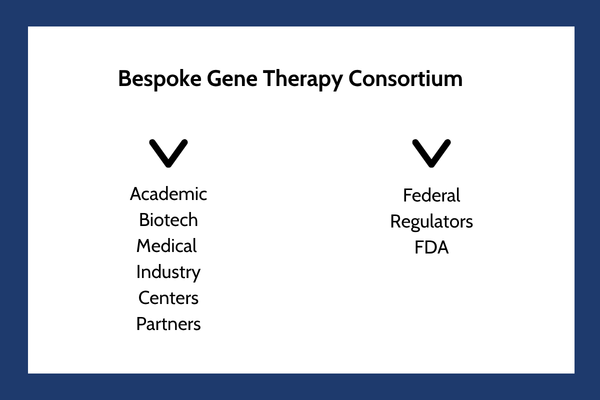
Regulatory agencies like the United States Food and Drug Administration have established updated draft guidance to help streamline N-of-1 clinical trials. These frameworks provide clear rules for safety testing, quality manufacturing, and reporting patient outcomes when a drug will be given to only one person. Anyone who wants to learn more about these collaborative efforts can visit the National Institutes of Health regulatory hub. (B)
Overcoming Challenges in Custom Gene Editing
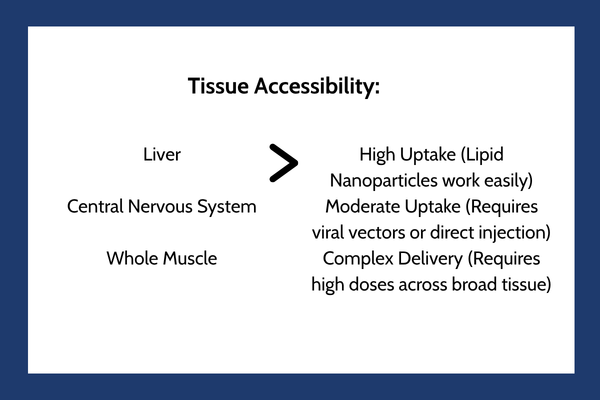
Despite notable early successes, expanding bespoke gene editing from isolated cases into standard medical care presents real hurdles. Delivering complex molecular tools to the right tissues remains a central challenge. While liver cells readily take up lipid nanoparticles, reaching cells in the brain, heart, or deep skeletal muscle requires specialized vector systems that are difficult to manufacture consistently.
Manufacturing costs also represent a major barrier. Producing a single batch of custom clinical-grade editor molecules under strict sterile conditions can cost hundreds of thousands of dollars. Finding sustainable ways to fund these treatments through public health programs or insurance coverage is essential so these breakthroughs do not remain restricted to a fortunate few.
Safety monitoring must also remain extraordinarily rigorous. Because N-of-1 therapies move quickly into human application, researchers perform extensive laboratory testing on patient cells to check for off-target editing, where the molecular tool cuts or alters unintended spots in the DNA sequence.
The Road Ahead for Personalized Medicine
Bespoke gene editing marks a permanent shift in how humanity approaches genetic disease. As base editors, prime editors, and gene delivery vectors continue to improve, the time needed to design and deliver a personalized treatment will continue to shrink.
The success seen in patients like Baby KJ shows that ultra-rare conditions no longer need to be considered incurable death sentences. By combining standardized delivery platforms, supportive regulatory pathways, and dedicated public/private partnerships, scientists are turning personalized genetic corrections into a reliable medical reality. The era of one-size-fits-all medicine is giving way to a future where every patient can receive a cure built specifically for them.
Navigate regulatory frameworks, accelerate development pathways, and commercialize cutting-edge genetic solutions. Contact Metis Consulting Services today and transform your strategic vision into clinical reality.
Sources:
1Innovative Genomics Institute, First Patient Treated with Personalized CRISPR Therapy, Developed in Just Six Months, May 15, 2025, by Andy Murdock
2Healthbeat, Huntington's Disease Progress in Gene Therapy, December 2025
3NIH, Gene Targeted Therapies, Bespoke Gene Therapy Consortium (BGTC)

What is Prime Editing? And How is it Used in Real World Applications?

This week, check out a deeper dive into how next-generation prime editing brings true surgical precision to genetic medicine. Building on our September 7, 2026 post on early gene editing. "Prime Editing: Changing How We Fix Broken Genes"
By Michael Bronfman
September 21, 2026
In our last blog post, we looked at how early gene editing opened up brand new possibilities for fixing genetic conditions. Today, we build directly on that foundation. We are taking a much deeper, more comprehensive dive into how next-generation gene editing moves far beyond rough cellular cuts toward real surgical precision inside the human body.
In that previous article, we mentioned how scientists can now rewrite faulty genetic code directly inside living cells. Now, let us explore how that process works in real clinical environments, what makes it drastically safer, and where human clinical testing stands today.
What Is Prime Editing?
Think of prime editing as a search-and-replace tool for human DNA.
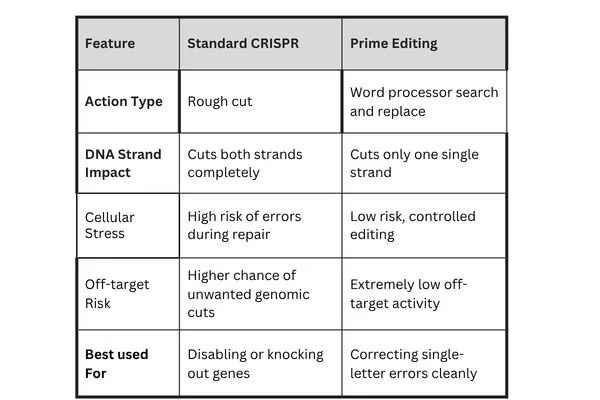
To understand why this technology represents a massive leap forward, it helps to see how older gene-editing tools work. For years, genetic medicine relied on standard CRISPR tools. Standard CRISPR acts like a pair of rough molecular scissors. It cuts through both strands of the DNA double helix at a targeted spot.
Once both strands are severed, the cell panics. It rushes to patch the broken ends back together using natural emergency repair mechanisms. Because that emergency fix is rushed, the cell often makes costly mistakes. It can accidentally delete important genetic information or mix up chemical letters. Worse, the scissors might accidentally cut DNA at the wrong spot elsewhere in the genome. Scientists call these accidental cuts off-target effects.
Prime editing fixes this major flaw. Instead of cutting through both strands of human DNA, prime editing cuts only one single strand. Leaving the second strand whole keeps the overall structure stable. The cell stays calm, making the whole repair process safer, cleaner, and more reliable for therapeutic applications.
How Search and Replace Works inside the Cell
To see how prime editing carries out a repair, we can break the machinery down into three main components.
1. The Target Site
Every cell in your body runs on instructions stored in DNA. These instructions use four chemical letters: A, T, C, and G. A single wrong letter among billions can cause a severe, life-altering genetic disease.
2. The Search Tool
Prime editing uses a modified Cas9 protein paired with a custom guide strand. This guide travels through the cell nucleus, scanning millions of letters until it locks onto the exact matching error in your genetic code.
3. The Replace Tool
Once the tool finds the target, an attached enzyme called reverse transcriptase gets to work. This enzyme reads new genetic instructions carried right on the guide strand. It then writes those corrected chemical letters straight into the single strand of DNA. The cell incorporates the new code, permanently fixing the original error without any random cellular guesswork.
Comparing Gene Editing Methods
Standard CRISPR works well if your goal is simply to break a harmful gene so it stops working. However, if you want to make a precise repair, prime editing is the superior choice for clinical safety.
Real World Medical Applications
Researchers are using prime editing to tackle some of the most challenging inherited diseases across multiple body systems.
Liver Diseases: The liver easily absorbs lipid nanoparticles, which are tiny protective bubbles used to carry fragile genetic medicines inside cells. Conditions like alpha-1 antitrypsin deficiency cause toxic, misfolded proteins to build up in liver cells. Prime editing can correct the single wrong letter responsible for the bad protein. Once corrected, the liver produces healthy proteins normally.
Lung Diseases: Lung tissue is tricky to reach, but new delivery systems are changing that. Conditions like cystic fibrosis stem from errors in genes that control salt and fluid balance in the lungs. Prime editing can rewrite those faulty sequences in lung stem cells, helping restore healthy mucus flow and clearing clogged airways.
Blood Disorders: Sickle cell disease and beta thalassemia come from single-letter mistakes in the hemoglobin gene. Prime editing rewrites those faulty letters back to normal. Because this method avoids double-strand DNA cuts, it lowers the risk of dangerous chromosome damage in blood stem cells.
Neurological Conditions: Researchers are beginning to adapt prime editing for non-dividing cells in the central nervous system. Disorders like Huntington disease feature repeated, toxic genetic sequences. Prime editing can delete these excessive repeats with surgical precision, offering hope for targeted treatments in brain tissue.
Muscular Dystrophies: Inherited muscle disorders often involve specific mutations across vast structural proteins. Prime editing allows researchers to insert larger corrected fragments without damaging surrounding tissue fibers, preserving long-term muscle function.
The Road Through Clinical Testing
Bringing a new genetic therapy out of the lab and into hospitals requires a strict, step-by-step evaluation process. Right now, prime editing is moving through human trials to confirm both safety and long-term performance.
1. Preclinical Phase: Lab testing in cell cultures and animal models.
Scientists test the editor inside human cells grown in lab dishes and in animal models. They measure how accurately the tool edits the target site and check for any accidental cuts across the entire genome.
2. Phase 1 Human Trials: Evaluating safety in small groups.
A small group of human patients receives the treatment. Doctors closely monitor patients to ensure the immune system does not react negatively to the editing machinery. Safety is the primary goal here.
3. Phase 2 Human Trials: Testing dosage and efficacy.
Researchers administer the therapy to a larger group of patients to evaluate efficacy. For liver and lung conditions, doctors check if organ function improves and if clinical symptoms disappear.
4. Phase 3 Human Trials: Comparison against standard care.
Large-scale trials compare the prime editing treatment directly against existing standard therapies. Successful results clear the way for official regulatory approval.
Engineering Hurdles Scientists Are Solving
Despite its immense promise, scientists are actively working to overcome a few remaining biological and technical challenges before these treatments become widespread.
Delivery Systems: Getting large molecular machines inside the correct human cells remains challenging. Researchers use microscopic lipid bubbles or modified viral shells to transport the tools. Ensuring these vehicles reach deep tissue in the lungs or liver without triggering immune inflammation is a major focus of active trials.
Size Limits: Prime editing tools are larger than standard CRISPR systems. The combined complex includes a modified cutting protein, a reverse transcriptase enzyme, and an extended guide strand. Packing all these parts into a single delivery vehicle requires advanced bioengineering.
Editing Efficiency: Prime editing works with impressive efficiency in fast-dividing cells. However, in non-dividing cells like mature heart, nerve, or brain cells, success rates can drop. Researchers continue modifying the guide structures and protein enzymes to boost performance across every tissue type in the human body.
Scalable Manufacturing: Producing high-purity, clinical-grade genetic machinery at a global scale requires specialized production infrastructure. Ensuring consistency across massive production batches is critical as these therapies progress toward commercial approval.
Off-Target Surveillance: While prime editing reduces unintended edits significantly, clinical developers must deploy long-read sequencing technologies to scan whole genomes, ensuring zero unexpected genomic rearrangements occur over time.
What Comes Next?
Prime editing represents a monumental step forward for modern medicine. By moving away from double-strand cuts and offering true search-and-replace capabilities, it opens the door to treating thousands of genetic conditions at their root source.
Over the next few years, human data from ongoing liver, lung, and blood trials will reveal how well this technology performs in real world medicine. If these trials succeed, prime editing could soon become the new gold standard for precise genetic cures.
Streamline your clinical development, navigate complex regulatory hurdles, and bring groundbreaking therapies from the lab to patients faster. Contact Metis Consulting Services today.
High Cholesterol Gone with One Treatment?
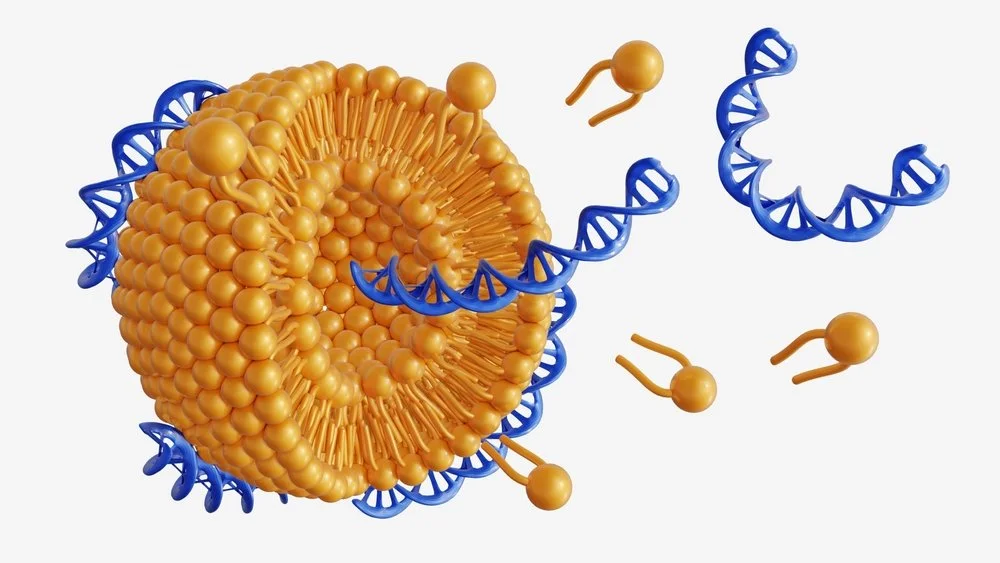
Base editing technology is moving beyond rare diseases to potentially eliminate high cholesterol with a single, highly precise genetic intervention. A profound paradigm shift from lifelong daily disease management to permanent, proactive prevention. Read about it this week in the Guardrail, The Power of Gene Editing
By Michael Bronfman
September 14, 2026
Imagine going to the clinic for a single shot and fixing your high cholesterol for the rest of your life. For millions of people worldwide, this sounds almost like magic. However, new medical progress is turning this dream into real science.
In mid 2025, A major pharmaceutical company bought out a smaller biotechnology company called Verve Therapeutics. In order to gain control of some advanced genetic tools. The main focus of this effort is a new experimental drug called VERVE 102.1.1
This drug uses a super precise technology called base editing. Unlike older ways of fixing genes, base editing acts like a tiny spell checker for your DNA. Instead of cutting the DNA strand completely, it neatly changes one single genetic letter. VERVE 102 targets a specific liver gene called PCSK9. By turning off this single gene, the body can clear bad cholesterol from the blood much faster.
As Phase 2 clinical trials expand, scientists and doctors are closely examining how this technology works. They are looking at what makes it safe and how it could completely change how we treat common long-term health conditions.
Understanding the Danger of High Cholesterol
To see why this new treatment is such a big deal, we first need to understand how cholesterol harms the human body.
Your body needs some cholesterol to build healthy cells. But too much of one specific type, called low-density lipoprotein (LDL) cholesterol, creates serious trouble. People often call LDL “bad cholesterol.” When you have high levels of LDL floating through your bloodstream for many years, it builds up inside the walls of your arteries. This buildup turns into hard spots called plaque.
Over time, plaque narrows and stiffens your blood vessels. This condition is known as atherosclerosis. When arteries get clogged, blood cannot flow easily to vital organs. If a piece of plaque breaks open, a blood clot can form quickly. This blockage can cause a sudden heart attack or a stroke. Cardiovascular disease remains the number one cause of death worldwide.
Many people try to lower their bad cholesterol by eating healthy food and exercising regularly. While lifestyle changes are important, they are often not enough. Many people have genes that make their bodies produce far too much cholesterol, no matter what they eat.
For decades, doctors have relied on daily pills called statins. Statins work well for millions of people, but only if they take them every single day. Many patients struggle to take a pill every day for the rest of their lives. Some people experience muscle pain or other side effects from statins. Others take their daily medication, but their bad cholesterol still stays at dangerous levels.
This gap in results is why scientists have been searching for a better, longer-lasting solution.
How PCSK9 Controls Your Cholesterol
To lower cholesterol permanently, scientists had to find the biological switch that controls it in the liver. They found that switch in a protein named PCSK9.
Your liver cells have small receptors on their surface that act like tiny nets. These receptors catch bad LDL cholesterol as it flows through the blood and pull it inside the liver cell to be broken down. After dropping off the cholesterol, the receptor returns to the cell surface to catch more. This recycling system keeps your blood clean.
This is where the PCSK9 protein comes in. PCSK9 binds to those cholesterol receptors and stops them from recycling. Instead of sending the receptor back to the surface, PCSK9 causes the cell to destroy the receptor inside.
When your body makes a lot of PCSK9, you have fewer receptors on your liver cells. Fewer receptors mean bad cholesterol stays in your blood longer.
When your body makes very little PCSK9, your liver cells recycle their receptors over and over again. This pulls huge amounts of bad cholesterol out of your bloodstream.
Years ago, researchers made a surprising discovery while studying people with rare genetic mutations. They found individuals who were born with a broken PCSK9 gene. These people naturally made almost no PCSK9 protein. Surprisingly, they were completely healthy, had extremely low bad cholesterol levels, and almost never developed heart disease.
This discovery proved that humans do not need active PCSK9 to live a healthy life. It gave scientists a clear goal. If they could turn off the PCSK9 gene in adults, they could permanently protect them from heart attacks.
The Evolution of Gene Editing: From Scissors to Spell Checkers
Early attempts to edit human genes used a famous tool called CRISPR-Cas9. Think of original CRISPR as a pair of molecular scissors. It finds a specific spot in your DNA and cuts clear through both strands of the double helix.
While cutting DNA can turn off a faulty gene, “double-strand breaks” bring some risks. When a cell tries to glue the two cut ends of DNA back together, it can sometimes make mistakes. It might accidentally delete a small section of DNA or rearrange pieces erroneously. When treating millions of people for a common illness, doctors need tools that are as safe and precise as possible.
This need for safety led to the innovation of base editing. Developed by researchers like David Liu at Harvard University, base editing is a major leap forward in genetic medicine.2
This need for safety led to the innovation of base editing. Developed by researchers like David Liu at Harvard University, base editing is a major leap forward in genetic medicine.2
Instead of cutting the DNA completely, a base editor works like a pencil and eraser. DNA is made of four chemical bases represented by the letters A, C, G, and T. A base editor travels to a specific spot in the DNA, opens the double strand gently without breaking it, and chemically changes one letter into another.
In VERVE 102, the base editor targets the PCSK9 gene in liver cells. It changes a single A letter to a G letter. This tiny, single-letter change alters the biological instructions just enough to stop the liver cell from producing the PCSK9 protein entirely. Because there are no double-strand cuts, the risk of accidental genetic damage drops significantly.
Inside the Treatment: Delivery via Lipid Nanoparticles
Having a clever genetic editor in a test tube is only half the battle. The biggest challenge in genetic medicine has always been delivery. How do you get the base editor inside millions of liver cells inside a living human body without causing harm?
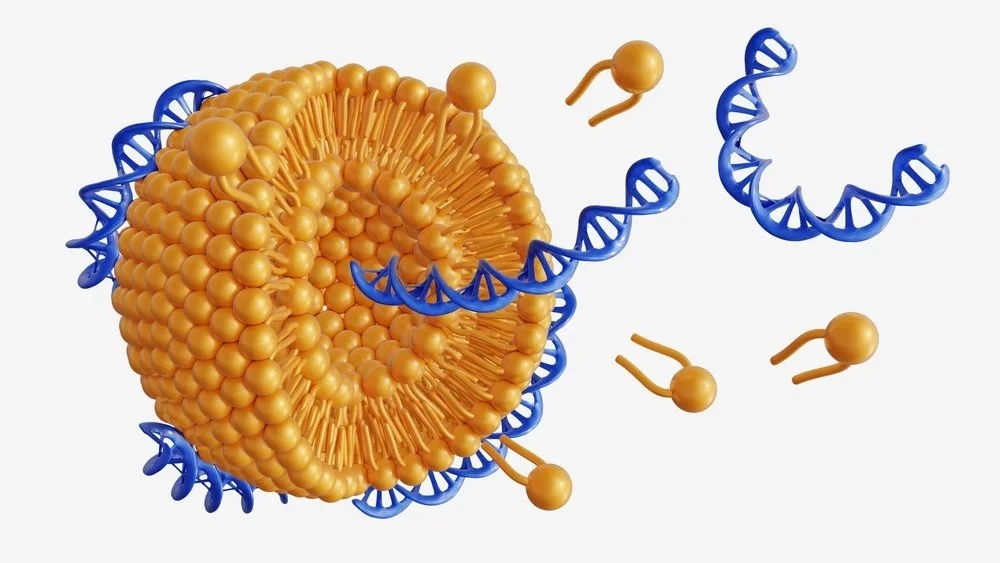
They are solving this by using tiny spheres of fat called lipid nanoparticles, or LNPs. If you received an mRNA vaccine for COVID-19, you are already familiar with lipid nanoparticles. They act like microscopic protective bubbles that carry fragile genetic instructions safely through the bloodstream.
Here is how the treatment works step by step:
- The Dose Preparation: The treatment contains two main components packaged inside the lipid nanoparticle. The first is messenger RNA that tells the cell how to build the base editing protein. The second is a guide RNA that acts like a GPS map, showing the protein exactly where to find the PCSK9 gene. 2.** Simple Infusion:** The patient receives the drug through a simple intravenous, or IV, line in their arm during a standard clinic visit. No surgery, bone marrow removal, or complex hospital stays are required.
- Liver Targeting: The lipid nanoparticles are specially designed with surface molecules that naturally attract them to liver cells. Once injected, they travel through the blood straight to the liver.
- Cell Entry: The liver cells absorb the lipid nanoparticles. Inside the cell, the lipid bubble dissolves, releasing the genetic instructions.
- The Edit: The liver cell uses the mRNA to build the base editor protein. Guided by the guide RNA, the editor enters the cell nucleus, finds the PCSK9 gene, and makes the single-letter change.
- Clean Departure: Once the edit is made, the editor protein and the lipid nanoparticle naturally break down and disappear from the body within a few days. But the change to the DNA remains permanent. Whenever that liver cell divides, its daughter cells inherit the edited, non-working version of the PCSK9 gene.3
Clinical Trial Results and What the Science Shows
The excitement surrounding VERVE 102 comes directly from real clinical data collected in human trials.
Earlier clinical studies testing the first version of this concept showed that base editing could dramatically lower PCSK9 protein levels in humans. However, early delivery methods caused temporary side effects, leading researchers to refine the lipid nanoparticle shell. The updated formulation, VERVE 102, was designed to be gentler on the body while delivering the same powerful genetic edit.
Recent clinical updates show impressive outcomes:
Dramatic Cholesterol Drop: Patients receiving a single high dose of VERVE 102 saw their bad LDL cholesterol levels fall by over 50 to 60 percent.
PCSK9 Shutdown: Measurement of the PCSK9 protein in the blood showed a drop of up to 88 percent, showing that the base editor successfully turned off the targeted gene in most liver cells.
Durable Impact: Follow-up data showed that the reduction in bad cholesterol remained steady over time. Because the edit is made directly to the cell's DNA, the liver continues to produce low cholesterol levels month after month without needing additional doses.
Shifting from Acute Care to Chronic Prevention
For decades, the standard model of medicine has been reactive care. We wait until a person develops high cholesterol or suffers a minor heart event, and then we prescribe a daily pill that they must take for thirty or forty years.
This model has major flaws. First, human behavior is imperfect. Studies show that within one year of being prescribed a daily statin, up to half of all patients stop taking their medication regularly. Life gets busy, prescriptions expire, pills are expensive, and side effects cause people to quit. Every day a patient skips their medication, their risk of a heart attack creeps back up.
Second, chronic care costs healthcare systems a lot. Decades of doctor visits, blood tests, and daily drug refills cost insurance companies, governments, and patients thousands of dollars per year.
Base editing introduces a completely new way of thinking about chronic disease. Scientists call it the "one and done" paradigm. Instead of managing a disease over a lifetime with thousands of pills, a patient receives a single therapeutic intervention that fixes the root cause forever.
If successful in broader Phase 2 and eventual Phase 3 trials, VERVE 102 could transform cardiovascular care from a lifelong burden into a single, proactive medical visit.
Safety and Regulatory Considerations
While the promise of base editing is huge, safety remains the top concern for doctors and regulators alike. When you take a daily pill, you can stop taking it if you experience bad side effects. But when you edit a person's DNA, you cannot hit an undo button. The change is permanent.
Because of this, researchers monitor clinical trial participants very closely for two primary risks:
Off-target Editing
An off-target edit happens if the guide RNA accidentally directs the base editor to the wrong spot in the genome. If the tool alters a healthy, important gene elsewhere in the cell, it could lead to unexpected health problems, including cancer. To prevent this, scientists use advanced computer modeling and deep sequencing to test millions of DNA sites, ensuring the guide RNA only binds to the target gene.
Liver Health and Inflammation
Because the drug delivers lipid nanoparticles directly to the liver, doctors must monitor patients for liver inflammation or temporary spikes in liver enzymes. Clinical trials track blood tests closely after the infusion to verify that the liver remains healthy and functions normally.
Regulatory bodies like the FDA require gene editing candidates to undergo years of careful tracking. Patients in early trials are followed for up to fifteen years to confirm that the editing remains safe and effective over long periods.
Expanding Beyond Cholesterol
Big pharmaceutical companies believe gene editing is ready for common conditions.
In the past, gene therapy was reserved almost exclusively for rare, deadly genetic conditions like sickle cell disease or spinal muscular atrophy. These conditions affect small numbers of people who have no other treatment options. Because the conditions are severe, regulators and patients are willing to accept higher costs and risks. Eli Lilly's acquisition of Verve Therapeutics in mid-2025 signals a major shift away from that model.
High cholesterol affects tens of millions of adults worldwide. By bringing base editing to hyperlipidemia, they are testing whether genetic medicine can scale up to treat common public health problems.
If base editing works safely for high cholesterol, the same platform can be adapted to treat many other long-term health issues:
- High Triglycerides: Editing genes like ANGPTL3 to lower dangerous blood fats.
- Hypertension: Targeting genes involved in blood pressure regulation to permanently lower high blood pressure.
- Type 2 Diabetes: Editing specific liver or pancreas pathways to improve how the body responds to insulin.
- Liver Disease: Turning off genes that cause fat accumulation or scarring in the liver. 4
The Path Ahead
The journey of VERVE 102 through clinical trials is one of the most exciting stories in modern medicine. It represents a shift in how humanity approaches human health. We are moving away from treating symptoms with daily chemicals and moving toward fixing the underlying source code of human disease.
Important questions remain to be answered over the coming years. Will insurance companies cover the upfront cost of a one-time gene editing treatment? How long will the cholesterol-lowering effect last in humans over twenty or thirty years? Will broader trials confirm that side effects remain minimal?
As Phase 2 trials continue to gather data, the scientific world is watching closely. If the results hold true, we may be standing at the beginning of an era where heart attacks become a preventable worry of the past, defeated by a single, precise genetic edit.
Navigating complex regulatory expectations, quality systems, and clinical trial oversight is vital, as gene therapies and advanced precision technologies scale toward mass markets. Contact Metis Consulting Services
Footnotes:
You can read more about how lipid nanoparticles deliver therapies by visiting the National Institutes of Health website.
To explore ongoing research in genetic science and biotechnology, you can visit the World Health Organization website.
To learn more about how clinical trials are designed and monitored for safety, check out the educational resources on the US Food and Drug Administration website.

Prime Editing: Changing How We Fix Broken Genes

This week in the Guardrail, we explore how next-generation gene editing is moving beyond rougher cellular cuts toward surgical precision.
By Michael Bronfman
September 7, 2026
Think of it like a search-and-replace tool for human DNA.
For years, genetic medicine relied on older CRISPR tools. Older CRISPR works like molecular scissors. It cuts both strands of human DNA at a specific spot. Then, the cell tries to patch the broken DNA back together. This process can create mistakes. It can cause unwanted cuts in other parts of the genome. These mistakes are called off-target effects.
Prime editing is different. It does not cut both strands of the DNA double helix. Instead, it cuts only one single strand. This makes the editing process much safer and more precise.
Right now, prime editing is moving into a major human testing phase. Researchers are running clinical trials to see how well it works inside the human body. Early trial data focuses on diseases that affect the liver and the lungs.
How Prime Editing Works
To understand prime editing, it helps to review the main parts of the cell system.
The Target Site
Every cell carries DNA. DNA holds the instructions for life. These instructions are written in four chemical letters. They are A, T, C, and G. Sometimes, a single letter is wrong. That small error can cause a severe genetic disease.
The Search Tool
Prime editing uses a modified protein to find the exact location of the error. The system includes a custom guide sequence. This guide moves through the cell and locks onto the matching spot in the genome.
The Replace Tool
Once the tool finds the target, an enzyme goes to work. This enzyme is a reverse transcriptase. It reads new genetic instructions carried by the prime editing guide. Then, it writes those new letters directly into the target single strand of DNA. The cell integrates this corrected sequence, fixing the original error.
What is the Difference between Prime Editing and Older CRISPR Tools?
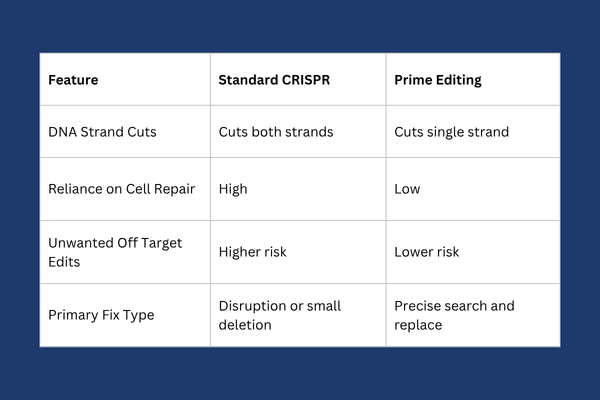
Standard CRISPR acts like a rough-cut tool. It is great for breaking a target gene so it stops working. However, standard CRISPR is less effective at making tiny, precise repairs.
Prime editing acts more like a word processor. It allows scientists to insert new DNA sequences, delete bad sequences, or swap individual chemical letters without causing double-strand breaks.
Key Medical Applications
Scientists are testing prime editing across several major therapeutic areas.
Liver Diseases
The liver is an ideal target for initial genetic treatments. Liver cells readily take up therapeutic delivery vehicles like lipid nanoparticles. Conditions such as alpha-1 antitrypsin deficiency cause toxic proteins to build up in liver cells. Prime editing can target the exact point mutation that causes the bad protein. By correcting the single-letter mistake, liver cells can start making normal, healthy proteins.
Lung Diseases
Lung tissue presents distinct challenges, but new delivery tools are making progress possible. Conditions like cystic fibrosis stem from errors in specific genes that regulate salt and fluid balance in lung tissue. Prime editing can swap out these faulty genetic sequences in lung stem cells. This can restore normal mucus flow and clear airway pathways.
Blood Disorders
Sickle cell disease and beta thalassemia stem from single-letter errors in the hemoglobin gene. Prime editing can rewrite those specific letters back to their healthy form. Because this fix avoids double-strand DNA breaks, it reduces the risk of dangerous chromosome rewiring in blood stem cells.
The Path Through Clinical Trials
Taking a new genetic therapy from the lab to patients requires careful clinical evaluation.
Preclinical Testing: Scientists test the editor in human cells grown in dishes and in animal models. They measure editing efficiency and check for off-target cuts across the whole genome.
Phase 1 Human Trials: A small group of patients receives the treatment. The main goal here is safety. Doctors monitor patients closely to ensure the immune system does not overreact to the editing tools.
Phase 2 Human Trials: Researchers test the therapy in a larger group of patients. They measure efficacy. For liver and lung diseases, doctors test if the organ begins functioning normally and if disease symptoms improve.
Phase 3 Human Trials: Large trials compare the new prime editing therapy against current standards of care. If successful, the therapy moves toward regulatory approval.
Challenges to Overcome
While prime editing holds enormous promise, several technical hurdles remain.
Delivery Mechanisms
Getting the prime editing tools inside the correct human cells remains a key challenge. Researchers use lipid nanoparticles or modified viral vectors to transport the editors. Ensuring these delivery systems reach the lung or liver without causing unwanted inflammation is a major focus of ongoing trials.
Editor Size
Prime editing systems are larger than basic CRISPR systems. The combined molecular machinery includes the nickase protein, the reverse transcriptase enzyme, and the extended guide RNA strand. Packing all these components into a single delivery vector requires advanced engineering.
Editing Efficiency
In some cell types, prime editing works with high efficiency. In non-dividing cells, the efficiency rates can drop. Researchers are tweaking the guide RNA structures and protein enzymes to boost edit success rates across all human tissue types.
Prime editing expands the capabilities of modern genetic medicine by refining how scientists interact with the human genome. Traditional gene editing frameworks often rely on creating double-strand breaks in the DNA backbone. While these early methods successfully disrupt harmful genetic pathways, they rely heavily on unpredictable cellular repair mechanisms that can introduce unwanted insertions, deletions, or structural chromosomal rearrangements. Prime editing avoids these outcomes by acting as a targeted search-and-replace system.
The architecture of a prime editor combines a modified Cas9 protein with a reverse transcriptase enzyme and a custom prime editing guide RNA. The modified Cas9, known as a nickase, cuts only a single strand of the target DNA helix rather than severing both strands completely. The engineered guide RNA performs two vital roles simultaneously: it directs the protein complex to a specific sequence within the genome and provides the fresh template sequence for the repair. Once the guide locates its matching target site and the single strand is nicked, the attached reverse transcriptase reads the new instructions written on the guide RNA and directly synthesizes the corrected DNA strand at the target site. The cell then incorporates this pristine sequence while replacing the original erroneous sequence, correcting single-letter mutations, small deletions, or precise insertions without relying on random cellular repair pathways.
Moving this technology into human clinical applications requires addressing significant biological and engineering demands, particularly surrounding delivery and tissue specificity. In vivo applications depend on delivering large molecular machinery into non-dividing or specialized adult cells. For targeted therapies focusing on the liver and lungs, researchers utilize lipid nanoparticles and viral vectors designed to protect the fragile RNA components until they cross the cellular membrane. Once inside the cytoplasm, the machinery translates into functional proteins, enters the nucleus, and executes the precise rewrite. Clinical studies monitor therapeutic efficacy alongside off-target activity across non-target tissues, ensuring that the prime editor operates solely within designated cellular populations.
Beyond single-organ applications, the broader potential of prime editing includes complex hematologic conditions, muscular dystrophies, and neurodegenerative disorders. Many human genetic diseases stem from point mutations—single nucleotide changes within a sequence of billions of base pairs. Traditional editing methods struggled to repair these point mutations cleanly without leaving behind unwanted genomic scars. By offering pinpoint accuracy, prime editing establishes a foundation for curative therapies that correct root causes rather than managing lifelong symptoms. Ongoing advancements in protein engineering continue to shrink the physical size of the reverse transcriptase domain, improve editing efficiency in quiescent cell types, and optimize guide RNA stability, bringing precise genome surgery closer to standard clinical practice.
For comprehensive background on genome editing protocols and clinical developments, explore research resources available through the National Institutes of Health at https://www.nih.gov.
Looking Ahead
Prime editing represents a major leap forward for genetic medicine. By avoiding double-strand cuts and offering true “search and replace” capability, it opens the door to treating thousands of inherited genetic conditions.
Over the next few years, clinical data from ongoing liver and lung trials will show how safely and effectively this tool operates in humans. If these trials succeed, prime editing could become the new gold standard for precise genomic medicine.
Prime editing is changing how scientists fix broken genes. For years, genetic medicine relied on older CRISPR tools. These older tools work like molecular scissors. Older CRISPR cuts both strands of human DNA at a specific spot. Then, the cell tries to patch the broken DNA back together. This process can create mistakes. It can cause unwanted cuts in other parts of the genome. These mistakes are called off-target effects.
Prime editing is different. It does not cut both strands of the DNA double helix. Instead, it cuts only one single strand. This makes the editing process much safer and more precise.
Right now, prime editing is moving into a major human testing phase. Researchers are running clinical trials to see how well it works inside the human body. Early trial data focuses on diseases affecting the liver and lungs.
Streamline your clinical development, navigate regulatory hurdles, and bring groundbreaking therapies from the lab to the clinic faster. Contact Metis Consulting Services now.