

Prime Editing: Changing How We Fix Broken Genes

This week in the Guardrail, we explore how next-generation gene editing is moving beyond rougher cellular cuts toward surgical precision.
By Michael Bronfman
September 7, 2026
Think of it like a search-and-replace tool for human DNA.
For years, genetic medicine relied on older CRISPR tools. Older CRISPR works like molecular scissors. It cuts both strands of human DNA at a specific spot. Then, the cell tries to patch the broken DNA back together. This process can create mistakes. It can cause unwanted cuts in other parts of the genome. These mistakes are called off-target effects.
Prime editing is different. It does not cut both strands of the DNA double helix. Instead, it cuts only one single strand. This makes the editing process much safer and more precise.
Right now, prime editing is moving into a major human testing phase. Researchers are running clinical trials to see how well it works inside the human body. Early trial data focuses on diseases that affect the liver and the lungs.
How Prime Editing Works
To understand prime editing, it helps to review the main parts of the cell system.
The Target Site
Every cell carries DNA. DNA holds the instructions for life. These instructions are written in four chemical letters. They are A, T, C, and G. Sometimes, a single letter is wrong. That small error can cause a severe genetic disease.
The Search Tool
Prime editing uses a modified protein to find the exact location of the error. The system includes a custom guide sequence. This guide moves through the cell and locks onto the matching spot in the genome.
The Replace Tool
Once the tool finds the target, an enzyme goes to work. This enzyme is a reverse transcriptase. It reads new genetic instructions carried by the prime editing guide. Then, it writes those new letters directly into the target single strand of DNA. The cell integrates this corrected sequence, fixing the original error.
What is the Difference between Prime Editing and Older CRISPR Tools?
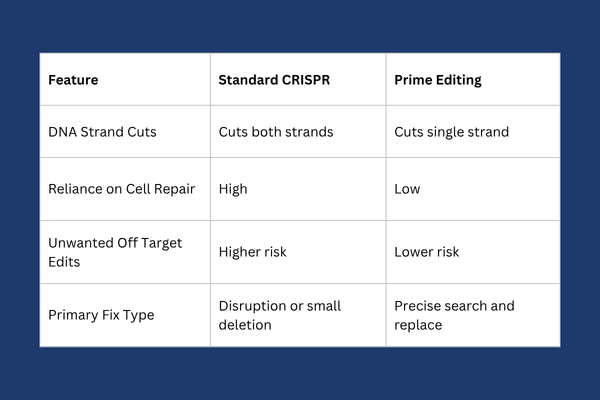
Standard CRISPR acts like a rough-cut tool. It is great for breaking a target gene so it stops working. However, standard CRISPR is less effective at making tiny, precise repairs.
Prime editing acts more like a word processor. It allows scientists to insert new DNA sequences, delete bad sequences, or swap individual chemical letters without causing double-strand breaks.
Key Medical Applications
Scientists are testing prime editing across several major therapeutic areas.
Liver Diseases
The liver is an ideal target for initial genetic treatments. Liver cells readily take up therapeutic delivery vehicles like lipid nanoparticles. Conditions such as alpha-1 antitrypsin deficiency cause toxic proteins to build up in liver cells. Prime editing can target the exact point mutation that causes the bad protein. By correcting the single-letter mistake, liver cells can start making normal, healthy proteins.
Lung Diseases
Lung tissue presents distinct challenges, but new delivery tools are making progress possible. Conditions like cystic fibrosis stem from errors in specific genes that regulate salt and fluid balance in lung tissue. Prime editing can swap out these faulty genetic sequences in lung stem cells. This can restore normal mucus flow and clear airway pathways.
Blood Disorders
Sickle cell disease and beta thalassemia stem from single-letter errors in the hemoglobin gene. Prime editing can rewrite those specific letters back to their healthy form. Because this fix avoids double-strand DNA breaks, it reduces the risk of dangerous chromosome rewiring in blood stem cells.
The Path Through Clinical Trials
Taking a new genetic therapy from the lab to patients requires careful clinical evaluation.
Preclinical Testing: Scientists test the editor in human cells grown in dishes and in animal models. They measure editing efficiency and check for off-target cuts across the whole genome.
Phase 1 Human Trials: A small group of patients receives the treatment. The main goal here is safety. Doctors monitor patients closely to ensure the immune system does not overreact to the editing tools.
Phase 2 Human Trials: Researchers test the therapy in a larger group of patients. They measure efficacy. For liver and lung diseases, doctors test if the organ begins functioning normally and if disease symptoms improve.
Phase 3 Human Trials: Large trials compare the new prime editing therapy against current standards of care. If successful, the therapy moves toward regulatory approval.
Challenges to Overcome
While prime editing holds enormous promise, several technical hurdles remain.
Delivery Mechanisms
Getting the prime editing tools inside the correct human cells remains a key challenge. Researchers use lipid nanoparticles or modified viral vectors to transport the editors. Ensuring these delivery systems reach the lung or liver without causing unwanted inflammation is a major focus of ongoing trials.
Editor Size
Prime editing systems are larger than basic CRISPR systems. The combined molecular machinery includes the nickase protein, the reverse transcriptase enzyme, and the extended guide RNA strand. Packing all these components into a single delivery vector requires advanced engineering.
Editing Efficiency
In some cell types, prime editing works with high efficiency. In non-dividing cells, the efficiency rates can drop. Researchers are tweaking the guide RNA structures and protein enzymes to boost edit success rates across all human tissue types.
Prime editing expands the capabilities of modern genetic medicine by refining how scientists interact with the human genome. Traditional gene editing frameworks often rely on creating double-strand breaks in the DNA backbone. While these early methods successfully disrupt harmful genetic pathways, they rely heavily on unpredictable cellular repair mechanisms that can introduce unwanted insertions, deletions, or structural chromosomal rearrangements. Prime editing avoids these outcomes by acting as a targeted search-and-replace system.
The architecture of a prime editor combines a modified Cas9 protein with a reverse transcriptase enzyme and a custom prime editing guide RNA. The modified Cas9, known as a nickase, cuts only a single strand of the target DNA helix rather than severing both strands completely. The engineered guide RNA performs two vital roles simultaneously: it directs the protein complex to a specific sequence within the genome and provides the fresh template sequence for the repair. Once the guide locates its matching target site and the single strand is nicked, the attached reverse transcriptase reads the new instructions written on the guide RNA and directly synthesizes the corrected DNA strand at the target site. The cell then incorporates this pristine sequence while replacing the original erroneous sequence, correcting single-letter mutations, small deletions, or precise insertions without relying on random cellular repair pathways.
Moving this technology into human clinical applications requires addressing significant biological and engineering demands, particularly surrounding delivery and tissue specificity. In vivo applications depend on delivering large molecular machinery into non-dividing or specialized adult cells. For targeted therapies focusing on the liver and lungs, researchers utilize lipid nanoparticles and viral vectors designed to protect the fragile RNA components until they cross the cellular membrane. Once inside the cytoplasm, the machinery translates into functional proteins, enters the nucleus, and executes the precise rewrite. Clinical studies monitor therapeutic efficacy alongside off-target activity across non-target tissues, ensuring that the prime editor operates solely within designated cellular populations.
Beyond single-organ applications, the broader potential of prime editing includes complex hematologic conditions, muscular dystrophies, and neurodegenerative disorders. Many human genetic diseases stem from point mutations—single nucleotide changes within a sequence of billions of base pairs. Traditional editing methods struggled to repair these point mutations cleanly without leaving behind unwanted genomic scars. By offering pinpoint accuracy, prime editing establishes a foundation for curative therapies that correct root causes rather than managing lifelong symptoms. Ongoing advancements in protein engineering continue to shrink the physical size of the reverse transcriptase domain, improve editing efficiency in quiescent cell types, and optimize guide RNA stability, bringing precise genome surgery closer to standard clinical practice.
For comprehensive background on genome editing protocols and clinical developments, explore research resources available through the National Institutes of Health at https://www.nih.gov.
Looking Ahead
Prime editing represents a major leap forward for genetic medicine. By avoiding double-strand cuts and offering true “search and replace” capability, it opens the door to treating thousands of inherited genetic conditions.
Over the next few years, clinical data from ongoing liver and lung trials will show how safely and effectively this tool operates in humans. If these trials succeed, prime editing could become the new gold standard for precise genomic medicine.
Prime editing is changing how scientists fix broken genes. For years, genetic medicine relied on older CRISPR tools. These older tools work like molecular scissors. Older CRISPR cuts both strands of human DNA at a specific spot. Then, the cell tries to patch the broken DNA back together. This process can create mistakes. It can cause unwanted cuts in other parts of the genome. These mistakes are called off-target effects.
Prime editing is different. It does not cut both strands of the DNA double helix. Instead, it cuts only one single strand. This makes the editing process much safer and more precise.
Right now, prime editing is moving into a major human testing phase. Researchers are running clinical trials to see how well it works inside the human body. Early trial data focuses on diseases affecting the liver and lungs.
Streamline your clinical development, navigate regulatory hurdles, and bring groundbreaking therapies from the lab to the clinic faster. Contact Metis Consulting Services now.
Direct Cellular Engineering
Direct cellular engineering
This week in the Guardrail, we explore how shifting cellular engineering directly inside the human body could eliminate costly manufacturing delays and revolutionize patient access to life-saving treatments. Are you ready to overcome regulatory and delivery hurdles and bring next-generation cell therapies to market faster? Read on.
By Michael Bronfman
August 24, 2026
Traditional cell therapies have achieved extraordinary accomplishments in modern oncology. Chimeric antigen receptor T cell treatments have altered the prognosis for patients suffering from aggressive hematological malignancies like relapsed leukemias, lymphomas, and multiple myeloma. Despite these clinical achievements, the logistical structure of modern cell therapy remains fundamentally constrained.
The current standard of care relies entirely on an autologous ex vivo manufacturing paradigm. Clinicians must harvest T cells from a patient through leukapheresis, transport those living cells to dedicated Good Manufacturing Practice facilities, genetically reprogram them using viral vectors, expand them over several weeks, and deliver them back to the clinical site for reinfusion.
Manufacturing schedules routinely span three to five weeks. This process presents severe bottlenecks. Throughout this waiting window, rapidly progressing disease can cause patient deterioration or mortality before the engineered cells arrive. Intensive labor, stringent quality control, and specialized infrastructure drive treatment prices to hundreds of thousands of dollars per patient, excluding ancillary medical costs for lymphodepleting chemotherapy and prolonged hospital stays.
The Ex Vivo Bottleneck vs The In Vivo Solution
To understand the revolutionary potential of in situ reprogramming, one must examine the structural restrictions inherent to ex vivo cell manufacturing.
Traditional Ex Vivo Pathway
Patient leukapheresis harvesting
Transport to a specialized GMP lab
Viral engineering and gene insertion
Multi-week ex vivo cellular expansion
Transport back to clinic and reinfusion following patient lymphodepletion
In Vivo Pathway
Direct intravenous infusion of targeted vector formulation
Immediate in situ T cell editing within seconds to hours inside the patient's body
Key Differences in Delivery Logistics
Cell Processing Requirements: Ex vivo protocols demand complex cell isolation, activation, viral transduction, and extensive expansion steps outside the body. In vivo protocols utilize an off-the-shelf synthetic formulation or targeted vector that requires no patient-specific cell manipulation.
Therapeutic Turnaround: Traditional manufacturing requires weeks of processing time, during which patients often require bridging therapies to manage disease burden. In vivo vectors can be reconstituted and administered on the same day the treatment decision is made.
Scale and Health Facilities: Current cell therapies are largely restricted to major academic medical centers that manage cell handling, logistics chain, and complex toxicities. In vivo formulations behave like traditional biologic drugs, opening up administration to regional health centers and community hospitals.
Cellular Fitness and Stemness: When T cells are harvested, stimulated, and cultured ex vivo for extended durations, they frequently undergo metabolic stress and premature exhaustion. Cells engineered directly inside the living organism retain their natural physiological state, naive phenotypes, and proliferative potential.
Technical Delivery Platforms
Directing genetic material to specific immune cell subsets within a complex systemic environment requires sophisticated delivery systems that can navigate biological barriers without triggering unwanted off-target effects.
Targeted Lipid Nanoparticles
Lipid nanoparticles, similar to those validated during global mRNA vaccine deployment, serve as a non-viral platform for in vivo reprogramming. Standard LNPs naturally accumulate in the liver due to apolipoprotein E adsorption. To redirect these particles specifically toward T lymphocytes, researchers modify the outer lipid shell with targeted ligands, such as monoclonal antibody fragments or single-chain variable fragments that bind surface receptors like CD3, CD4, or CD5.
The structural makeup consists of:
Outer Shell: Targeted ligands (anti-CD3 or anti-CD5 antibody fragments) and PEGylated lipids for target specificity and stability.
Internal Core: Ionizable lipids and structural phospholipids surrounding the encapsulated payload.
Payload: Messenger RNA encoding the CAR construct or CRISPR-Cas editing machinery.
Once administered intravenously, these surface-modified LNPs recognize circulating and tissue-resident T cells and induce receptor-mediated endocytosis. Inside the cell, the ionizable lipids respond to the acidic endosomal environment, damage the membrane, and release the encapsulated messenger RNA into the cytoplasm.
The cytoplasm then translates the mRNA payload into CAR proteins that translocate to the cell membrane. Because mRNA does not integrate into the genomic DNA, expression is transient, lasting from several days to a few weeks. This time-based control offers a major safety advantage, allowing clinicians to titrate dosage and avoid permanently immune-altered states.
Engineered Viral Vectors
For applications requiring permanent genetic integration, researchers are actively refining pseudotyped viral delivery systems. Standard viral vectors, such as adeno-associated viruses or lentiviruses, exhibit broad tropism and infect various cell types indiscriminately.
To overcome this, engineers mutate the native viral envelope proteins to abolish their natural binding capabilities. They then engineer the viral surface to display targeting domains specific to T cell surface markers.
Receptor-targeted lentiviral vectors can selectively transduce CD8-positive cytotoxic lymphocytes or CD4-positive helper lymphocytes directly within lymph nodes and the spleen. This permanent integration guarantees that as the reprogrammed T cells divide in response to tumor antigens, their daughter cells inherit the CAR gene, providing long-term immunological memory.
In Vivo Site-Specific Genomic Editing
A major milestone in cellular engineering is securing precise gene insertion in vivo without random viral integration. Recent developments use dual-vector platforms that combine enveloped delivery vehicles with adeno-associated viruses to execute site-specific knock-ins directly inside endogenous T cells.
The site-specific knock-in mechanism proceeds through distinct biological phases:
Targeting: Guide RNA directs the Cas9 nuclease to a designated cut site within Exon 1 of the TRAC locus.
Cleavage: Double-strand DNA breaks are introduced precisely at the target site, knocking out the endogenous T cell receptor.
Integration: Homology-directed repair templates insert the synthetic CAR gene sequence into the double-strand break point.
Expression: The integrated CAR gene is transcribed directly under the control of native promoter elements.
Furthermore, conducting this site-specific knockout and knock-in process entirely in vivo preserves T cell stemness. Recent preclinical findings show that T cells engineered inside living tissue express higher levels of stem cell memory markers versus traditional lab-engineered cell products, yielding superior persistence and deeper tumor-clearing capabilities in both hematological and solid tumor models.
Primary Applications and Preclinical Findings
Direct immune cell editing is expanding into wider medical disciplines. Oncology remains the primary target for in vivo CAR technologies.
Hematological Cancers
Primary Target Indications: Leukemias, Lymphomas, Multiple Myeloma
Biological Mechanism: Transient or permanent targeting of CD19 or CD20 on malignant B cell populations
Solid Tumors
Primary Target Indications: Epithelial carcinomas, Glioblastomas
Biological Mechanism: Multi-antigen targeting combined with microenvironment remodeling factors
Autoimmune Diseases
Primary Target Indications: Lupus, Rheumatoid Arthritis
Biological Mechanism: Transient depletion of autoreactive B cells or generation of regulatory T cells
Tissue Fibrosis
Primary Target Indications: Cardiac scarring, Liver cirrhosis
Biological Mechanism: Anti-FAP CARs targeting activated fibroblasts to reverse tissue scarring
Hematological and Solid Tumors
In preclinical models, targeted LNPs delivering anti-CD19 CAR mRNA have rapidly generated functional CAR T populations in circulating blood and lymphatic tissue. These in situ generated cells cleared systemic tumor burdens with efficiency matching or exceeding ex vivo controls.
Dual vector gene insertion strategies target the TRAC locus and achieve therapeutic levels of CAR T cells in vivo, successfully clearing aggressive leukemias and multiple myeloma in humanized animal models with a single systemic injection.
Autoimmune and Fibrotic Diseases
The transient nature of non-viral mRNA delivery makes in vivo CAR generation uniquely suited for non-oncology indications where permanent cell modification is unnecessary or hazardous.
Cardiac and Tissue Fibrosis: Pathological fibrosis in heart disease and liver conditions is driven by overactive, activated fibroblasts expressing Fibroblast Activation Protein. Research using CD5-targeted LNPs carrying anti-FAP CAR mRNA showed that a single systemic infusion could reprogram T cells to selectively eliminate activated fibroblasts, significantly reducing cardiac and hepatic fibrosis and restoring organ function.
Autoimmune Disorders: In severe autoimmune conditions like systemic lupus erythematosus, transient in vivo depletion of the pathogenic B cell population resets the immune system. Once the transient CAR expression dissipates, naive B cells repopulate the compartment without causing permanent humoral immunodeficiency.
Off-Target Transduction and Tissue Tropism
A central safety requirement for overall vector administration is absolute target specificity. If a viral or nanoparticle vector encapsulates or transduces off-target tissues like hepatocytes, endothelial cells, or healthy parenchymal tissue, the host cells may express chimeric antigen receptors on their surface or suffer unintended genetic editing.
To reduce off-target risks, developers use dual-targeting strategies. This includes combining surface antibody functionalization with cell type-specific promoter sequences, making sure that even if a vector enters a non-immune cell, the synthetic genetic payload remains transcriptionally silent.
Academic References
For additional information about the core mechanisms and translational data of in vivo cellular engineering, refer to the following publications:
Volta, L. (2026). In vivo generation of CAR T cells: biology, delivery platforms, clinical promise, and translational challenges. Blood Immunology & Cellular Therapy, 2(1), 100027.
Nyberg, W. A., Bernard, P. L., Ngo, W., et al. (2026). In vivo site-specific engineering to reprogram T cells. Nature, 639, 10235.
Rurik, J. G., Tombácz, I., Yadegari, A., et al. (2022). CAR T cells produced in vivo to treat cardiac injury. Science, 375(6578), 91-96.
Klichinsky, M., Ruella, M., Shestova, O., et al. (2020). Human chimeric antigen receptor macrophages for cancer immunotherapy. Nature Biotechnology, 38(8), 947-953.
To learn more about cellular processing standards and bio manufacturing logistics, explore technical guidelines supplied by the International Society for Cell & Gene Therapy and regulatory insights at the U.S. Food and Drug Administration Cellular & Gene Therapy Products Portal.

Spatial Omics and Single-Cell Biology: Mapping the Next Generation of Precision Therapeutics
Today, we examine how spatial omics and single-cell biology are overcoming the limitations of bulk sequencing by mapping gene activity directly within intact tissue architecture. Discover how this architectural shift is accelerating target discovery, refining biomarker validation, and powering the next generation of precision therapeutics.

This week in the Guardrail… we examine how spatial omics and single-cell biology are overcoming the limitations of bulk sequencing by mapping gene activity directly within intact tissue architecture. Discover how this architectural shift is accelerating target discovery, refining biomarker validation, and powering the next generation of precision therapeutics.
By Michael Bronfman
August 17, 2026
Traditional genomic and transcriptomic analyses have long served as the foundation of biomedical research, yet they carry a fundamental structural limitation. Standard sequencing protocols require researchers to grind up heterogeneous tissue samples to extract their DNA or RNA. While this bulk extraction yields valuable genetic readouts, it completely destroys the spatial architecture of the tissue sample. The homogenization process blends thousands or millions of distinct cells into a single average measurement. This leaves researchers unable to observe how individual cell types were originally organized, how they communicated through local signaling, or how they interacted within their microenvironment.
Spatial transcriptomics and single-cell biology directly overcome this limitation. By enabling scientists to profile gene activity directly within an intact tissue section, these combined methodologies preserve critical spatial coordinates alongside comprehensive molecular signatures. By bridging single-cell sequencing with high-resolution optical imaging, spatial omics maps the exact location of individual cell populations while detailing their corresponding gene expression profiles inside native tissue architecture.
This technical shift is accelerating preclinical research, refining target discovery, and transforming drug development strategies across major therapeutic areas.
The Technological Shift: Moving Beyond Bulk Averages
For decades, drug discovery teams relied heavily on bulk sequencing data to identify therapeutic targets. Bulk measurements, however, routinely mask low-abundance cell populations or localized transcriptional shifts. A candidate drug target that appears minimally expressed across an entire tumor lysate may actually be highly expressed within a localized cluster of aggressive cells at the invasive tumor margin.
Single-cell RNA sequencing introduced higher resolution by isolating individual cells prior to library preparation, enabling researchers to classify distinct cell subtypes and rare phenotypes. Yet, the physical dissociation step required for single-cell RNA sequencing severs extracellular matrix contacts and destroys spatial organization.
Spatial omics platforms bridge this remaining gap. By utilizing spatially barcoded solid-phase capture arrays or multiplexed in situ hybridization, these technologies capture mRNA transcripts directly from intact tissue sections. 1
Transformative Impact Across Key Therapeutic Areas
Integrating spatial profiling into preclinical drug development pipelines provides unprecedented clarity into complex human diseases, directly improving target validation and risk assessment.
Oncology and the Tumor Microenvironment
Cancerous tissue is exceptionally complex, consisting of malignant subclones, infiltrating immune cells, stromal fibroblasts, blood vessels, and dense extracellular matrix components. Spatial omics allows oncology researchers to deconstruct the tumor microenvironment with high spatial resolution.
Immune Exclusion Zones: Spatial profiling explains why checkpoint inhibitors succeed in certain regions of a tumor while failing in others. Researchers can identify physically restricted immune cells trapped within dense fibrotic borders, which prevent them from penetrating the core tumor tissue.
Therapeutic Resistance Niches: Tumor regions located near hypovascularized or hypoxic cores display distinct stress-response signatures. Mapping these microdomains clarifies how localized environments shield malignant subclones from systemically administered therapies.
Tertiary Lymphoid Structures: Identifying the presence, cellular composition, and spatial layout of tertiary lymphoid structures within solid tumors offers strong predictive value for immunotherapy response. This enables clinical teams to stratify patient cohorts more effectively during early clinical trials.
Neuroscience and Structural Brain Mapping
The central nervous system depends entirely on an organized spatial architecture, in which local neuronal circuits govern functional signals. Bulk sequencing of brain tissue offers limited actionable insight into circuit-level pathologies.
Neuronal Circuit Profiling: Spatial transcriptomics maps the complex laminar organization of the cerebral cortex, charting gene signatures across distinct cortical layers and subcortical structures.
Neurodegenerative Pathology Progression: In conditions such as Alzheimer disease or Parkinson disease, pathological features such as amyloid plaques and neurofibrillary tangles form in localized regions. Spatial profiling allows researchers to evaluate transcriptomic shifts occurring in microglial cells and neurons immediately adjacent to these protein aggregates, comparing them directly to distant healthy tissue.
Blood-Brain Barrier Integrity: Mapping the vascular parenchymal interface helps researchers evaluate how local inflammatory signals compromise active transport across the blood-brain barrier. This aids the rational design of central nervous system drug delivery vehicles.
Immunology and Inflammatory Pathology
Immune responses depend on coordinated cellular migration and localized paracrine signaling within specialized tissue structures.
Lymph Node Architecture: Spatial methods map how immune cell subsets, including dendritic cells, helper T cells, and cytotoxic lymphocytes, reorganize within follicular and paracortical regions during antigen presentation or autoimmune activation.
Autoimmune Niches: In chronic inflammatory conditions such as rheumatoid arthritis or Crohn disease, spatial omics identifies local cellular niches that drive tissue damage. This uncovers localized cytokine networks that systemic blood profiling fails to detect.
Integrating Spatial Omics into the Drug Discovery Pipeline
Pharmaceutical R&D organizations are transitioning from bulk tissue profiling to spatially resolved experimental workflows. This workflow integration enhances multiple stages of early drug development.
Target Identification and Validation
By overlaying high-resolution transcript profiling onto tissue histology, discovery teams can verify whether a target is expressed specifically within disease-driving cells or broadly across healthy tissue. Target evaluation at the tissue microdomain level reduces off-target toxicity risks early in discovery.2
Pharmacodynamics and Tissue Distribution
Assessing candidate drug efficacy requires confirming that a therapeutic agent reaches target cells at effective concentrations within complex tissue. Combining spatial transcriptomics with mass spectrometry imaging or spatial proteomics allows research teams to map drug molecule concentration alongside downstream gene expression changes in the exact same tissue section.
Biomarker Discovery for Clinical Stratification
Phase 2 and Phase 3 clinical trial failures frequently stem from unaddressed patient heterogeneity. Analyzing intact patient biopsy tissue reveals spatial biomarkers, such as cell-to-cell proximity scores or immune infiltration indices, that identify patient subgroups most likely to achieve clinical response.3
Comparative Analysis of Primary Spatial Omics Technologies
Modern spatial biology platforms fall into two main technical categories: sequencing-based spatial capture arrays and imaging-based in situ hybridization technologies. Selecting the appropriate technology depends on research goals, resolution requirements, and target gene panel depth.Sequencing-based capture platforms, such as array-based transcript mapping systems, provide unbiased, high-throughput coverage across the entire genome. These systems are ideal for exploratory target discovery where relevant biological pathways are not yet fully defined.
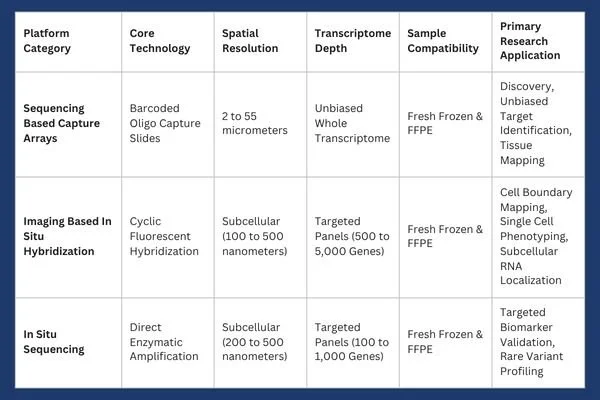
In contrast, imaging based platforms achieve subcellular resolution. These systems utilize targeted fluorescent probe panels to detect individual mRNA molecules within defined cell boundaries. 4
Laboratory Adoption Considerations and Technical Protocols
Successfully establishing a spatial transcriptomics workflow within a biomedical laboratory requires addressing sample preservation, assay selection, and computational data processing infrastructure.
Sample Preparation: FFPE vs Fresh Frozen Tissue
Tissue sample preparation remains a critical variable influencing spatial assay performance.
Fresh Frozen (FF) Tissue: Preserves high-quality RNA integrity, making it optimal for whole transcriptome sequencing-based profiling. However, collecting and preserving fresh frozen samples requires continuous cold-chain storage, which can be difficult to maintain across multisite clinical trial networks.
Formalin Fixed Paraffin Embedded (FFPE) Tissue: Represents the standard preservation format for historical clinical pathology archives. While formalin fixation induces crosslinking and RNA degradation over time, modern probe-based capture chemistries allow robust RNA transcript detection directly from archival FFPE tissue blocks.
Resolution and Multiplexing Tradeoffs
Laboratories must balance transcriptomic breadth against spatial resolution based on specific experimental requirements.
Whole Transcriptome Array Profiling: Measures overall gene expression across thousands of mRNA species across array capture spots. While comprehensive, spatial resolution on standard arrays may encompass multiple adjacent cells per spot, requiring bioinformatic deconvolution to estimate individual cell contributions.
Subcellular Single-Molecule Imaging: Uses targeted, multiplexed probes to achieve resolution down to the hundreds of nanometers. These methods allow direct visualization of intracellular transcript localization within specific organelles or near cell membranes, but require preselecting specific gene-target panels.
Computational Pipelines and Data Scale
Spatial transcriptomics experiments produce extensive datasets combining high-resolution multi-channel image stacks with dense molecular expression matrices. Processing these datasets requires specialized bioinformatic tools capable of handling image registration, cell boundary segmentation, background signal suppression, and spatial neighborhood clustering.
Market Trajectory and Commercial Dynamics
Driven by demand for targeted therapies and precision oncology, the spatial biology market is growing rapidly. Commercial market reports project strong expansion across reagents, instruments, and analytical software through the coming decade.
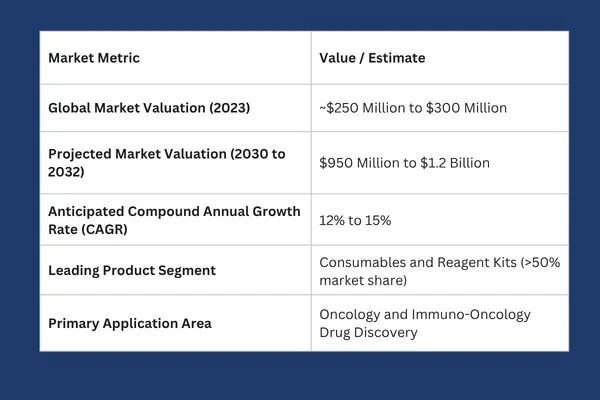
Key drivers powering this commercial expansion include automated tissue-processing instruments, decreasing sequencing costs, improved single-cell segmentation algorithms, and expanding spatial foundation models for automated pathology analysis.
Future Directions: Multimodal Spatial Omics and Artificial Intelligence
The field of spatial biology is rapidly moving beyond single-analyte transcript mapping toward integrated multimodal measurements. Modern experimental platforms enable concurrent spatial profiling of transcripts, functional proteins, epigenetic chromatin accessibility, and small-molecule metabolites within the exact same tissue section.
Concurrently, artificial intelligence models and spatial foundation frameworks are reshaping tissue analytics. Advanced machine learning algorithms can now correlate standard hematoxylin and eosin (H&E) pathology images with underlying spatial gene expression patterns. By training neural networks on matched spatial transcriptomic datasets, researchers can predict localized molecular signatures directly from routine histological slides, unlocking deep biological insight from archival clinical pathology banks.
As these technologies continue to mature and protocol costs decline, spatially resolved biology will evolve from an exploratory research tool into a mandatory standard across pharmaceutical target validation, safety testing, and translational medicine. By preserving the architectural landscape of human tissue, spatial omics is establishing a more accurate foundation for precision drug development.
1 National Library of Medicine, Zhai, Chen & Deng. Researchers can view both the identity of the cell and its exact cellular neighborhood, linking transcriptomic expression directly to tissue histology. pmc.ncbi.nlm.nig.gov
2 Illumina, "What is transcriptomics? A complete guide to gene expression analysis, July 29, 2026. Comprehensive guides on transcriptomic workflows can be found via Illumina transcriptomics overview. illumina.com
3 Atlantis Bioscience, Discovering Solutions for Translational Science. Researchers seeking technical validation tools, reagents, and spatial profiling solutions can explore resources hosted at Atlantis Bioscience. atlantisbioscience.com
4 University of Wisconsin-Madison, Biotechnology Center Gene Expression Core. 10xGenomics Xenium in Situ Spatial Platform. Specialized commercial platforms in this space include the 10x Genomics Xenium in situ platform. biotech.wisc.edu S and the Vizgen MERSCOPE platform. vizgen.com
Our expert advisors accelerate your therapeutic candidates from target validation to clinical triumph. Contact Metis Consulting Services today to integrate cutting-edge spatial transcriptomics and precision workflow strategies into your drug discovery pipeline.

What Acceleration of Development Looks Like in Cell and Gene Therapy
Cell and gene therapy represents some of the most transformative areas of modern medicine. These new and exciting innovations aim to repair, replace, or modify genetic material and cells to treat disease at its root cause.

For Metis Consulting Services
By Michael Bronfman
September 1, 2025
Cell and gene therapy represent some of the most transformative areas of modern medicine. These new and exciting innovations aim to repair, replace, or modify genetic material and cells to treat disease at its root cause. For decades, many conditions, such as certain genetic disorders, advanced cancers, or degenerative diseases, offered few options beyond supportive care. Today, cell and gene therapies are offering new hope. What makes this progress even more remarkable is the speed of development. The acceleration of discovery, design, testing, and approval is unlike any other period in pharmaceutical history.
This article examines how acceleration of development is taking place in cell and gene therapy, why it matters, and what challenges remain.
The Foundation of Acceleration
Progress and practical necessity are forming the foundation of accelerated development in both scientific and. Molecular biology, sequencing technologies, and cell culture methods have all experienced significant advances, reducing the time required to identify disease targets and design therapies. At the same time, patients with life-threatening illnesses cannot afford to wait decades for new treatments. This combination of scientific readiness and urgent medical need has prompted researchers, companies, and regulators to accelerate their efforts.
The path from concept to treatment has traditionally been a slow process. Historically, developing a new pharmaceutical product could take ten to fifteen years. Much of this time was spent in early research, animal testing, and multiple stages of clinical trials. In cell and gene therapy, this timeline has been shortened through better tools, closer collaboration, and more flexible regulatory pathways.
Scientific Tools Driving Speed
One of the most important drivers of acceleration is the set of scientific tools available to researchers. Whole genome sequencing now allows scientists to identify mutations linked to disease in a matter of weeks rather than years. The cost of sequencing has fallen dramatically, which makes it possible to analyze large patient populations and pinpoint the genetic roots of rare conditions.
Gene editing tools such as CRISPR-Cas9 have also transformed development. Before these tools, altering genetic material was complicated, imprecise, and slow. Now, researchers can design edits with remarkable accuracy. This makes it faster to create cell models, test therapeutic approaches, and move into preclinical development.
Advanced cell culture technologies and bioreactors also play a role. Manufacturing therapeutic cells once required painstaking manual methods. Today, automated and scalable systems allow for faster and more consistent production of cells that can be used in therapies.
Collaboration Across Sectors
Acceleration is not only a matter of scientific tools. It also depends on collaboration across sectors. Cell and gene therapy requires expertise from biology, chemistry, engineering, medicine, and regulatory science. Companies have learned that they cannot work in isolation. Instead, partnerships between academic institutions, biotechnology firms, large pharmaceutical companies, and government agencies are essential.
Academic groups often generate the first ideas and proof-of-concept studies. Biotechnology firms then specialize in translating these discoveries into viable products. Large pharmaceutical companies provide resources for clinical trials, manufacturing, and distribution. Regulatory agencies create frameworks that balance safety with speed. Together, these players create an environment in which therapies can progress more quickly than in the past.
Public-private partnerships have been especially valuable. By sharing data, patient registries, and trial results, the entire community reduces duplication of effort and builds collective knowledge. This culture of openness is critical in a field where patient numbers are often small and every dataset matters.
Regulatory Innovation
Another factor in acceleration is regulatory innovation. Traditional drug development was designed for medicines that would be used by millions of patients. Cell and gene therapies are often targeted to rare diseases with small patient populations. Regulators have recognized that the standard framework may not apply in these cases.
In the United States, the Food and Drug Administration has created programs such as the Regenerative Medicine Advanced Therapy Designation. This allows promising therapies to receive closer guidance, rolling review of data, and potential priority review. In Europe, the European Medicines Agency has similar pathways, including the PRIME scheme. These approaches do not remove the requirement for safety and efficacy, but they allow data to be submitted in stages and evaluated more quickly.
Post-marketing commitments are also an important part of the regulatory landscape. Because long-term data may not be available at the time of approval, regulators often allow conditional approval while requiring companies to continue gathering information. This model supports faster access for patients while ensuring continued oversight.
Manufacturing as a Driver of Speed
Manufacturing has traditionally been one of the slowest steps in cell and gene therapy. Producing living cells or viral vectors at clinical and commercial scale is complex. In the early years, many therapies were made almost by hand, which limited capacity and slowed development.
Recent advances are changing this picture. Closed system bioreactors reduce contamination risk and allow for automated production. Improvements in viral vector production yield higher amounts of material in shorter times. Standardization of processes across laboratories and companies also helps reduce delays.
In addition, digital technologies are being used to monitor and optimize manufacturing in real time. This allows rapid adjustments and reduces the likelihood of production failures. Faster and more reliable manufacturing means that clinical trials can begin sooner and scale up more quickly if results are positive.
Patient Engagement
Patients are not simply recipients of cell and gene therapies. They are active participants in the acceleration process. For many rare diseases, patients and advocacy groups are often the driving force behind research funding, trial recruitment, and awareness campaigns.
Engaged patients help researchers design better trials. They provide insight into meaningful outcomes beyond laboratory measurements. They also assist with identifying trial participants, which is especially important when the patient population is very small.
This level of involvement speeds up both the research and the clinical stages. It also ensures that the therapies being developed address real patient needs.
The Role of Data
The acceleration of development is closely tied to the power of data. Electronic health records, genomic databases, and real-world evidence create opportunities to study diseases and track treatment outcomes more efficiently.
Big data approaches allow researchers to identify patterns and predict which patients are most likely to benefit from a given therapy. Adaptive trial designs use data in real time to adjust study parameters, which shortens timelines and increases efficiency.
Data sharing across organizations is also critical. Rare disease research often involves small numbers of patients scattered around the world. Pooling this information accelerates the learning process and reduces duplication of effort.
Case Examples of Accelerated Therapies
Several therapies highlight how accelerated development is reshaping medicine.
Chimeric antigen receptor T cell therapy, known as CAR T therapy, moved from early clinical trials to approval in just a few years. These therapies involve collecting a patient's own T cells, engineering them to attack cancer cells, and reinfusing them. The speed of development was driven by strong clinical results, regulatory flexibility, and urgent patient need.
Another example is gene therapy for spinal muscular atrophy. Once considered untreatable, this disease now has an approved therapy that delivers a functional copy of the defective gene. Development was accelerated by breakthroughs in vector technology, rapid trial enrollment, and close collaboration with regulators.
These examples show that acceleration is not only possible but already happening.
Challenges That Remain
Despite the progress, challenges remain. Safety is always the highest concern. Editing genes or modifying cells carries risks, and long-term monitoring is essential. While acceleration is important, it cannot come at the cost of patient well-being.
Manufacturing and supply chain issues continue to be difficult. Even with improved systems, scaling up to meet demand is not easy. The cost of therapies remains very high, which raises questions about access and sustainability.
Global harmonization is still lacking, even though regulatory pathways are evolving. A therapy could be approved in one region or country and still face delays in others. Greater international coordination could reduce these barriers.
Finally, ethical questions around gene editing and long-term effects require ongoing discussion. Acceleration must be balanced with careful consideration of broader implications.
The Future of Accelerated Development
Looking forward, acceleration of development in cell and gene therapy is likely to continue. New tools such as base editing and prime editing promise even greater precision. Advances in stem cell biology may expand the range of treatable diseases. Manufacturing will become more standardized and less costly.
Regulatory agencies are learning from early experiences and may refine their frameworks to support even faster yet responsible approvals. Global collaboration will likely grow as patient groups, researchers, and companies work across borders.
Ultimately, the greatest measure of acceleration will be patient outcomes. The goal is not speed for its own sake, but faster relief for individuals and families facing devastating conditions. When development accelerates responsibly, it translates into more lives improved and more diseases transformed from untreatable to manageable.
Acceleration of development in cell and gene therapy is one of the most significant trends in modern medicine. The quick progress faster than ever before, is being driven by scientific advances, collaboration, regulatory innovations, improved manufacturing, patient engagement, and the power of data. While challenges remain, the direction is clear. Diseases once thought incurable are now within reach of treatment. The future of medicine will be defined not only by what we can achieve, but also by how quickly we can achieve it responsibly.
The acceleration of development is not simply about speed. It is about building a system that can respond to urgent patient needs, integrate scientific discovery, and deliver safe and effective therapies in record time. Cell and gene therapy demonstrate that this vision is possible and that the future of healthcare is being reshaped today.
As the landscape continues to evolve, staying ahead requires deep expertise and strategic insight. At Metis Consulting Services, we specialize in helping organizations navigate these complexities and harness the full potential of this groundbreaking field.
To learn more about our services and how we can partner with you, please see our website: metisconsultingservices.com or email us at hello@metisconsultingservices.com.

Supply Chain Challenges
In "The Guard Rail" this week, we're diving into a challenge that defines the pharmaceutical and biotech industries: the delicate balance between Time, Quality, and Cost.
For Metis Consulting Services
By Michael Bronfman
August 25, 2025
This week’s Guard Rail discusses one exciting therapeutic area that is changing the world of medicine. at a breakneck pace. We will delve into the unique challenges that distinguish the cell and gene therapy supply chain. From managing delicate cryogenic materials to ensuring that each patient's unique biological material is handled with absolute precision. Mastering this precision is not just a matter of good business; it is a matter of life and death for patients worldwide.
Supply Chain Challenges: Complexities in the Cell and Gene Space
The field of cell and gene therapy has experienced remarkable growth over the last decade. These therapies offer hope to patients with rare diseases, cancers, and other life-threatening conditions that have resisted traditional treatment. Driven by new clinical breakthroughs, the Pharmaceutical industry is racing to develop cell and gene products that can transform healthcare.
These therapies require more complex logistics, specialized facilities, and precise coordination among multiple players than traditional pharmaceuticals. The supply chain is not a linear process of producing pills in a factory and shipping them to pharmacies. It is instead a highly dynamic network that involves human cells, time-sensitive deliveries, and rigorous quality checks. The following discussion examines some of the complexities of the supply chain in the cell and gene therapy space, as well as the critical importance of these issues for the industry.
The Personalized Nature of Therapies
A central difference between cell and gene therapies and conventional drugs lies in the manner in which they are manufactured. Many cell therapies are designed for individual patients. For example, in autologous therapies, cells are collected directly from the patient, modified in a specialized facility, and then returned for infusion back into the same patient. This is a very different model compared to the mass production of tablets or vials.
Supply chains must handle thousands of individualized processes simultaneously, because each product batch is unique. Tracking, labeling, and verifying each sample are vital to avoid mix-ups that could have life-threatening consequences. This personalized model introduces an enormous amount of variability, which makes planning and scaling operations far more challenging than in traditional pharmaceutical manufacturing.
Chain of Identity and Chain of Custody
Two terms often repeated in the industry are chain of identity and chain of custody. The chain of identity ensures that a sample collected from a specific patient remains linked to that same patient throughout the entire process. The chain of custody is the detailed documentation of who handled the product at every stage. This includes where it was transported and under what conditions.
Maintaining that documentation requires advanced tracking technologies, digital platforms, and trained personnel at every handoff. A single error could result in the incorrect therapy being administered to the wrong patient. So the supply chain is one of the most sensitive areas in cell and gene therapy. Digital solutions can provide real-time monitoring and secure tracking across multiple sites, so many companies are investing heavily in this area.
Cold Chain Logistics
Temperature control is one of the most critical components of this supply chain. Many cell and gene therapies are extremely sensitive to temperature changes. Some must be kept at cryogenic temperatures as low as minus 150 degrees Celsius, while others must remain between 2 and 8 degrees Celsius.1Infrastructure Archives - VillageReach
Maintaining these conditions from the point of collection to the point of delivery is a monumental task. Specialized freezers, liquid nitrogen shippers, temperature monitoring sensors, and validated transportation partners are required. Even a short lapse in temperature control can compromise the integrity of the therapy.
Additionally, many therapies cannot be stored for extended periods of time. Their shelf life is often measured in days rather than months. Delays in customs, traffic, or weather can put entire treatments at risk; needless to say, this results in an immense amount of pressure on logistics teams to deliver products quickly and without incident.
Manufacturing Bottlenecks
The manufacturing process adds another layer of complexity. Unlike conventional drugs that are synthesized in bulk, cell and gene therapies require a more intricate set of customized bioprocessing steps.
Currently, the number of facilities capable of performing this type of manufacturing is limited. Capacity constraints create bottlenecks that can delay treatment for patients who may not have time to wait. We need to increase that number, but expanding manufacturing capacity requires significant investment. Increased investments in equipment, in trained personnel, and regulatory compliance. Furthermore, as science evolves rapidly, facilities must remain flexible to adapt to new processes and technologies.
Regulatory Complexity
Regulatory requirements for cell and gene therapies are among the most stringent in health care. Regulators demand extensive data on product safety, identity, purity, and potency. Additionally, every step of the supply chain must be validated and thoroughly documented. This level of oversight increases the already complex nature of operations. Companies must establish quality systems that meet the standards for review, auditing, and high regulatory requirements. They must also ensure that suppliers, logistics providers, and manufacturing partners comply with the same high standards. Achieving and maintaining compliance can slow down operations and add significant costs, but it is necessary to protect patients and maintain trust in the industry. 2Key Skills and Experience to Look for in Pharmaceutical Sales Talent.
Global Supply Chain Challenges
Cell and gene therapies are not limited to one country; clinical trials and treatments often span multiple continents. This creates multiple additional challenges related to transportation regulations, customs, and international quality standards.
For example, shipping cryogenic material across borders requires permits, specialized containers, and coordination with customs officials who may not always be familiar with the time-sensitive nature of such shipments. Variations in regulations between countries add another layer of complexity. A therapy that is approved in one country may face delays or restrictions in another.
These global challenges require close collaboration between regulators, manufacturers, and logistics providers. Standardization of procedures and alignment of regulations could help reduce delays and improve patient access.
Workforce and Training Issues
From laboratory technicians to logistics managers, cell and gene therapies require a highly trained workforce. The specialized nature of these therapies means every person involved must understand the sensitivity of the products and the importance of compliance. Unfortunately, there is a shortage of skilled professionals in this field.3CGT Applications Data Management - BioProcess International.
Recruiting, training, and retaining talent are challenges for most companies. The learning curve is steep, and mistakes can be costly. Additionally, as the industry continues to grow rapidly, competition for skilled workers is intensifying. Building a strong workforce is essential for strengthening the supply chain and ensuring the safe delivery of therapies.
Financial Pressures
The cost of developing and delivering cell and gene therapies is exceptionally high. Manufacturing processes are labor-intensive, facilities are expensive, and logistics require specialized equipment. All of these factors contribute to the high price of these therapies, which can exceed hundreds of thousands or even millions of dollars per patient.4 Zadig, S. M., & Tejay, G. (2012). Emerging Cybercrime Trends. Advances in Information Security, Privacy, and Ethics Book Series.
Every step in the supply chain must be carefully optimized to control costs without compromising safety. Waste reduction, efficiency improvements, and digital automation are key strategies. However, the bespoke nature of Cell and Gene therapies makes it difficult to achieve the economies of scale typically found in traditional pharmaceutical manufacturing.
The Role of Technology and Innovation
Despite these challenges, the forecast in our industry remains optimistic. New technology is significantly improving supply chains. Currently in use or soon to be introduced are digital tracking platforms, blockchain solutions, advanced sensors, and artificial intelligence-driven analytics. New methods to reduce errors and improve efficiency are being explored. Standardized modular facilities are being developed that can be rapidly deployed in different regions.
Automation in manufacturing is also helping to reduce variability and increase throughput. The promise in all of these innovations is creating more resilient supply chains and easing the current bottlenecks.
The Human Element
People place enormous trust in these therapies, often seeing them as their last hope. This reality adds urgency and responsibility to every decision made in the industry.
Healthcare providers, logistics partners, and manufacturers must work together with both compassion and precision. The supply chain in cell and gene therapy is not simply about moving products from one place to another. It is about ensuring that each patient receives the correct treatment at the right time, with no compromises in safety or quality.
The supply chain challenges in the cell and gene therapy space are unlike any seen in the history of medicine. Personalized products, strict regulatory requirements, temperature-sensitive logistics, manufacturing bottlenecks, and global coordination issues create a level of complexity that is unprecedented. At the same time, these therapies hold extraordinary promise. They have the potential to cure diseases that are considered untreatable. This could transform the future of health care.
To realize this potential, the industry must continue to invest in infrastructure, digital solutions, workforce development, and international collaboration. Overcoming supply chain challenges will not only save lives but also improve efficiency and the bottom line. The road ahead is difficult, but with continued innovation and commitment, the cell and gene therapy field can achieve its promise and deliver lasting hope to patients worldwide.
At Metis Consulting Services, we have seen firsthand that the logistics of Cell and Gene therapies are far more intricate than traditional pharmaceuticals. Contact us today to learn how we can help you optimize your operations and accelerate your path to delivering these life-changing therapies to patients. Hello@Metisconsultingservices.com