
High Cholesterol Gone with One Treatment?
Base editing technology is moving beyond rare diseases to potentially eliminate high cholesterol with a single, highly precise genetic intervention. A profound paradigm shift from lifelong daily disease management to permanent, proactive prevention. Read about it this week in the Guardrail, The Power of Gene Editing
By Michael Bronfman
September 14, 2026
Imagine going to the clinic for a single shot and fixing your high cholesterol for the rest of your life. For millions of people worldwide, this sounds almost like magic. However, new medical progress is turning this dream into real science.
In mid 2025, A major pharmaceutical company bought out a smaller biotechnology company called Verve Therapeutics. In order to gain control of some advanced genetic tools. The main focus of this effort is a new experimental drug called VERVE 102.1.1
This drug uses a super precise technology called base editing. Unlike older ways of fixing genes, base editing acts like a tiny spell checker for your DNA. Instead of cutting the DNA strand completely, it neatly changes one single genetic letter. VERVE 102 targets a specific liver gene called PCSK9. By turning off this single gene, the body can clear bad cholesterol from the blood much faster.
As Phase 2 clinical trials expand, scientists and doctors are closely examining how this technology works. They are looking at what makes it safe and how it could completely change how we treat common long-term health conditions.
Understanding the Danger of High Cholesterol
To see why this new treatment is such a big deal, we first need to understand how cholesterol harms the human body.
Your body needs some cholesterol to build healthy cells. But too much of one specific type, called low-density lipoprotein (LDL) cholesterol, creates serious trouble. People often call LDL “bad cholesterol.” When you have high levels of LDL floating through your bloodstream for many years, it builds up inside the walls of your arteries. This buildup turns into hard spots called plaque.
Over time, plaque narrows and stiffens your blood vessels. This condition is known as atherosclerosis. When arteries get clogged, blood cannot flow easily to vital organs. If a piece of plaque breaks open, a blood clot can form quickly. This blockage can cause a sudden heart attack or a stroke. Cardiovascular disease remains the number one cause of death worldwide.
Many people try to lower their bad cholesterol by eating healthy food and exercising regularly. While lifestyle changes are important, they are often not enough. Many people have genes that make their bodies produce far too much cholesterol, no matter what they eat.
For decades, doctors have relied on daily pills called statins. Statins work well for millions of people, but only if they take them every single day. Many patients struggle to take a pill every day for the rest of their lives. Some people experience muscle pain or other side effects from statins. Others take their daily medication, but their bad cholesterol still stays at dangerous levels.
This gap in results is why scientists have been searching for a better, longer-lasting solution.
How PCSK9 Controls Your Cholesterol
To lower cholesterol permanently, scientists had to find the biological switch that controls it in the liver. They found that switch in a protein named PCSK9.
Your liver cells have small receptors on their surface that act like tiny nets. These receptors catch bad LDL cholesterol as it flows through the blood and pull it inside the liver cell to be broken down. After dropping off the cholesterol, the receptor returns to the cell surface to catch more. This recycling system keeps your blood clean.
This is where the PCSK9 protein comes in. PCSK9 binds to those cholesterol receptors and stops them from recycling. Instead of sending the receptor back to the surface, PCSK9 causes the cell to destroy the receptor inside.
When your body makes a lot of PCSK9, you have fewer receptors on your liver cells. Fewer receptors mean bad cholesterol stays in your blood longer.
When your body makes very little PCSK9, your liver cells recycle their receptors over and over again. This pulls huge amounts of bad cholesterol out of your bloodstream.
Years ago, researchers made a surprising discovery while studying people with rare genetic mutations. They found individuals who were born with a broken PCSK9 gene. These people naturally made almost no PCSK9 protein. Surprisingly, they were completely healthy, had extremely low bad cholesterol levels, and almost never developed heart disease.
This discovery proved that humans do not need active PCSK9 to live a healthy life. It gave scientists a clear goal. If they could turn off the PCSK9 gene in adults, they could permanently protect them from heart attacks.
The Evolution of Gene Editing: From Scissors to Spell Checkers
Early attempts to edit human genes used a famous tool called CRISPR-Cas9. Think of original CRISPR as a pair of molecular scissors. It finds a specific spot in your DNA and cuts clear through both strands of the double helix.
While cutting DNA can turn off a faulty gene, “double-strand breaks” bring some risks. When a cell tries to glue the two cut ends of DNA back together, it can sometimes make mistakes. It might accidentally delete a small section of DNA or rearrange pieces erroneously. When treating millions of people for a common illness, doctors need tools that are as safe and precise as possible.
This need for safety led to the innovation of base editing. Developed by researchers like David Liu at Harvard University, base editing is a major leap forward in genetic medicine.2
This need for safety led to the innovation of base editing. Developed by researchers like David Liu at Harvard University, base editing is a major leap forward in genetic medicine.2
Instead of cutting the DNA completely, a base editor works like a pencil and eraser. DNA is made of four chemical bases represented by the letters A, C, G, and T. A base editor travels to a specific spot in the DNA, opens the double strand gently without breaking it, and chemically changes one letter into another.
In VERVE 102, the base editor targets the PCSK9 gene in liver cells. It changes a single A letter to a G letter. This tiny, single-letter change alters the biological instructions just enough to stop the liver cell from producing the PCSK9 protein entirely. Because there are no double-strand cuts, the risk of accidental genetic damage drops significantly.
Inside the Treatment: Delivery via Lipid Nanoparticles
Having a clever genetic editor in a test tube is only half the battle. The biggest challenge in genetic medicine has always been delivery. How do you get the base editor inside millions of liver cells inside a living human body without causing harm?
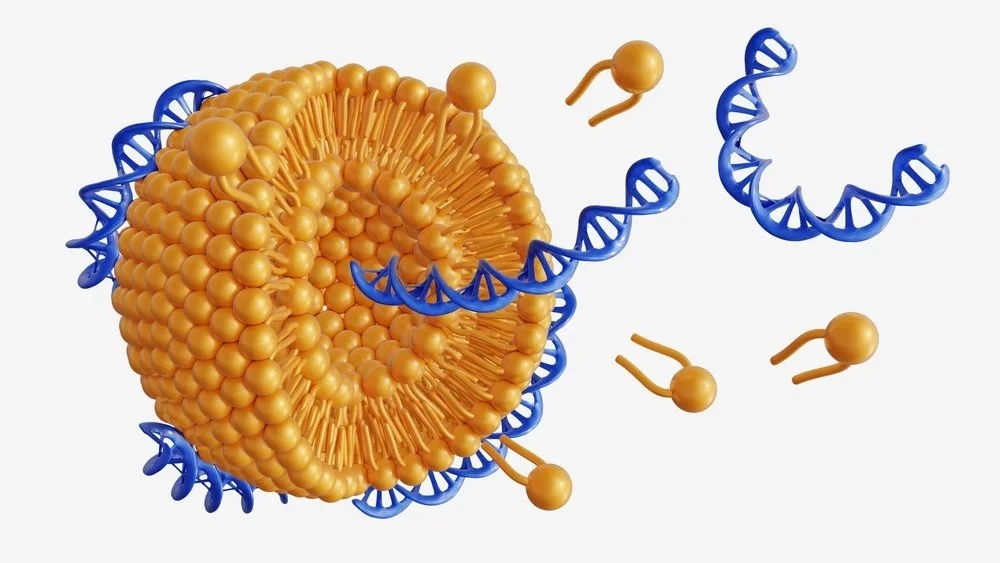
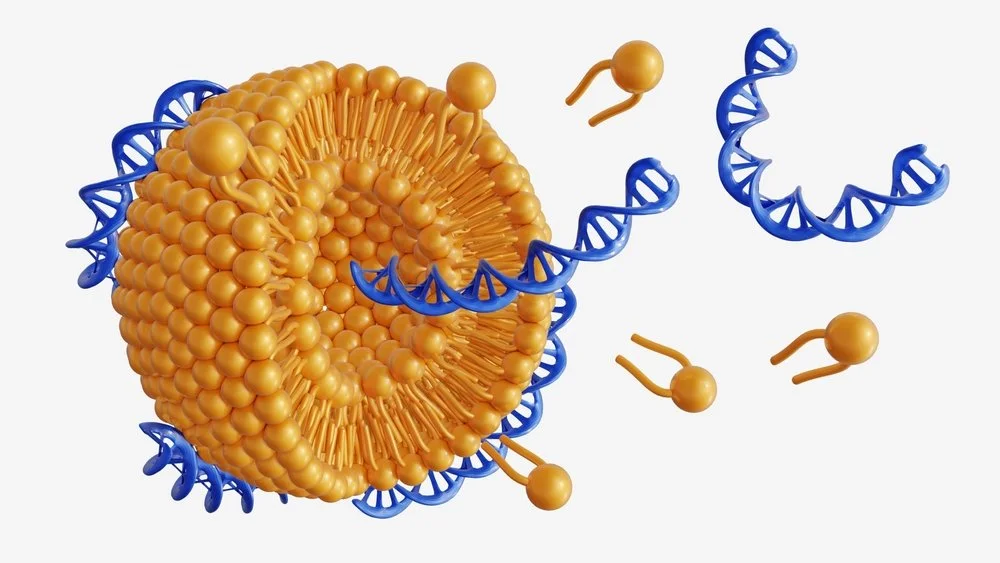
They are solving this by using tiny spheres of fat called lipid nanoparticles, or LNPs. If you received an mRNA vaccine for COVID-19, you are already familiar with lipid nanoparticles. They act like microscopic protective bubbles that carry fragile genetic instructions safely through the bloodstream.
Here is how the treatment works step by step:
- The Dose Preparation: The treatment contains two main components packaged inside the lipid nanoparticle. The first is messenger RNA that tells the cell how to build the base editing protein. The second is a guide RNA that acts like a GPS map, showing the protein exactly where to find the PCSK9 gene. 2.** Simple Infusion:** The patient receives the drug through a simple intravenous, or IV, line in their arm during a standard clinic visit. No surgery, bone marrow removal, or complex hospital stays are required.
- Liver Targeting: The lipid nanoparticles are specially designed with surface molecules that naturally attract them to liver cells. Once injected, they travel through the blood straight to the liver.
- Cell Entry: The liver cells absorb the lipid nanoparticles. Inside the cell, the lipid bubble dissolves, releasing the genetic instructions.
- The Edit: The liver cell uses the mRNA to build the base editor protein. Guided by the guide RNA, the editor enters the cell nucleus, finds the PCSK9 gene, and makes the single-letter change.
- Clean Departure: Once the edit is made, the editor protein and the lipid nanoparticle naturally break down and disappear from the body within a few days. But the change to the DNA remains permanent. Whenever that liver cell divides, its daughter cells inherit the edited, non-working version of the PCSK9 gene.3
Clinical Trial Results and What the Science Shows
The excitement surrounding VERVE 102 comes directly from real clinical data collected in human trials.
Earlier clinical studies testing the first version of this concept showed that base editing could dramatically lower PCSK9 protein levels in humans. However, early delivery methods caused temporary side effects, leading researchers to refine the lipid nanoparticle shell. The updated formulation, VERVE 102, was designed to be gentler on the body while delivering the same powerful genetic edit.
Recent clinical updates show impressive outcomes:
Dramatic Cholesterol Drop: Patients receiving a single high dose of VERVE 102 saw their bad LDL cholesterol levels fall by over 50 to 60 percent.
PCSK9 Shutdown: Measurement of the PCSK9 protein in the blood showed a drop of up to 88 percent, showing that the base editor successfully turned off the targeted gene in most liver cells.
Durable Impact: Follow-up data showed that the reduction in bad cholesterol remained steady over time. Because the edit is made directly to the cell's DNA, the liver continues to produce low cholesterol levels month after month without needing additional doses.
Shifting from Acute Care to Chronic Prevention
For decades, the standard model of medicine has been reactive care. We wait until a person develops high cholesterol or suffers a minor heart event, and then we prescribe a daily pill that they must take for thirty or forty years.
This model has major flaws. First, human behavior is imperfect. Studies show that within one year of being prescribed a daily statin, up to half of all patients stop taking their medication regularly. Life gets busy, prescriptions expire, pills are expensive, and side effects cause people to quit. Every day a patient skips their medication, their risk of a heart attack creeps back up.
Second, chronic care costs healthcare systems a lot. Decades of doctor visits, blood tests, and daily drug refills cost insurance companies, governments, and patients thousands of dollars per year.
Base editing introduces a completely new way of thinking about chronic disease. Scientists call it the "one and done" paradigm. Instead of managing a disease over a lifetime with thousands of pills, a patient receives a single therapeutic intervention that fixes the root cause forever.
If successful in broader Phase 2 and eventual Phase 3 trials, VERVE 102 could transform cardiovascular care from a lifelong burden into a single, proactive medical visit.
Safety and Regulatory Considerations
While the promise of base editing is huge, safety remains the top concern for doctors and regulators alike. When you take a daily pill, you can stop taking it if you experience bad side effects. But when you edit a person's DNA, you cannot hit an undo button. The change is permanent.
Because of this, researchers monitor clinical trial participants very closely for two primary risks:
Off-target Editing
An off-target edit happens if the guide RNA accidentally directs the base editor to the wrong spot in the genome. If the tool alters a healthy, important gene elsewhere in the cell, it could lead to unexpected health problems, including cancer. To prevent this, scientists use advanced computer modeling and deep sequencing to test millions of DNA sites, ensuring the guide RNA only binds to the target gene.
Liver Health and Inflammation
Because the drug delivers lipid nanoparticles directly to the liver, doctors must monitor patients for liver inflammation or temporary spikes in liver enzymes. Clinical trials track blood tests closely after the infusion to verify that the liver remains healthy and functions normally.
Regulatory bodies like the FDA require gene editing candidates to undergo years of careful tracking. Patients in early trials are followed for up to fifteen years to confirm that the editing remains safe and effective over long periods.
Expanding Beyond Cholesterol
Big pharmaceutical companies believe gene editing is ready for common conditions.
In the past, gene therapy was reserved almost exclusively for rare, deadly genetic conditions like sickle cell disease or spinal muscular atrophy. These conditions affect small numbers of people who have no other treatment options. Because the conditions are severe, regulators and patients are willing to accept higher costs and risks. Eli Lilly's acquisition of Verve Therapeutics in mid-2025 signals a major shift away from that model.
High cholesterol affects tens of millions of adults worldwide. By bringing base editing to hyperlipidemia, they are testing whether genetic medicine can scale up to treat common public health problems.
If base editing works safely for high cholesterol, the same platform can be adapted to treat many other long-term health issues:
- High Triglycerides: Editing genes like ANGPTL3 to lower dangerous blood fats.
- Hypertension: Targeting genes involved in blood pressure regulation to permanently lower high blood pressure.
- Type 2 Diabetes: Editing specific liver or pancreas pathways to improve how the body responds to insulin.
- Liver Disease: Turning off genes that cause fat accumulation or scarring in the liver. 4
The Path Ahead
The journey of VERVE 102 through clinical trials is one of the most exciting stories in modern medicine. It represents a shift in how humanity approaches human health. We are moving away from treating symptoms with daily chemicals and moving toward fixing the underlying source code of human disease.
Important questions remain to be answered over the coming years. Will insurance companies cover the upfront cost of a one-time gene editing treatment? How long will the cholesterol-lowering effect last in humans over twenty or thirty years? Will broader trials confirm that side effects remain minimal?
As Phase 2 trials continue to gather data, the scientific world is watching closely. If the results hold true, we may be standing at the beginning of an era where heart attacks become a preventable worry of the past, defeated by a single, precise genetic edit.
Navigating complex regulatory expectations, quality systems, and clinical trial oversight is vital, as gene therapies and advanced precision technologies scale toward mass markets. Contact Metis Consulting Services
Footnotes:
You can read more about how lipid nanoparticles deliver therapies by visiting the National Institutes of Health website.
To explore ongoing research in genetic science and biotechnology, you can visit the World Health Organization website.
To learn more about how clinical trials are designed and monitored for safety, check out the educational resources on the US Food and Drug Administration website.
In Vivo CAR-T Cell Therapy: Rewriting the Rules of Cancer Treatment
This week in the Guardrail, we explore how in vivo CAR-T cell therapy is shifting the paradigm of genetic medicine by reprogramming a patient’s immune system directly inside their body.
By Michael Bronfman
The way we treat cancer is changing fast, and one of the biggest stories in medicine right now is happening inside the human body rather than inside a lab.
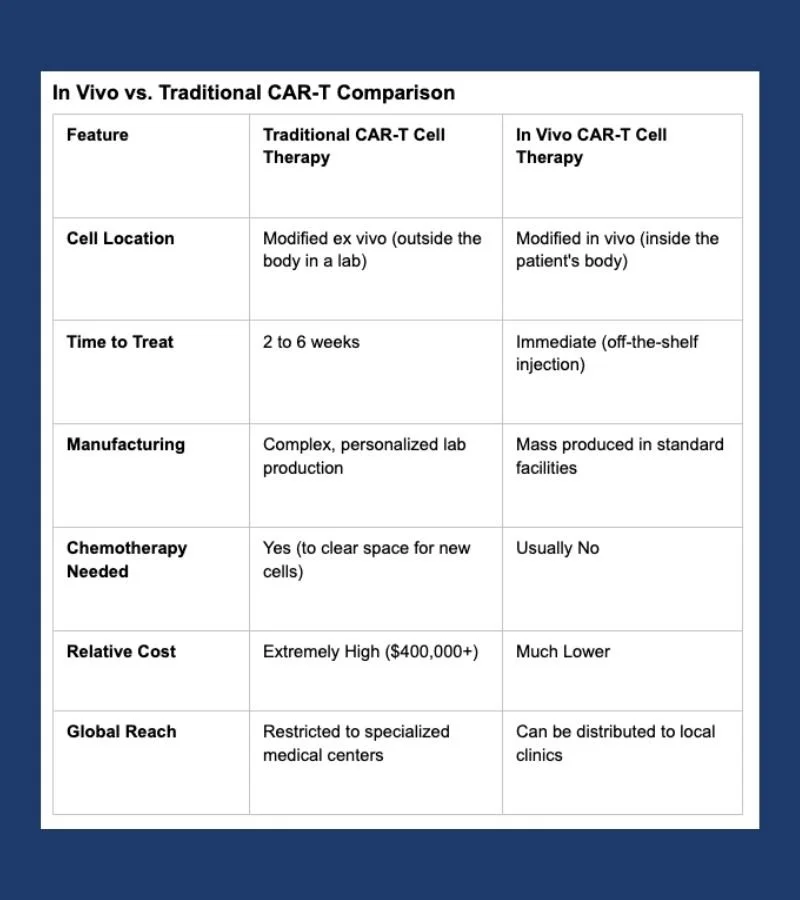
For years, doctors have used a groundbreaking treatment called CAR-T cell therapy to fight stubborn blood cancers. It works by taking a patient's own immune cells, giving them a genetic upgrade, and putting them back into the body to hunt down cancer cells. While this therapy has saved many lives, it is extremely hard to make, takes weeks to process, and costs a fortune.
Now, scientists are testing a new approach called in vivo CAR-T cell therapy. Instead of taking cells out of the body to upgrade them, this new method delivers the genetic instructions directly into the patient with a simple injection. It turns the patient's own body into the laboratory.
If this technology succeeds in human trials, it could make life-saving cancer treatments faster, cheaper, and available to millions of people around the world.
What Is Traditional CAR-T Cell Therapy?
To understand why this new discovery is such a big deal, it helps to look at how traditional CAR-T therapy works.
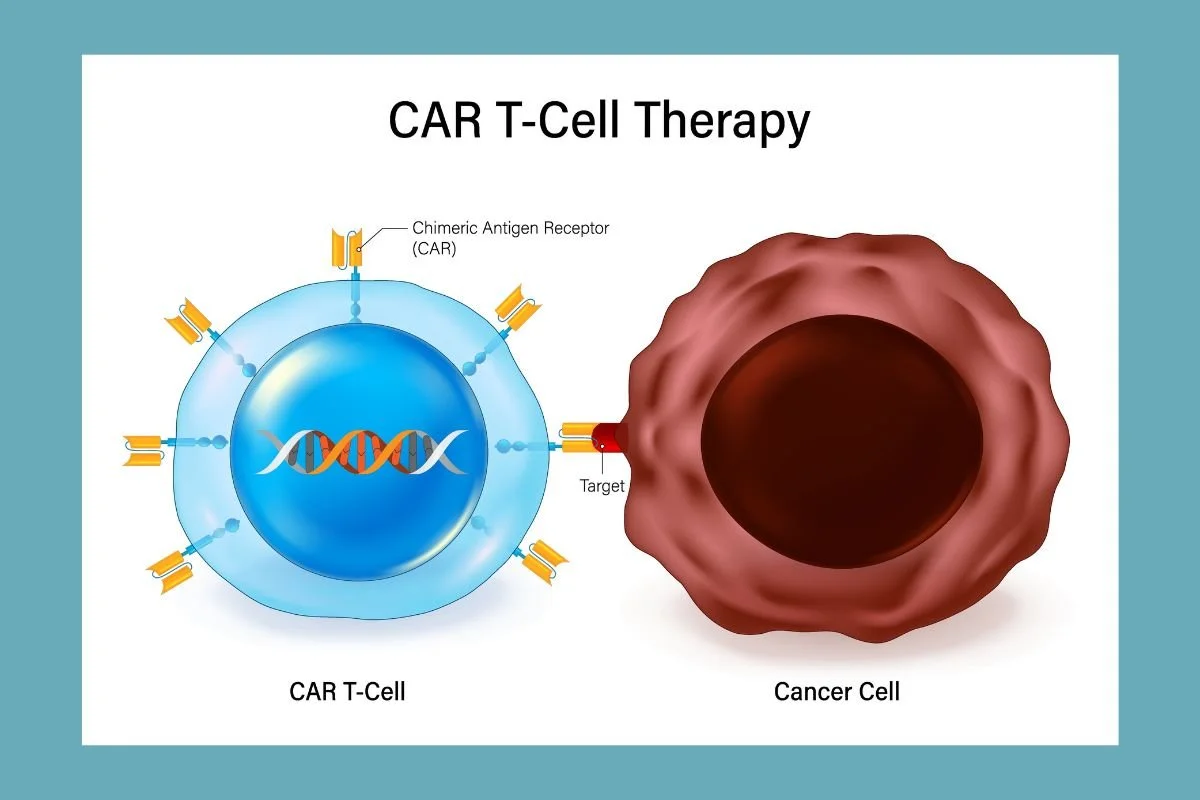
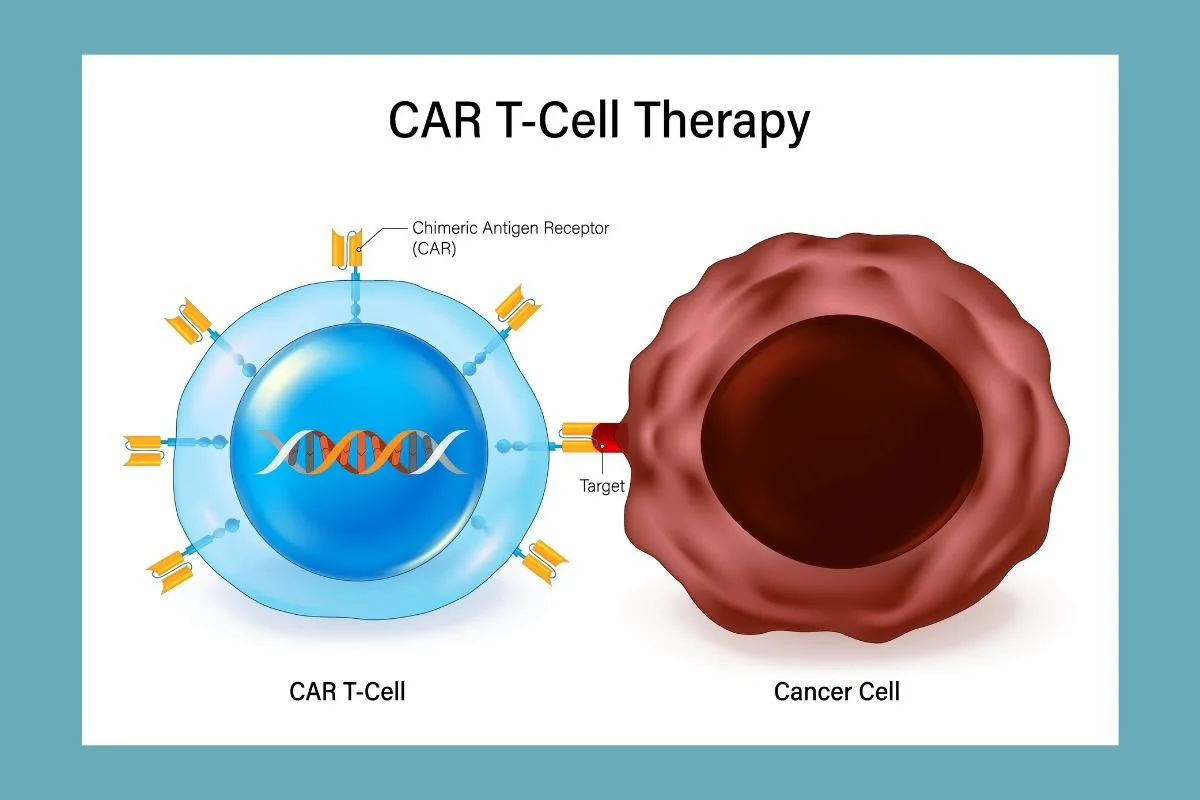
CAR stands for Chimeric Antigen Receptor. T-cells are a type of white blood cell in your immune system. You can think of T-cells as the body's internal security guards. They patrol your bloodstream, looking for infected cells or abnormal cells, and destroy them before they can cause harm.
However, cancer cells are tricky. They often disguise themselves so the immune system cannot see them. To overcome this, scientists figured out a way to retrain T-cells.
Here is the traditional step-by-step process:
Blood Collection: Doctors hook the patient up to a special machine to remove their blood, separate out the T-cells, and return the rest of the blood.
Shipping to a Specialized Lab: The harvested T-cells are frozen and shipped to a high-tech facility known as a Good Manufacturing Practice facility.
Genetic Engineering: In the lab, scientists use a harmless virus to insert a new gene into the T-cells. This gene tells the cells to grow special hooks on their surface called Chimeric Antigen Receptors. These hooks allow the T-cells to lock onto a specific protein found on cancer cells.
Cell Multiplication: The lab grows millions of these upgraded CAR-T cells over several weeks.
Chemotherapy: Before receiving the new cells, the patient goes through chemotherapy to clear out some of their old immune cells and make room for the upgraded ones.
Reinfusion: The new CAR-T cells are shipped back to the hospital and infused into the patient's bloodstream.
Once inside, these engineered T-cells act like guided missiles. They seek out cancer cells, lock onto them with their new receptor hooks, and destroy them.
The Big Problems with Traditional CAR-T
While traditional CAR-T therapy has cleared cancer in patients who had no other options left, the current system has massive drawbacks.
1. Time Limits
Making CAR-T cells outside the body takes anywhere from two to six weeks. For someone with fast-growing leukemia or lymphoma, waiting weeks for a treatment can be dangerous or even fatal.
2. High Costs
Because every batch of CAR-T cells must be custom-made for one specific individual in a sterile lab, the cost is enormous. A single treatment can cost between four hundred thousand and five hundred thousand dollars, not including hospital stays and extra medical care.
3. Complex Logistics
Shipping living human cells across the country under frozen conditions requires advanced temperature-controlled transport. If anything goes wrong during shipping or manufacturing, the batch can be ruined, forcing the patient to start over.
4. Limited Access
Because the process requires specialized hospitals and advanced manufacturing labs, CAR-T therapy is mostly available in wealthy countries and large academic medical centers. Most people in developing nations or rural areas cannot get access to it.
The In Vivo Breakthrough: How It Works
This is where in vivo CAR-T cell therapy comes in. The phrase in vivo means inside the living body. Instead of taking cells out, modifying them in a lab, and putting them back, in vivo therapy delivers the genetic instructions directly into the patient using a single injection.
Scientists do this with special delivery vehicles called nanoparticles or modified viruses.
Here is how the in vivo process works:
Building the Delivery Vehicle: Scientists create tiny bubbles made of fats, known as lipid nanoparticles, or use modified viral shells. Inside these tiny bubbles, they pack genetic instructions written in mRNA or DNA.
Adding the Navigation System: Scientists attach special targeting molecules to the outside of the nanoparticle. These molecules act like a GPS, ensuring the nanoparticle only attaches to T-cells and ignores other cells like liver or lung cells.
Direct Injection: The patient receives a simple IV drip or injection containing these targeted nanoparticles.
Reprogramming Inside the Body: The nanoparticles travel through the bloodstream, attach to the patient's T-cells, and deliver the genetic instructions.
Cancer Hunting: The T-cells read the instructions, start building chimeric antigen receptors on their surface, and immediately begin hunting down cancer cells inside the body.
This simple shift removes the need for cell extraction, lab manufacturing, complex freezing shipping lines, and heavy chemotherapy prep.
What the Research Shows
Recent preclinical studies have shown promising results using in vivo cell engineering.
Research in animal models demonstrates that mRNA delivered by lipid nanoparticles can successfully target T-cells inside living mice. Within days of injection, the mice generated functional CAR-T cells that successfully targeted and shrank tumors.
Researchers are also exploring precise gene editing tools like CRISPR inside the body. Instead of just adding a new gene temporarily, in vivo gene editing can permanently alter the T-cells or remove genes that cause cellular exhaustion, allowing the immune cells to fight cancer longer.
Scientists are publishing new findings regularly on research platforms like Atlantis Bioscience and medical news outlets like STAT News. These studies highlight how in vivo engineering could cut production times from weeks down to zero, turning a custom surgical procedure into an off the shelf pharmacy medication.
Potential Benefits Beyond Cancer
While cancer treatment is the main focus, in vivo CAR-T cell therapy could treat many other diseases.
Autoimmune Diseases: In conditions like lupus or multiple sclerosis, the immune system mistakenly attacks healthy tissue. Scientists are testing CAR-T cells designed to clear out malfunctioning immune cells, effectively resetting the immune system.
Heart Disease: Researchers have used in vivo CAR-T cells in animal models to target and remove scar tissue in damaged hearts, helping restore heart function after a heart attack.
Infectious Diseases: Modified immune cells could be trained to clear out persistent viral infections like HIV that hide inside human tissues.
Organ Transplants: Engineered regulatory immune cells could prevent organ rejection without requiring lifelong immune-suppressing drugs.
Challenges Ahead
While in vivo CAR-T therapy is exciting, scientists still need to solve several technical challenges before it becomes widely available for human patients.
1. Off-Target Effects
The delivery vehicle must be extremely accurate. If a nanoparticle delivers its genetic payload to the wrong cell type, like liver cells or brain cells, it could cause unintended side effects.
2. Overactive Immune Reaction
When CAR-T cells attack cancer cells, they release signal proteins called cytokines. If too many CAR-T cells activate at once inside the body, it can cause a dangerous condition called cytokine release syndrome, which causes high fevers and dangerous drops in blood pressure. Controlling the speed and strength of in vivo reprogramming is vital for safety.
3. Immune Rejection of Delivery Vehicles
The human immune system might spot the nanoparticles or viral vectors and destroy them before they reach the T-cells. Finding materials that can sneak past the body's defenses without causing an allergic reaction requires careful design.
4. Dosing and Control
With traditional CAR-T, doctors know exactly how many modified cells they put back into the patient. With in vivo therapy, it is harder to predict how many T-cells will pick up the gene instructions and how long those instructions will last.
The Road Ahead
In vivo CAR-T cell therapy represents a major shift in modern medicine. By turning the human body into its own medicine factory, scientists are opening the door to a future where genetic treatments are no longer rare luxury procedures reserved for a few, but standard therapies available at local healthcare clinics.
Clinical trials in humans are beginning to take off, testing different delivery vehicles and gene editing tools. Over the next decade, as researchers refine these methods, in vivo cell engineering could fundamentally reshape how we treat cancer, autoimmune conditions, and chronic heart disease.
With Metis Consulting Services you streamline your strategic roadmap, overcome complex regulatory hurdles, and maximize operational efficiency. Contact Metis Consulting Services today
The Real Stakes of Phase 2: You Cannot Afford to Wait
Phase 2 is the ultimate "make or break" moment for drug development and why cutting corners now leads to catastrophic failure later. This Guard Rail blog breaks down the essential risk-mitigation strategies needed to bridge the treacherous gap between initial proof of concept and a successful Phase 3 trial.
This week, we explore why Phase 2 is the ultimate "make or break" moment for drug development and why cutting corners now leads to catastrophic failure later. This Guard Rail blog breaks down the essential risk-mitigation strategies needed to bridge the treacherous gap between initial proof-of-concept and a successful Phase 3 trial.
By Michael Bronfman
In the world of drug development, Phase 2 is often called the "Lands of Proof." This is the moment when a company moves from testing safety in a few healthy people to seeing whether the drug actually works in patients with the disease. It is an exciting time, but it is also the most dangerous part of the journey.
Many teams make the mistake of thinking they can fix small problems later in Phase 3. They might say, "We will figure out the final dose later," or "We will refine the manufacturing process once we have more data." In the pharmaceutical industry, this "wait and see" approach is a recipe for disaster.
Risk mitigation must happen right now. If you do not resolve your biggest uncertainties during Phase 2, you are not just delaying a problem. You are risking billions of dollars and years of hard work.
The Massive Cost of Failure in Phase 3
The jump from Phase 2 to Phase 3 is a giant leap in terms of cost and complexity. While Phase 2 might involve a few hundred patients, Phase 3 often requires thousands.
If a drug fails in Phase 3 because of a risk that could have been identified earlier, the financial hit is devastating. According to reports from Deloitte, the cost to bring a single drug to market has climbed to over two billion dollars.
Most of that money is spent during the final stage. If you enter Phase 3 with a "weak" dose or a "fuzzy" understanding of which patients benefit most, you are gambling with the future of the company. Fixing a mistake in Phase 2 costs thousands. Fixing that same mistake in Phase 3 costs millions.
Solving the Dosage Puzzle
One of the biggest risks in Phase 2 is choosing the wrong dose. This is known as "dose finding."
If the dose is too low, the drug will not show enough benefit, and the trial will fail. If the dose is too high, the side effects might be too many for the government to approve it.
Many companies rush through this. They pick a dose that looks "good enough" so they can start the big trials faster. However, the Food and Drug Administration (FDA) has become much stricter about this. They want to see that you have tested several different doses to find the "sweet spot."
By spending the extra time in Phase 2 to run a robust dose-ranging study, you build a solid foundation. You go into Phase 3 with total confidence that you are giving patients the best possible chance of success.
Identifying the Right Patient Population
Not every patient with a specific disease reacts to a drug the same way. One of the best ways to mitigate risk is to figure out exactly who your "super responders" are.
During Phase 2, researchers look for biomarkers. These are biological signs in the blood or tissue that suggest a patient will respond well to the treatment.
If you ignore these signs and try to test the drug on everyone in Phase 3, your results might get "watered down." The drug might work great for 20 percent of people but not at all for the other 80 percent. If you mix them all together, the average result might look like the drug does not work.
By using Phase 2 to narrow down the target group, you make your Phase 3 trial much smaller, faster, and more likely to succeed. You can find more information on how patient selection impacts trials HERE.
Manufacturing and Supply Chain Hurdles
It is easy to make a small amount of a drug in a lab. It is very hard to make enough for ten thousand people while keeping the quality exactly the same every single time.
A major risk that teams "kick down the road" is the manufacturing process. They use a "Version 1" process for Phase 2 and plan to switch to a "Version 2" for Phase 3.
The problem is that the FDA considers the manufacturing process to be part of the drug itself. If you change how you make the drug, you have to prove that the "new" drug is the same as the "old" drug. This can lead to massive delays or even require you to redo your studies.
Addressing manufacturing risks during Phase 2 ensures that what you test in the final stages is exactly what will be sold in pharmacies. Consistency is the key to safety and approval.
The Regulatory Conversation
You should never treat the government regulators as a surprise at the end of the race. Risk mitigation involves talking to the FDA or the European Medicines Agency early and often.
Phase 2 is the perfect time for an "End of Phase 2" meeting. This is where you present your data and plan to the regulators for the big trial. If they have concerns about your safety data or your goals, you want to know that now.
Waiting until after Phase 3 to find out the FDA does not like your study design is a nightmare scenario. Early transparency reduces the risk of rejection and builds trust with the people who hold the keys to the market.
Protecting the Patients
Beyond the money and the business goals, the most important reason to mitigate risk is the people. Every person who signs up for a clinical trial is a volunteer who wants to help find a cure.
If we move into Phase 3 with known risks that we chose not to solve, we are putting those volunteers at unnecessary risk. We owe it to the patients to be as certain as possible about the safety and the logic behind the study before we ask thousands of people to participate.
High-quality science in Phase 2 leads to safer trials. When we prioritize risk management early, we protect the integrity of the medical profession and the lives of the people we serve.
Key Actions
To ensure a successful transition out of Phase 2, teams should focus on these three pillars:
Data Certainty: Do not settle for "maybe." Use Phase 2 to get clear answers on dose and efficacy.
Process Stability: Finalize how the drug is made and how it will be delivered before the big spend.
Open Dialogue: Work with regulators to make sure the finish line is clearly defined.
The motto for Phase 2 should always be: Fail fast or fix it now. Dealing with the hard truths today is the only way to ensure a breakthrough tomorrow. Waiting to resolve these issues later is not a strategy; it is a gamble that the industry simply cannot afford.
Don’t leave your clinical legacy to chance—master the "Lands of Proof" before the stakes become insurmountable. Contact Metis Consulting Services today to fortify your strategy, optimize your data, and turn your scientific vision into a regulatory reality.
The Australian Advantage in Early Stage Clinical Trials
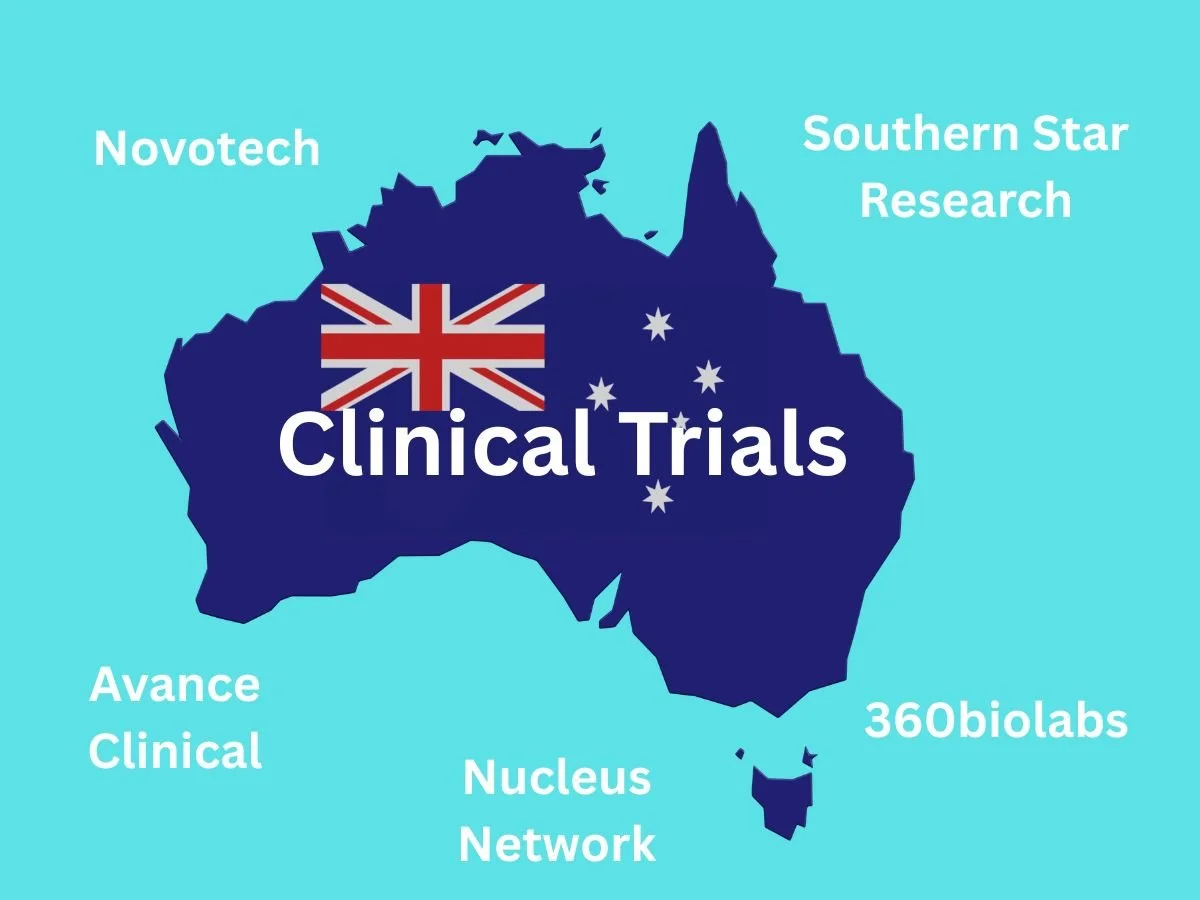
This week in the Guardrail, we explore how the Aussie Advantage-how Australia has leveraged rapid regulatory timelines and aggressive financial incentives to solidify its position as the premier global destination for Phase 1 clinical trials.
By Michael Bronfman
March 30, 2026
When a pharmaceutical company creates a new medicine, the most exciting and scary step is the first time it is given to a human. This is called a “First in Human” or Phase 1 trial. For decades, many companies sent their studies to the United States or Europe. Today, the world is looking at Australia. This country has become a global leader for early-stage clinical trials. In 2026, the "Australian Advantage" is a major topic in the medical world. Here is why so many biotech companies are heading down under to start their research.
Speed Is the Greatest Tool
In the world of medicine, time is everything. If a company can start a trial faster, it can help patients sooner. Australia has a very special system for approving trials that is much faster than that in the United States. In the US, companies must wait months for the Food and Drug Administration to review their plans. In Australia, the process is streamlined.
The Australian system uses a scheme called the Clinical Trial Notification (CTN) scheme. Instead of a long government review, the trial is reviewed by a local ethics committee at a hospital or research center. Once the committee says the trial is safe, the company simply notifies the government. This allows trials to start in just five or six weeks. This speed helps companies save money and move their science forward without waiting for paperwork. You can see how this process works on the Therapeutic Goods Administration website.
A Massive Financial Incentive
Running a clinical trial is very expensive. It can cost millions of dollars to test a new drug. The Australian government wants to help companies do this work in their country. To do this, they offer one of the best tax breaks in the world.
Small and medium companies can get a cash refund of 43.5 percent for every dollar they spend on research in Australia. This means if a company spends one million dollars on a trial, the government gives them back over four hundred thousand dollars in cash. This is not just a tax credit for the future. It is real money that companies can use to fund more research right away. This financial help makes Australia about 60 percent cheaper than the United States for early-stage studies. Many companies use this to stretch their budget and test more ideas.
World Class Quality and Data
Speed and money are important, but they do not matter if the data is not good. Australia is famous for having some of the best doctors and hospitals in the world. The scientists there follow the highest international rules for research. These rules are called Good Clinical Practice.
Because the quality is so high, the data from Australian trials is accepted by major health groups like the US Food and Drug Administration and the European Medicines Agency. A company can conduct its initial tests in Australia and then use the same data to apply for a license in the US or Europe. They do not have to repeat the work. This makes Australia a perfect "launchpad" for global medical development.
A Diverse and Willing Population
For a clinical trial to work, you need people to participate. Australia is a very multicultural country. It has people from many different backgrounds and ethnicities. This is important because medicines can affect different people in different ways. Researchers need a diverse group of people to make sure a drug is safe for everyone.
Australians are also known for being very supportive of medical research. Many people are excited to join trials to help find cures for diseases like cancer or Alzheimer's. There are even special networks, such as the NSW Early Phase Clinical Trials Alliance, that help connect patients with new trials across the country. This makes it much easier for companies to find the volunteers they need.
Advanced Technology and Innovation
In 2026, Australia is at the cutting edge of new medical technologies. They are leaders in areas like gene editing and cell therapy. The labs in cities like Sydney and Melbourne have the latest equipment to study how new drugs work at a microscopic level.
Australian companies and researchers are also using artificial intelligence to help design better trials. This technology helps them predict which patients will respond best to a new treatment. By using the best technology, Australia ensures that every trial is as smart and efficient as possible. Organizations like Novotech help companies from all over the world navigate this high-tech environment.
Seasonal Advantages for Research
One unique advantage of Australia is its location in the Southern Hemisphere. When it is winter in the US and Europe, it is summer in Australia. This is very helpful for testing medicines for seasonal issues like the flu or allergies. Researchers can follow the seasons around the world to keep their studies going year-round. Instead of waiting for next winter in the North, they can simply move their study to the South. This "seasonal bridge" is a clever way to save time in the drug development process.
Strong Protection for Ideas
Companies spend a lot of time and money creating new medicines. They want to be sure that their ideas are safe. Australia has very strong laws to protect intellectual property. This means that when a company brings a new discovery to Australia, they own it completely. They do not have to worry about someone else stealing their hard work. This safety gives business leaders the confidence to bring their most important projects to Australian soil.
The Future of Global Medicine
As we look at the future of public health, Australia will continue to play a big role. The country is not just a place for early tests anymore. It is becoming a hub where the next generation of life-saving cures is born. By making trials faster, cheaper, and higher-quality, Australia is helping the whole world access better medical care.
For a young scientist or a biotech founder, Australia is the place to be in 2026. The combination of government support and scientific excellence is hard to find anywhere else. As more companies realize this, the Australian biotech sector will only continue to grow. BioPharma APAC keeps track of the latest news in the region.
The Australian Advantage is real, and it is growing. By focusing on speed and quality, Australia has made itself the top choice for “first in human” trials. Whether it is the 43.5 percent tax refund or the fast five-week startup time, the benefits are clear. Most importantly, this system helps get new medicines to the people who need them faster than ever before. Australia is proving that you do not have to be the biggest country to be a leader in the world of medicine.
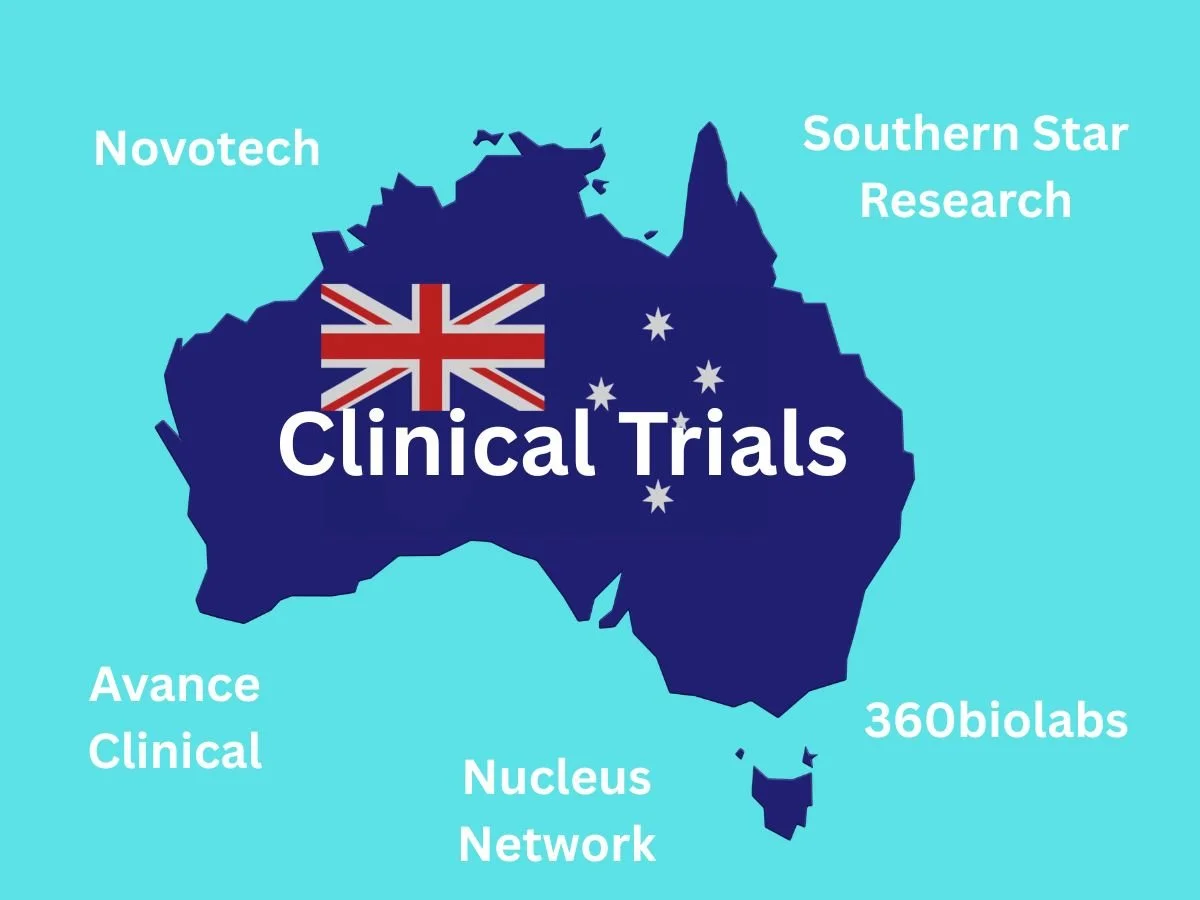
Australia’s Leading Partners for First in Human Clinical Trials
When a biotech company decides to use the Australian Advantage, they usually hire a local expert called a Contract Research Organization ( CRO). These groups handle all the paperwork and find the best hospitals for the study.
Here is a list of the top partners in Australia for early-stage trials in 2026.
1. Novotech
Novotech is the largest independent CRO in the Asia Pacific region. They are experts at helping companies from the United States and Europe move their trials to Australia. They focus on fast startup times and high-quality data.
Specialty: Biotechnology and oncology (cancer) research.
Website: Novotech Health
2. Avance Clinical
Avance Clinical is known for being very agile. They specialize in Phase 1 trials and have a very high success rate with the Australian government’s 43.5 percent tax incentive. They often work with small companies that need to move quickly.
Specialty: Rare diseases and early-stage vaccines.
Website: Avance Clinical
3. Nucleus Network
This group is unique because they have their own dedicated clinics in Melbourne and Brisbane. They have over 150 beds specifically for people participating in First-in-Human trials. This means they do not have to wait for space at a public hospital.
Specialty: Complex Phase 1 studies and healthy volunteer trials.
Website: Nucleus Network
4. Southern Star Research
Southern Star is a boutique CRO based in Sydney. They offer a very personal service for international clients. They are experts in the Clinical Trial Notification (CTN) scheme which allows for that famous five-week trial startup time.
Specialty: Medical devices and respiratory medicine.
Website: Southern Star Research
5. 360biolabs
While the other groups manage the trials, 360biolabs is the leading laboratory in Australia. They test the blood and tissue samples from the trials to see exactly how the new medicine is working. Their data is world-class and accepted by every major global health agency.
Specialty: Specialty laboratory services and virology.
Website: 360biolabs
How to Choose an Australian Partner
Choosing the right partner is the most important decision for a new medical project. Here are three things to look for when researching these groups.
Look for Local Knowledge
A good partner should know the Australian tax system inside and out. They should be able to tell you exactly how to get your 43.5 percent cash refund from the Australian Tax Office. If they cannot explain the finances clearly, they might not be the right fit.
Check Their Track Record
Ask the CRO how many First in Human trials they have managed in the last three years. Speed only matters if the trial is done correctly. You can verify their experience by checking the public database of every trial happening in the region. The Australian New Zealand Clinical Trials Registry.
Verify Their Global Status
Ensure that the CRO has experience working with the US FDA. Since most companies eventually want to sell their medicine in the United States, the Australian data must be perfect. A partner that understands global rules will save you a lot of time later on.
Maximizing the Aussie Advantage requires a global perspective and sophisticated tactical execution. Metis Consulting Services combines deep-seated technical expertise with the strategic capabilities necessary to help you bridge the gap between Australian early-stage success and global regulatory approval.

From Academic Discovery to Clinical Trials: Transitional Priorities
Moving a drug from academic discovery to clinical trials is one of the most critical phases in pharmaceutical development. Academic research often focuses on understanding disease mechanisms and identifying potential targets

This week in the Guardrail, we explore the rigorous journey between bench-side innovation and bedside application. Read the article for the essential regulatory and manufacturing milestones necessary to successfully transition a drug from academic discovery into human clinical trials
By Michael Bronfman
March 9, 2026
Moving a drug from academic discovery to clinical trials is one of the most critical phases in pharmaceutical development. Academic research often focuses on understanding disease mechanisms and identifying potential targets. Translating those discoveries into therapies that can be tested in humans requires careful planning, rigorous validation, and a strong focus on regulatory and operational priorities.
The transition from academic discovery to clinical development is not automatic. Many promising compounds fail to progress because key priorities are overlooked. Companies that understand these priorities can increase the likelihood of successful trials and regulatory approval.
Understanding the Gap Between Discovery and Development
Academic labs are excellent at generating novel ideas and identifying biological targets. However, academic research is usually exploratory. Experiments may be small-scale, conditions controlled, and outcomes focused on understanding mechanisms rather than therapeutic benefit.
Clinical development requires a shift. Compounds must be reproducible, manufacturable, and safe for human testing. Regulatory requirements for documentation, quality, and ethics become central.
Filling this gap requires early planning for pharmacology, toxicology, and chemistry manufacturing and controls, known as CMC.
Establishing a Strong Preclinical Package
Before a drug can enter clinical trials, an extensive preclinical package is essential. Preclinical studies show safety and provide dosing guidance for first-in-human studies.
Key areas include:
Pharmacokinetics and pharmacodynamics, understanding how the drug behaves in the body and its mechanism of action
Toxicology, assessing possible harmful effects in relevant animal models
Formulation and stability, guaranteeing the drug can be reliably manufactured and stored
The FDA provides guidance on preclinical safety evaluation at https://www.fda.gov/regulatory-information/search-fda-guidance-documents/s6r1-preclinical-safety-evaluation-biotechnology-derived-pharmaceuticals
A strong preclinical package increases confidence for regulatory submission and trial planning.
Regulatory Engagement Early and Often
Early engagement with regulators is critical. Discussions with the FDA or EMA can clarify what data is needed to move into clinical trials.
Pre-IND (pre-Investigational New Drug (pre-IND) meetings or Scientific Advice meetings with EMA allow sponsors to present plans and receive feedback. This reduces the risk of surprises during submission review.
Regulatory guidance and meeting information can be found at:
Translating Academic Findings Into Clinical Protocols
Academic studies often use models that may not fully reflect human disease. Translating findings into a clinical protocol calls for careful consideration.
Clinical trial design must define endpoints, patient populations, and dosage regimens. Safety monitoring must be rigorous. Feasibility and patient recruitment plans should be realistic.
Collaboration between discovery scientists, clinical experts, and regulatory professionals ensures that the transition maintains scientific integrity while meeting clinical standards.
Manufacturing and Quality Considerations
Academic labs rarely operate under Good Manufacturing Practice (GMP) standards. Moving into clinical trials requires that compounds be manufactured under controlled conditions.
GMP ensures consistency, purity, and traceability. Sponsors must validate manufacturing processes, control raw materials, and document production.
FDA guidance on GMP requirements is available at
Early attention to manufacturing reduces delays and supports regulatory confidence.
Intellectual Property and Commercial Considerations
Transitioning a compound to clinical trials also demands focus on intellectual property. Patents protect innovations and support investment in development.
Sponsors must assess freedom-to-operate, patent coverage, and potential competitor activity. These considerations impact strategy and partnerships.
Establishing Risk Management Plans
Clinical development entails inherent risk. Safety, efficacy, and operational risks must be identified and mitigated.
Developing a risk management plan includes monitoring safety signals, contingency planning, and guaranteeing compliance with regulatory requirements.
This proactive method supports smooth trial conduct and regulatory inspection readiness.
Building Cross-Functional Teams
Successful transition entails collaboration across multiple disciplines. Discovery scientists, clinical operations, regulatory affairs, quality, and commercial teams must work together.
Effective coordination and mutual objectives avoid misalignment and accelerate progress.
Training and clear role definitions are essential to uphold compliance and accountability.
Patient Considerations and Ethics
Moving from discovery to human trials introduces ethical obligations. Patients must be protected via informed consent, risk minimization, and oversight by institutional review boards or ethics committees.
Clinical study protocols must clearly define inclusion and exclusion criteria, monitoring procedures, and termination rules.
Ethical conduct is mandatory and foundational to regulatory approval.
Timeline Planning and Milestones
Transition planning includes realistic timelines and milestones. From preclinical studies to IND submission and first patient dosing, each stage has dependencies.
Delays frequently occur due to insufficient data, regulatory questions, or manufacturing issues. Detailed planning helps teams foresee obstacles and allocate resources optimally.
Project management tools, milestone tracking, and clear communication reduce bottlenecks and improve efficiency.
Documentation and Data Validity
Data from discovery and preclinical studies must be well documented. Traceability from raw data to reports supports regulatory review and internal decision-making.
Audit-ready records, standardized reporting, and quality checks guarantee that evidence can be defended during inspections.
FDA guidance on data validity can be found at https://www.fda.gov/inspections-compliance-enforcement-and-criminal-investigations
Partnerships and External Expertise
Many organizations rely on external partners to support the transition. Contract research organizations, academic collaborators, and consultants bring specialized expertise.
Sponsors must manage these relationships carefully. Contracts, oversight, and communication plans ensure that responsibilities are clear and quality standards are met.
Glancing Ahead
The transition from academic discovery to clinical trials is a defining phase in drug development. Attention to preclinical data, regulatory engagement, manufacturing, risk management, and team alignment sets the stage for successful clinical programs.
Organizations that plan deliberately, execute rigorously, and sustain compliance are more likely to advance therapies safely and efficiently to patients.
The transition from discovery to development is fraught with complexity, but you don’t have to navigate it alone. Contact Metis Consulting Services today to leverage our deep regulatory expertise and strategic oversight, ensuring your breakthrough therapy moves from the lab to the clinic with precision, speed, and total compliance.