
High Cholesterol Gone with One Treatment?
Base editing technology is moving beyond rare diseases to potentially eliminate high cholesterol with a single, highly precise genetic intervention. A profound paradigm shift from lifelong daily disease management to permanent, proactive prevention. Read about it this week in the Guardrail, The Power of Gene Editing
By Michael Bronfman
September 14, 2026
Imagine going to the clinic for a single shot and fixing your high cholesterol for the rest of your life. For millions of people worldwide, this sounds almost like magic. However, new medical progress is turning this dream into real science.
In mid 2025, A major pharmaceutical company bought out a smaller biotechnology company called Verve Therapeutics. In order to gain control of some advanced genetic tools. The main focus of this effort is a new experimental drug called VERVE 102.1.1
This drug uses a super precise technology called base editing. Unlike older ways of fixing genes, base editing acts like a tiny spell checker for your DNA. Instead of cutting the DNA strand completely, it neatly changes one single genetic letter. VERVE 102 targets a specific liver gene called PCSK9. By turning off this single gene, the body can clear bad cholesterol from the blood much faster.
As Phase 2 clinical trials expand, scientists and doctors are closely examining how this technology works. They are looking at what makes it safe and how it could completely change how we treat common long-term health conditions.
Understanding the Danger of High Cholesterol
To see why this new treatment is such a big deal, we first need to understand how cholesterol harms the human body.
Your body needs some cholesterol to build healthy cells. But too much of one specific type, called low-density lipoprotein (LDL) cholesterol, creates serious trouble. People often call LDL “bad cholesterol.” When you have high levels of LDL floating through your bloodstream for many years, it builds up inside the walls of your arteries. This buildup turns into hard spots called plaque.
Over time, plaque narrows and stiffens your blood vessels. This condition is known as atherosclerosis. When arteries get clogged, blood cannot flow easily to vital organs. If a piece of plaque breaks open, a blood clot can form quickly. This blockage can cause a sudden heart attack or a stroke. Cardiovascular disease remains the number one cause of death worldwide.
Many people try to lower their bad cholesterol by eating healthy food and exercising regularly. While lifestyle changes are important, they are often not enough. Many people have genes that make their bodies produce far too much cholesterol, no matter what they eat.
For decades, doctors have relied on daily pills called statins. Statins work well for millions of people, but only if they take them every single day. Many patients struggle to take a pill every day for the rest of their lives. Some people experience muscle pain or other side effects from statins. Others take their daily medication, but their bad cholesterol still stays at dangerous levels.
This gap in results is why scientists have been searching for a better, longer-lasting solution.
How PCSK9 Controls Your Cholesterol
To lower cholesterol permanently, scientists had to find the biological switch that controls it in the liver. They found that switch in a protein named PCSK9.
Your liver cells have small receptors on their surface that act like tiny nets. These receptors catch bad LDL cholesterol as it flows through the blood and pull it inside the liver cell to be broken down. After dropping off the cholesterol, the receptor returns to the cell surface to catch more. This recycling system keeps your blood clean.
This is where the PCSK9 protein comes in. PCSK9 binds to those cholesterol receptors and stops them from recycling. Instead of sending the receptor back to the surface, PCSK9 causes the cell to destroy the receptor inside.
When your body makes a lot of PCSK9, you have fewer receptors on your liver cells. Fewer receptors mean bad cholesterol stays in your blood longer.
When your body makes very little PCSK9, your liver cells recycle their receptors over and over again. This pulls huge amounts of bad cholesterol out of your bloodstream.
Years ago, researchers made a surprising discovery while studying people with rare genetic mutations. They found individuals who were born with a broken PCSK9 gene. These people naturally made almost no PCSK9 protein. Surprisingly, they were completely healthy, had extremely low bad cholesterol levels, and almost never developed heart disease.
This discovery proved that humans do not need active PCSK9 to live a healthy life. It gave scientists a clear goal. If they could turn off the PCSK9 gene in adults, they could permanently protect them from heart attacks.
The Evolution of Gene Editing: From Scissors to Spell Checkers
Early attempts to edit human genes used a famous tool called CRISPR-Cas9. Think of original CRISPR as a pair of molecular scissors. It finds a specific spot in your DNA and cuts clear through both strands of the double helix.
While cutting DNA can turn off a faulty gene, “double-strand breaks” bring some risks. When a cell tries to glue the two cut ends of DNA back together, it can sometimes make mistakes. It might accidentally delete a small section of DNA or rearrange pieces erroneously. When treating millions of people for a common illness, doctors need tools that are as safe and precise as possible.
This need for safety led to the innovation of base editing. Developed by researchers like David Liu at Harvard University, base editing is a major leap forward in genetic medicine.2
This need for safety led to the innovation of base editing. Developed by researchers like David Liu at Harvard University, base editing is a major leap forward in genetic medicine.2
Instead of cutting the DNA completely, a base editor works like a pencil and eraser. DNA is made of four chemical bases represented by the letters A, C, G, and T. A base editor travels to a specific spot in the DNA, opens the double strand gently without breaking it, and chemically changes one letter into another.
In VERVE 102, the base editor targets the PCSK9 gene in liver cells. It changes a single A letter to a G letter. This tiny, single-letter change alters the biological instructions just enough to stop the liver cell from producing the PCSK9 protein entirely. Because there are no double-strand cuts, the risk of accidental genetic damage drops significantly.
Inside the Treatment: Delivery via Lipid Nanoparticles
Having a clever genetic editor in a test tube is only half the battle. The biggest challenge in genetic medicine has always been delivery. How do you get the base editor inside millions of liver cells inside a living human body without causing harm?
They are solving this by using tiny spheres of fat called lipid nanoparticles, or LNPs. If you received an mRNA vaccine for COVID-19, you are already familiar with lipid nanoparticles. They act like microscopic protective bubbles that carry fragile genetic instructions safely through the bloodstream.
Here is how the treatment works step by step:
- The Dose Preparation: The treatment contains two main components packaged inside the lipid nanoparticle. The first is messenger RNA that tells the cell how to build the base editing protein. The second is a guide RNA that acts like a GPS map, showing the protein exactly where to find the PCSK9 gene. 2.** Simple Infusion:** The patient receives the drug through a simple intravenous, or IV, line in their arm during a standard clinic visit. No surgery, bone marrow removal, or complex hospital stays are required.
- Liver Targeting: The lipid nanoparticles are specially designed with surface molecules that naturally attract them to liver cells. Once injected, they travel through the blood straight to the liver.
- Cell Entry: The liver cells absorb the lipid nanoparticles. Inside the cell, the lipid bubble dissolves, releasing the genetic instructions.
- The Edit: The liver cell uses the mRNA to build the base editor protein. Guided by the guide RNA, the editor enters the cell nucleus, finds the PCSK9 gene, and makes the single-letter change.
- Clean Departure: Once the edit is made, the editor protein and the lipid nanoparticle naturally break down and disappear from the body within a few days. But the change to the DNA remains permanent. Whenever that liver cell divides, its daughter cells inherit the edited, non-working version of the PCSK9 gene.3
Clinical Trial Results and What the Science Shows
The excitement surrounding VERVE 102 comes directly from real clinical data collected in human trials.
Earlier clinical studies testing the first version of this concept showed that base editing could dramatically lower PCSK9 protein levels in humans. However, early delivery methods caused temporary side effects, leading researchers to refine the lipid nanoparticle shell. The updated formulation, VERVE 102, was designed to be gentler on the body while delivering the same powerful genetic edit.
Recent clinical updates show impressive outcomes:
Dramatic Cholesterol Drop: Patients receiving a single high dose of VERVE 102 saw their bad LDL cholesterol levels fall by over 50 to 60 percent.
PCSK9 Shutdown: Measurement of the PCSK9 protein in the blood showed a drop of up to 88 percent, showing that the base editor successfully turned off the targeted gene in most liver cells.
Durable Impact: Follow-up data showed that the reduction in bad cholesterol remained steady over time. Because the edit is made directly to the cell's DNA, the liver continues to produce low cholesterol levels month after month without needing additional doses.
Shifting from Acute Care to Chronic Prevention
For decades, the standard model of medicine has been reactive care. We wait until a person develops high cholesterol or suffers a minor heart event, and then we prescribe a daily pill that they must take for thirty or forty years.
This model has major flaws. First, human behavior is imperfect. Studies show that within one year of being prescribed a daily statin, up to half of all patients stop taking their medication regularly. Life gets busy, prescriptions expire, pills are expensive, and side effects cause people to quit. Every day a patient skips their medication, their risk of a heart attack creeps back up.
Second, chronic care costs healthcare systems a lot. Decades of doctor visits, blood tests, and daily drug refills cost insurance companies, governments, and patients thousands of dollars per year.
Base editing introduces a completely new way of thinking about chronic disease. Scientists call it the "one and done" paradigm. Instead of managing a disease over a lifetime with thousands of pills, a patient receives a single therapeutic intervention that fixes the root cause forever.
If successful in broader Phase 2 and eventual Phase 3 trials, VERVE 102 could transform cardiovascular care from a lifelong burden into a single, proactive medical visit.
Safety and Regulatory Considerations
While the promise of base editing is huge, safety remains the top concern for doctors and regulators alike. When you take a daily pill, you can stop taking it if you experience bad side effects. But when you edit a person's DNA, you cannot hit an undo button. The change is permanent.
Because of this, researchers monitor clinical trial participants very closely for two primary risks:
Off-target Editing
An off-target edit happens if the guide RNA accidentally directs the base editor to the wrong spot in the genome. If the tool alters a healthy, important gene elsewhere in the cell, it could lead to unexpected health problems, including cancer. To prevent this, scientists use advanced computer modeling and deep sequencing to test millions of DNA sites, ensuring the guide RNA only binds to the target gene.
Liver Health and Inflammation
Because the drug delivers lipid nanoparticles directly to the liver, doctors must monitor patients for liver inflammation or temporary spikes in liver enzymes. Clinical trials track blood tests closely after the infusion to verify that the liver remains healthy and functions normally.
Regulatory bodies like the FDA require gene editing candidates to undergo years of careful tracking. Patients in early trials are followed for up to fifteen years to confirm that the editing remains safe and effective over long periods.
Expanding Beyond Cholesterol
Big pharmaceutical companies believe gene editing is ready for common conditions.
In the past, gene therapy was reserved almost exclusively for rare, deadly genetic conditions like sickle cell disease or spinal muscular atrophy. These conditions affect small numbers of people who have no other treatment options. Because the conditions are severe, regulators and patients are willing to accept higher costs and risks. Eli Lilly's acquisition of Verve Therapeutics in mid-2025 signals a major shift away from that model.
High cholesterol affects tens of millions of adults worldwide. By bringing base editing to hyperlipidemia, they are testing whether genetic medicine can scale up to treat common public health problems.
If base editing works safely for high cholesterol, the same platform can be adapted to treat many other long-term health issues:
- High Triglycerides: Editing genes like ANGPTL3 to lower dangerous blood fats.
- Hypertension: Targeting genes involved in blood pressure regulation to permanently lower high blood pressure.
- Type 2 Diabetes: Editing specific liver or pancreas pathways to improve how the body responds to insulin.
- Liver Disease: Turning off genes that cause fat accumulation or scarring in the liver. 4
The Path Ahead
The journey of VERVE 102 through clinical trials is one of the most exciting stories in modern medicine. It represents a shift in how humanity approaches human health. We are moving away from treating symptoms with daily chemicals and moving toward fixing the underlying source code of human disease.
Important questions remain to be answered over the coming years. Will insurance companies cover the upfront cost of a one-time gene editing treatment? How long will the cholesterol-lowering effect last in humans over twenty or thirty years? Will broader trials confirm that side effects remain minimal?
As Phase 2 trials continue to gather data, the scientific world is watching closely. If the results hold true, we may be standing at the beginning of an era where heart attacks become a preventable worry of the past, defeated by a single, precise genetic edit.
Navigating complex regulatory expectations, quality systems, and clinical trial oversight is vital, as gene therapies and advanced precision technologies scale toward mass markets. Contact Metis Consulting Services
Footnotes:
You can read more about how lipid nanoparticles deliver therapies by visiting the National Institutes of Health website.
To explore ongoing research in genetic science and biotechnology, you can visit the World Health Organization website.
To learn more about how clinical trials are designed and monitored for safety, check out the educational resources on the US Food and Drug Administration website.
Direct Cellular Engineering
Direct cellular engineering
This week in the Guardrail, we explore how shifting cellular engineering directly inside the human body could eliminate costly manufacturing delays and revolutionize patient access to life-saving treatments. Are you ready to overcome regulatory and delivery hurdles and bring next-generation cell therapies to market faster? Read on.
By Michael Bronfman
August 24, 2026
Traditional cell therapies have achieved extraordinary accomplishments in modern oncology. Chimeric antigen receptor T cell treatments have altered the prognosis for patients suffering from aggressive hematological malignancies like relapsed leukemias, lymphomas, and multiple myeloma. Despite these clinical achievements, the logistical structure of modern cell therapy remains fundamentally constrained.
The current standard of care relies entirely on an autologous ex vivo manufacturing paradigm. Clinicians must harvest T cells from a patient through leukapheresis, transport those living cells to dedicated Good Manufacturing Practice facilities, genetically reprogram them using viral vectors, expand them over several weeks, and deliver them back to the clinical site for reinfusion.
Manufacturing schedules routinely span three to five weeks. This process presents severe bottlenecks. Throughout this waiting window, rapidly progressing disease can cause patient deterioration or mortality before the engineered cells arrive. Intensive labor, stringent quality control, and specialized infrastructure drive treatment prices to hundreds of thousands of dollars per patient, excluding ancillary medical costs for lymphodepleting chemotherapy and prolonged hospital stays.
The Ex Vivo Bottleneck vs The In Vivo Solution
To understand the revolutionary potential of in situ reprogramming, one must examine the structural restrictions inherent to ex vivo cell manufacturing.
Traditional Ex Vivo Pathway
Patient leukapheresis harvesting
Transport to a specialized GMP lab
Viral engineering and gene insertion
Multi-week ex vivo cellular expansion
Transport back to clinic and reinfusion following patient lymphodepletion
In Vivo Pathway
Direct intravenous infusion of targeted vector formulation
Immediate in situ T cell editing within seconds to hours inside the patient's body
Key Differences in Delivery Logistics
Cell Processing Requirements: Ex vivo protocols demand complex cell isolation, activation, viral transduction, and extensive expansion steps outside the body. In vivo protocols utilize an off-the-shelf synthetic formulation or targeted vector that requires no patient-specific cell manipulation.
Therapeutic Turnaround: Traditional manufacturing requires weeks of processing time, during which patients often require bridging therapies to manage disease burden. In vivo vectors can be reconstituted and administered on the same day the treatment decision is made.
Scale and Health Facilities: Current cell therapies are largely restricted to major academic medical centers that manage cell handling, logistics chain, and complex toxicities. In vivo formulations behave like traditional biologic drugs, opening up administration to regional health centers and community hospitals.
Cellular Fitness and Stemness: When T cells are harvested, stimulated, and cultured ex vivo for extended durations, they frequently undergo metabolic stress and premature exhaustion. Cells engineered directly inside the living organism retain their natural physiological state, naive phenotypes, and proliferative potential.
Technical Delivery Platforms
Directing genetic material to specific immune cell subsets within a complex systemic environment requires sophisticated delivery systems that can navigate biological barriers without triggering unwanted off-target effects.
Targeted Lipid Nanoparticles
Lipid nanoparticles, similar to those validated during global mRNA vaccine deployment, serve as a non-viral platform for in vivo reprogramming. Standard LNPs naturally accumulate in the liver due to apolipoprotein E adsorption. To redirect these particles specifically toward T lymphocytes, researchers modify the outer lipid shell with targeted ligands, such as monoclonal antibody fragments or single-chain variable fragments that bind surface receptors like CD3, CD4, or CD5.
The structural makeup consists of:
Outer Shell: Targeted ligands (anti-CD3 or anti-CD5 antibody fragments) and PEGylated lipids for target specificity and stability.
Internal Core: Ionizable lipids and structural phospholipids surrounding the encapsulated payload.
Payload: Messenger RNA encoding the CAR construct or CRISPR-Cas editing machinery.
Once administered intravenously, these surface-modified LNPs recognize circulating and tissue-resident T cells and induce receptor-mediated endocytosis. Inside the cell, the ionizable lipids respond to the acidic endosomal environment, damage the membrane, and release the encapsulated messenger RNA into the cytoplasm.
The cytoplasm then translates the mRNA payload into CAR proteins that translocate to the cell membrane. Because mRNA does not integrate into the genomic DNA, expression is transient, lasting from several days to a few weeks. This time-based control offers a major safety advantage, allowing clinicians to titrate dosage and avoid permanently immune-altered states.
Engineered Viral Vectors
For applications requiring permanent genetic integration, researchers are actively refining pseudotyped viral delivery systems. Standard viral vectors, such as adeno-associated viruses or lentiviruses, exhibit broad tropism and infect various cell types indiscriminately.
To overcome this, engineers mutate the native viral envelope proteins to abolish their natural binding capabilities. They then engineer the viral surface to display targeting domains specific to T cell surface markers.
Receptor-targeted lentiviral vectors can selectively transduce CD8-positive cytotoxic lymphocytes or CD4-positive helper lymphocytes directly within lymph nodes and the spleen. This permanent integration guarantees that as the reprogrammed T cells divide in response to tumor antigens, their daughter cells inherit the CAR gene, providing long-term immunological memory.
In Vivo Site-Specific Genomic Editing
A major milestone in cellular engineering is securing precise gene insertion in vivo without random viral integration. Recent developments use dual-vector platforms that combine enveloped delivery vehicles with adeno-associated viruses to execute site-specific knock-ins directly inside endogenous T cells.
The site-specific knock-in mechanism proceeds through distinct biological phases:
Targeting: Guide RNA directs the Cas9 nuclease to a designated cut site within Exon 1 of the TRAC locus.
Cleavage: Double-strand DNA breaks are introduced precisely at the target site, knocking out the endogenous T cell receptor.
Integration: Homology-directed repair templates insert the synthetic CAR gene sequence into the double-strand break point.
Expression: The integrated CAR gene is transcribed directly under the control of native promoter elements.
Furthermore, conducting this site-specific knockout and knock-in process entirely in vivo preserves T cell stemness. Recent preclinical findings show that T cells engineered inside living tissue express higher levels of stem cell memory markers versus traditional lab-engineered cell products, yielding superior persistence and deeper tumor-clearing capabilities in both hematological and solid tumor models.
Primary Applications and Preclinical Findings
Direct immune cell editing is expanding into wider medical disciplines. Oncology remains the primary target for in vivo CAR technologies.
Hematological Cancers
Primary Target Indications: Leukemias, Lymphomas, Multiple Myeloma
Biological Mechanism: Transient or permanent targeting of CD19 or CD20 on malignant B cell populations
Solid Tumors
Primary Target Indications: Epithelial carcinomas, Glioblastomas
Biological Mechanism: Multi-antigen targeting combined with microenvironment remodeling factors
Autoimmune Diseases
Primary Target Indications: Lupus, Rheumatoid Arthritis
Biological Mechanism: Transient depletion of autoreactive B cells or generation of regulatory T cells
Tissue Fibrosis
Primary Target Indications: Cardiac scarring, Liver cirrhosis
Biological Mechanism: Anti-FAP CARs targeting activated fibroblasts to reverse tissue scarring
Hematological and Solid Tumors
In preclinical models, targeted LNPs delivering anti-CD19 CAR mRNA have rapidly generated functional CAR T populations in circulating blood and lymphatic tissue. These in situ generated cells cleared systemic tumor burdens with efficiency matching or exceeding ex vivo controls.
Dual vector gene insertion strategies target the TRAC locus and achieve therapeutic levels of CAR T cells in vivo, successfully clearing aggressive leukemias and multiple myeloma in humanized animal models with a single systemic injection.
Autoimmune and Fibrotic Diseases
The transient nature of non-viral mRNA delivery makes in vivo CAR generation uniquely suited for non-oncology indications where permanent cell modification is unnecessary or hazardous.
Cardiac and Tissue Fibrosis: Pathological fibrosis in heart disease and liver conditions is driven by overactive, activated fibroblasts expressing Fibroblast Activation Protein. Research using CD5-targeted LNPs carrying anti-FAP CAR mRNA showed that a single systemic infusion could reprogram T cells to selectively eliminate activated fibroblasts, significantly reducing cardiac and hepatic fibrosis and restoring organ function.
Autoimmune Disorders: In severe autoimmune conditions like systemic lupus erythematosus, transient in vivo depletion of the pathogenic B cell population resets the immune system. Once the transient CAR expression dissipates, naive B cells repopulate the compartment without causing permanent humoral immunodeficiency.
Off-Target Transduction and Tissue Tropism
A central safety requirement for overall vector administration is absolute target specificity. If a viral or nanoparticle vector encapsulates or transduces off-target tissues like hepatocytes, endothelial cells, or healthy parenchymal tissue, the host cells may express chimeric antigen receptors on their surface or suffer unintended genetic editing.
To reduce off-target risks, developers use dual-targeting strategies. This includes combining surface antibody functionalization with cell type-specific promoter sequences, making sure that even if a vector enters a non-immune cell, the synthetic genetic payload remains transcriptionally silent.
Academic References
For additional information about the core mechanisms and translational data of in vivo cellular engineering, refer to the following publications:
Volta, L. (2026). In vivo generation of CAR T cells: biology, delivery platforms, clinical promise, and translational challenges. Blood Immunology & Cellular Therapy, 2(1), 100027.
Nyberg, W. A., Bernard, P. L., Ngo, W., et al. (2026). In vivo site-specific engineering to reprogram T cells. Nature, 639, 10235.
Rurik, J. G., Tombácz, I., Yadegari, A., et al. (2022). CAR T cells produced in vivo to treat cardiac injury. Science, 375(6578), 91-96.
Klichinsky, M., Ruella, M., Shestova, O., et al. (2020). Human chimeric antigen receptor macrophages for cancer immunotherapy. Nature Biotechnology, 38(8), 947-953.
To learn more about cellular processing standards and bio manufacturing logistics, explore technical guidelines supplied by the International Society for Cell & Gene Therapy and regulatory insights at the U.S. Food and Drug Administration Cellular & Gene Therapy Products Portal.

Spatial Omics and Single-Cell Biology: Mapping the Next Generation of Precision Therapeutics
Today, we examine how spatial omics and single-cell biology are overcoming the limitations of bulk sequencing by mapping gene activity directly within intact tissue architecture. Discover how this architectural shift is accelerating target discovery, refining biomarker validation, and powering the next generation of precision therapeutics.

This week in the Guardrail… we examine how spatial omics and single-cell biology are overcoming the limitations of bulk sequencing by mapping gene activity directly within intact tissue architecture. Discover how this architectural shift is accelerating target discovery, refining biomarker validation, and powering the next generation of precision therapeutics.
By Michael Bronfman
August 17, 2026
Traditional genomic and transcriptomic analyses have long served as the foundation of biomedical research, yet they carry a fundamental structural limitation. Standard sequencing protocols require researchers to grind up heterogeneous tissue samples to extract their DNA or RNA. While this bulk extraction yields valuable genetic readouts, it completely destroys the spatial architecture of the tissue sample. The homogenization process blends thousands or millions of distinct cells into a single average measurement. This leaves researchers unable to observe how individual cell types were originally organized, how they communicated through local signaling, or how they interacted within their microenvironment.
Spatial transcriptomics and single-cell biology directly overcome this limitation. By enabling scientists to profile gene activity directly within an intact tissue section, these combined methodologies preserve critical spatial coordinates alongside comprehensive molecular signatures. By bridging single-cell sequencing with high-resolution optical imaging, spatial omics maps the exact location of individual cell populations while detailing their corresponding gene expression profiles inside native tissue architecture.
This technical shift is accelerating preclinical research, refining target discovery, and transforming drug development strategies across major therapeutic areas.
The Technological Shift: Moving Beyond Bulk Averages
For decades, drug discovery teams relied heavily on bulk sequencing data to identify therapeutic targets. Bulk measurements, however, routinely mask low-abundance cell populations or localized transcriptional shifts. A candidate drug target that appears minimally expressed across an entire tumor lysate may actually be highly expressed within a localized cluster of aggressive cells at the invasive tumor margin.
Single-cell RNA sequencing introduced higher resolution by isolating individual cells prior to library preparation, enabling researchers to classify distinct cell subtypes and rare phenotypes. Yet, the physical dissociation step required for single-cell RNA sequencing severs extracellular matrix contacts and destroys spatial organization.
Spatial omics platforms bridge this remaining gap. By utilizing spatially barcoded solid-phase capture arrays or multiplexed in situ hybridization, these technologies capture mRNA transcripts directly from intact tissue sections. 1
Transformative Impact Across Key Therapeutic Areas
Integrating spatial profiling into preclinical drug development pipelines provides unprecedented clarity into complex human diseases, directly improving target validation and risk assessment.
Oncology and the Tumor Microenvironment
Cancerous tissue is exceptionally complex, consisting of malignant subclones, infiltrating immune cells, stromal fibroblasts, blood vessels, and dense extracellular matrix components. Spatial omics allows oncology researchers to deconstruct the tumor microenvironment with high spatial resolution.
Immune Exclusion Zones: Spatial profiling explains why checkpoint inhibitors succeed in certain regions of a tumor while failing in others. Researchers can identify physically restricted immune cells trapped within dense fibrotic borders, which prevent them from penetrating the core tumor tissue.
Therapeutic Resistance Niches: Tumor regions located near hypovascularized or hypoxic cores display distinct stress-response signatures. Mapping these microdomains clarifies how localized environments shield malignant subclones from systemically administered therapies.
Tertiary Lymphoid Structures: Identifying the presence, cellular composition, and spatial layout of tertiary lymphoid structures within solid tumors offers strong predictive value for immunotherapy response. This enables clinical teams to stratify patient cohorts more effectively during early clinical trials.
Neuroscience and Structural Brain Mapping
The central nervous system depends entirely on an organized spatial architecture, in which local neuronal circuits govern functional signals. Bulk sequencing of brain tissue offers limited actionable insight into circuit-level pathologies.
Neuronal Circuit Profiling: Spatial transcriptomics maps the complex laminar organization of the cerebral cortex, charting gene signatures across distinct cortical layers and subcortical structures.
Neurodegenerative Pathology Progression: In conditions such as Alzheimer disease or Parkinson disease, pathological features such as amyloid plaques and neurofibrillary tangles form in localized regions. Spatial profiling allows researchers to evaluate transcriptomic shifts occurring in microglial cells and neurons immediately adjacent to these protein aggregates, comparing them directly to distant healthy tissue.
Blood-Brain Barrier Integrity: Mapping the vascular parenchymal interface helps researchers evaluate how local inflammatory signals compromise active transport across the blood-brain barrier. This aids the rational design of central nervous system drug delivery vehicles.
Immunology and Inflammatory Pathology
Immune responses depend on coordinated cellular migration and localized paracrine signaling within specialized tissue structures.
Lymph Node Architecture: Spatial methods map how immune cell subsets, including dendritic cells, helper T cells, and cytotoxic lymphocytes, reorganize within follicular and paracortical regions during antigen presentation or autoimmune activation.
Autoimmune Niches: In chronic inflammatory conditions such as rheumatoid arthritis or Crohn disease, spatial omics identifies local cellular niches that drive tissue damage. This uncovers localized cytokine networks that systemic blood profiling fails to detect.
Integrating Spatial Omics into the Drug Discovery Pipeline
Pharmaceutical R&D organizations are transitioning from bulk tissue profiling to spatially resolved experimental workflows. This workflow integration enhances multiple stages of early drug development.
Target Identification and Validation
By overlaying high-resolution transcript profiling onto tissue histology, discovery teams can verify whether a target is expressed specifically within disease-driving cells or broadly across healthy tissue. Target evaluation at the tissue microdomain level reduces off-target toxicity risks early in discovery.2
Pharmacodynamics and Tissue Distribution
Assessing candidate drug efficacy requires confirming that a therapeutic agent reaches target cells at effective concentrations within complex tissue. Combining spatial transcriptomics with mass spectrometry imaging or spatial proteomics allows research teams to map drug molecule concentration alongside downstream gene expression changes in the exact same tissue section.
Biomarker Discovery for Clinical Stratification
Phase 2 and Phase 3 clinical trial failures frequently stem from unaddressed patient heterogeneity. Analyzing intact patient biopsy tissue reveals spatial biomarkers, such as cell-to-cell proximity scores or immune infiltration indices, that identify patient subgroups most likely to achieve clinical response.3
Comparative Analysis of Primary Spatial Omics Technologies
Modern spatial biology platforms fall into two main technical categories: sequencing-based spatial capture arrays and imaging-based in situ hybridization technologies. Selecting the appropriate technology depends on research goals, resolution requirements, and target gene panel depth.Sequencing-based capture platforms, such as array-based transcript mapping systems, provide unbiased, high-throughput coverage across the entire genome. These systems are ideal for exploratory target discovery where relevant biological pathways are not yet fully defined.
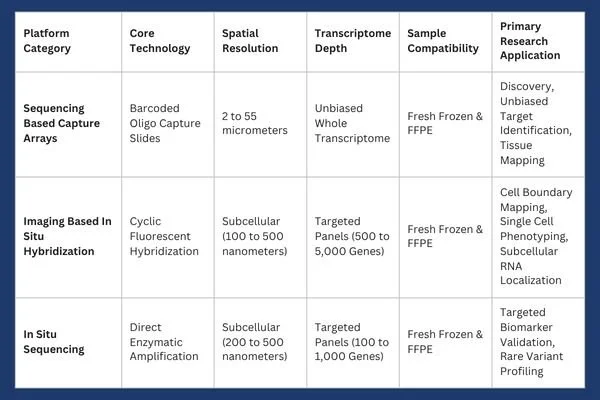
In contrast, imaging based platforms achieve subcellular resolution. These systems utilize targeted fluorescent probe panels to detect individual mRNA molecules within defined cell boundaries. 4
Laboratory Adoption Considerations and Technical Protocols
Successfully establishing a spatial transcriptomics workflow within a biomedical laboratory requires addressing sample preservation, assay selection, and computational data processing infrastructure.
Sample Preparation: FFPE vs Fresh Frozen Tissue
Tissue sample preparation remains a critical variable influencing spatial assay performance.
Fresh Frozen (FF) Tissue: Preserves high-quality RNA integrity, making it optimal for whole transcriptome sequencing-based profiling. However, collecting and preserving fresh frozen samples requires continuous cold-chain storage, which can be difficult to maintain across multisite clinical trial networks.
Formalin Fixed Paraffin Embedded (FFPE) Tissue: Represents the standard preservation format for historical clinical pathology archives. While formalin fixation induces crosslinking and RNA degradation over time, modern probe-based capture chemistries allow robust RNA transcript detection directly from archival FFPE tissue blocks.
Resolution and Multiplexing Tradeoffs
Laboratories must balance transcriptomic breadth against spatial resolution based on specific experimental requirements.
Whole Transcriptome Array Profiling: Measures overall gene expression across thousands of mRNA species across array capture spots. While comprehensive, spatial resolution on standard arrays may encompass multiple adjacent cells per spot, requiring bioinformatic deconvolution to estimate individual cell contributions.
Subcellular Single-Molecule Imaging: Uses targeted, multiplexed probes to achieve resolution down to the hundreds of nanometers. These methods allow direct visualization of intracellular transcript localization within specific organelles or near cell membranes, but require preselecting specific gene-target panels.
Computational Pipelines and Data Scale
Spatial transcriptomics experiments produce extensive datasets combining high-resolution multi-channel image stacks with dense molecular expression matrices. Processing these datasets requires specialized bioinformatic tools capable of handling image registration, cell boundary segmentation, background signal suppression, and spatial neighborhood clustering.
Market Trajectory and Commercial Dynamics
Driven by demand for targeted therapies and precision oncology, the spatial biology market is growing rapidly. Commercial market reports project strong expansion across reagents, instruments, and analytical software through the coming decade.
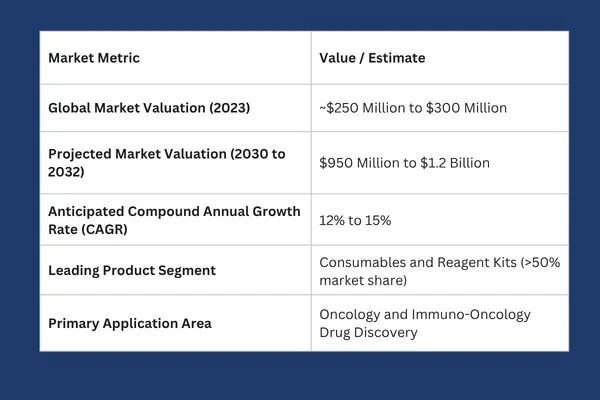
Key drivers powering this commercial expansion include automated tissue-processing instruments, decreasing sequencing costs, improved single-cell segmentation algorithms, and expanding spatial foundation models for automated pathology analysis.
Future Directions: Multimodal Spatial Omics and Artificial Intelligence
The field of spatial biology is rapidly moving beyond single-analyte transcript mapping toward integrated multimodal measurements. Modern experimental platforms enable concurrent spatial profiling of transcripts, functional proteins, epigenetic chromatin accessibility, and small-molecule metabolites within the exact same tissue section.
Concurrently, artificial intelligence models and spatial foundation frameworks are reshaping tissue analytics. Advanced machine learning algorithms can now correlate standard hematoxylin and eosin (H&E) pathology images with underlying spatial gene expression patterns. By training neural networks on matched spatial transcriptomic datasets, researchers can predict localized molecular signatures directly from routine histological slides, unlocking deep biological insight from archival clinical pathology banks.
As these technologies continue to mature and protocol costs decline, spatially resolved biology will evolve from an exploratory research tool into a mandatory standard across pharmaceutical target validation, safety testing, and translational medicine. By preserving the architectural landscape of human tissue, spatial omics is establishing a more accurate foundation for precision drug development.
1 National Library of Medicine, Zhai, Chen & Deng. Researchers can view both the identity of the cell and its exact cellular neighborhood, linking transcriptomic expression directly to tissue histology. pmc.ncbi.nlm.nig.gov
2 Illumina, "What is transcriptomics? A complete guide to gene expression analysis, July 29, 2026. Comprehensive guides on transcriptomic workflows can be found via Illumina transcriptomics overview. illumina.com
3 Atlantis Bioscience, Discovering Solutions for Translational Science. Researchers seeking technical validation tools, reagents, and spatial profiling solutions can explore resources hosted at Atlantis Bioscience. atlantisbioscience.com
4 University of Wisconsin-Madison, Biotechnology Center Gene Expression Core. 10xGenomics Xenium in Situ Spatial Platform. Specialized commercial platforms in this space include the 10x Genomics Xenium in situ platform. biotech.wisc.edu S and the Vizgen MERSCOPE platform. vizgen.com
Our expert advisors accelerate your therapeutic candidates from target validation to clinical triumph. Contact Metis Consulting Services today to integrate cutting-edge spatial transcriptomics and precision workflow strategies into your drug discovery pipeline.

Background of the Breakthroughs of mRNA
By Michael Bronfman, June 23, 2025

Dr. Katalin Kariko, Nobel Prize winning scientist, mRNA vaccine pioneer
This week, The Guard Rail is diving into a topic that has truly revolutionized modern medicine: Messenger RNA, or mRNA. What was once merely a fascinating concept in biology has rapidly become a groundbreaking platform, and its incredible success in the COVID-19 vaccine development is just the beginning. Join us as we explore the captivating scientific journey of mRNA, highlighting the decades of innovation in molecular biology, chemistry, and nanotechnology that led to its triumph. We will also spotlight the key innovators who made it all possible, with a special nod to the remarkable influence of Dr. Katalin Karikó and Dr. Drew Weissman and peek into the exciting future promise of mRNA-based therapeutics.
The Arrival of a New Therapeutic Frontier
Messenger RNA (mRNA) has rapidly transitioned from a biological curiosity to a revolutionary platform in medicine. Its recent triumph—vaccine success against COVID-19—stemmed from decades of incremental yet transformative molecular biology, chemistry, and nanotechnology breakthroughs.
1. From Molecular Discovery to Therapeutic Aspiration
1961 – mRNA Identified
Scientists first recognized mRNA as the key intermediary transmitting genetic information from DNA to ribosomes. This discovery laid the molecular foundation for engineering mRNA for therapeutic use.
1990 – Synthetic mRNA Demonstrated
Jon A. Wolff and colleagues injected synthetic mRNA into mouse muscle, successfully producing proteins in vivo—an early hint at mRNA's therapeutic potential. See: time.com+3penntoday.upenn.edu+3science.org+3en.wikipedia.org+4en.wikipedia.org+4en.wikipedia.org+4.
Despite the promise, these pioneering experiments raised fundamental obstacles: mRNA's inherent fragility, strong immunogenicity, and inefficient cellular delivery.
2. Cracking the Code: Reducing Immunogenicity via Nucleoside Modification
1997–1998 – The Penn Collaboration Begins
At the University of Pennsylvania, biochemist Katalin Karikó and immunologist Drew Weissman formed a partnership driven by a shared interest in harnessing mRNA. See: nature.com+15bu.edu+15teenvogue.com+15.
2005 – Seminal Discovery
They revealed that unmodified synthetic mRNA activates Toll‑like receptors in dendritic cells, triggering inflammation. Crucially, swapping out uridine with pseudouridine (or other modified nucleosides) dramatically suppressed this response, mitigating immunogenicity and enhancing protein translation. See: jbiomedsci.biomedcentral.com+15nobelprize.org+15jci.org+15.
These findings marked a watershed—chemical modification of mRNA transformed it into a viable therapeutic candidate, earning the duo the 2023 Nobel Prize in Physiology or Medicine. See: en.wikipedia.org+3time.com+3nobelprize.org+3
3. Packaging Success: Lipid Nanoparticles Enable Delivery
Origins from siRNA Therapeutics
Before mRNA use, lipid nanoparticle (LNP) technology had been trialed for siRNA drug delivery and achieved FDA approval in 2018 with Onpattro. See: pubmed.ncbi.nlm.nih.gov+15en.wikipedia.org+15statnews.com+15.
Development of mRNA-LNP Systems
Research in the late 2000s and 2010s refined LNP formulations tailored to shield mRNA from degradation, enable cellular entry, and facilitate efficient endosomal escape. See: mdpi.compubs.rsc.org.
Notable innovations include ionizable lipids, helper lipids, cholesterol, and PEGylated lipids, collectively optimizing pharmacokinetics, stability, and safety. See: mdpi.com.
Clinical Translation
This chemistry and engineering synergy culminated in the approval and deployment of the first lipid nanoparticle-based mRNA vaccines during the COVID-19 pandemic.
4. Pre-Pandemic Explorations
Even before 2020, mRNA therapeutics were under active development:
Cancer Vaccines: Preclinical and early clinical trials featured mRNA encoding tumor-specific antigens delivered via LNPs to prime anti‑tumor immunity.
Infectious Disease Vaccines: mRNA vaccines targeting rabies, Zika, influenza, and HIV entered early human trials, demonstrating both feasibility and promise. See: arxiv.org+3teenvogue.com+3wired.com+3.
Protein Replacement and Gene Editing: Applications using LNP-delivered mRNA for protein replacement therapies and CRISPR editing emerged in preclinical stages. See: mdpi.com+2pmc.ncbi.nlm.nih.gov+2pubs.rsc.org+2.
Pioneering Companies: Moderna (founded 2010) and BioNTech (2008) both built platforms centered on Karikó/Weissman technology and LNPs. BioNTech later partnered with Pfizer to develop its COVID-19 vaccine regimen.
5. The COVID‑19 Catalyst & Rapid Deployment
When SARS-CoV‑2 emerged in early 2020, the platform's modular nature and advanced formulations enabled unprecedented speed:
Fast Translation: Within days of the SARS‑CoV‑2 genome release, Moderna and Pfizer‑BioNTech initiated vaccine development. See: penntoday.upenn.edu+9nature.com+9en.wikipedia.org+9.
Clinical Trials: Moderna began human trials in March 2020. By December, both mRNA‑1273 (Moderna) and BNT162b2 (Pfizer‑BioNTech) secured Emergency Use Authorization based on ~95% efficacy. See: nature.com.
This success validated decades of incremental innovation: nucleoside-modified mRNA + optimized LNPs = real-world impact.
6. Recognition: The Nobel and Beyond
The scientific community honored Karikó and Weissman's pivotal contributions:
2023 Nobel Prize: Awarded "for their discoveries concerning nucleoside base modifications that enabled the development of effective mRNA vaccines against COVID‑19". See: statnews.comtime.com+6en.wikipedia.org+6time.com+6.
Media Spotlight: Wired even labeled it "the beginning of an mRNA vaccine revolution". See: penntoday.upenn.edu+3wired.com+3en.wikipedia.org+3.
7. Beyond Vaccination: Broadening the mRNA Horizon
The mRNA platform's adaptability has ignited diverse research avenues:
Infectious Diseases: Ongoing trials for HIV, influenza, RSV, CMV, EBV, and even pan-coronavirus vaccines. See: teenvogue.com+1frontiersin.org+1.
Cancer Therapies: Personalized mRNA vaccines targeting neoantigens, mRNA‑encoded cytokines, and CAR-T therapies are progressing in clinical evaluation.
Gene Editing & Protein Replacement: mRNA-driven CRISPR approaches for in vivo editing, and LNP-encoded enzyme replacement therapies (e.g., for genetic disorders) are expanding mdpi.com+1jbiomedsci.biomedcentral.com+1.
Neurological Disorders: Research is underway to deliver mRNA across the blood‑brain barrier—potentially addressing Alzheimer's, Parkinson's, and others mdpi.com+2teenvogue.com+2theguardian.com+2.
Autoimmunity & Regenerative Medicine: Early-stage efforts are exploring mRNA-induced immune tolerance and tissue regeneration applications.
8. Continued Innovation & Challenges
Despite remarkable success, key areas require continued innovation:
Delivery Precision: Next-gen LNPs (e.g., organ-selective or SORT nanoparticles) aim to enable tissue-specific targeting beyond the liver en.wikipedia.org+1arxiv.org+1.
Stability & Design Optimization: Advanced methods like codon optimization and structure-prediction algorithms (e.g., LinearDesign) enhance mRNA stability and translational efficiency arxiv.org.
Manufacturing Scale & Supply: Scaling up mRNA and LNP production, maintaining cold chain logistics, and ensuring global access remain formidable obstacles wired.com+1mdpi.com+1.
Safety & Regulation: Comprehensive long-term safety monitoring—especially with novel ionizable lipids and repeated dosing—is critical pmc.ncbi.nlm.nih.gov.
Cost & Accessibility: Ensuring equitable pricing and widespread distribution, especially to low- and middle-income countries, remains essential.
9. Timeline of Key Milestones
Year Breakthrough
1961 Discovery of mRNA
1990 Synthetic mRNA expression in mice
1997–98 Karikó & Weissman collaboration begins
2005 Pseudouridine‑modified mRNA suppresses immune activation
2018 FDA approves LNP‑siRNA therapy Onpattro
2020 First mRNA COVID‑19 vaccine trials and rollout
2023 Nobel Prize for Karikó & Weissman
10. In Conclusion: A Platform Reborn
The mRNA story is a testament to scientific persistence, collaboration, and cumulative innovation. From a molecular curiosity to a global vaccine solution, the ascent of mRNA illustrates how challenges—fragility, immunogenicity, delivery—were methodically overcome with modified nucleosides and precision lipid carriers.
The result? A modular, adaptable therapeutic platform poised to revolutionize vaccines, cancer therapy, gene editing, and more. Let this narrative serve both as a chronicle of what has been achieved and a roadmap for what's next in the pharma world.
Your Organization and bench-to-bedside Drug Development with Metis Consulting Services
The groundbreaking advancements in mRNA technology demonstrate the power of specialized expertise and meticulous scientific guidance in navigating complex drug development landscapes. Just as decades of dedicated research led to the mRNA revolution, your next therapeutic breakthrough requires seasoned insight and strategic direction.
Don't leave your innovative drug development projects to chance. Let Metis Consulting Services help to leverage unparalleled expertise in navigating the intricate pathways of pharmaceutical research and development. We provide comprehensive guidance, from early-stage discovery to clinical translation, ensuring your projects are optimized for success.
Contact Metis Consulting Services today to unlock the full potential of your drug development pipeline and turn scientific aspirations into real-world impact.
Be sure to check out our podcast, Queens of Quality for more informative and interesting conversations about this and more bio/pharma hot topics.